Related Experiment Video
Updated: Aug 30, 2025

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
A 7-Year-Old With Persistent Fever and Cough
Ethan S Vorel1, Jay J Mehta1,2,3, Michael E Russo1,4,3
1Department of Pediatrics.

Insights
A previously healthy child experienced prolonged fevers and respiratory distress. Despite extensive workups, the cause remained elusive, highlighting the need for systemic evaluation in complex pediatric cases.
Area of Science:
- Pediatric Medicine
- Infectious Diseases
- Rheumatology
Background:
- A 7-year-old girl presented with a 7-week history of daily fevers, worsening cough, and elevated inflammatory markers.
- Previous extensive outpatient workups by multiple specialists, including infectious disease and rheumatology, were unrevealing.
Observation:
- The patient exhibited respiratory distress, stridor, leukocytosis, microcytic anemia, hypoalbuminemia, and elevated ferritin and fecal calprotectin.
- Initial investigations, including infectious studies and rheumatologic tests, were negative. Computed tomography revealed mediastinal lymphadenopathy, later deemed nonpathologic.
- Ophthalmologic examination showed bilateral anterior uveitis, but rheumatologic markers remained negative.
Findings:
- Despite multiple antibiotic courses and initial steroid trials, the patient's condition worsened, leading to intubation and ICU transfer.
- Severe purulent tracheitis was identified on bronchoscopy, yet throat cultures were sterile.
- The persistent clinical deterioration without an identified pathogen prompted further investigation for a systemic etiology.
Implications:
- This case underscores the diagnostic challenges in pediatric patients with prolonged unexplained fevers and respiratory symptoms.
- It highlights the importance of considering systemic inflammatory or autoimmune conditions even with negative initial workups.
- Further evaluation for rare or complex systemic diseases is crucial for effective management in similar pediatric presentations.
Abstract:
A previously healthy, fully immunized 7-year-old girl presented with a 7-week history of daily fevers and a worsening cough with persistently elevated inflammatory markers. Before admission, she had an unrevealing outpatient workup by infectious disease, rheumatology, pulmonology, and otorhinolaryngology for her fever and other symptoms. Multiple courses of antibiotics had no effect, but brief courses of steroids seemed to modestly alleviate her symptoms. At an outside hospital, a computed tomography neck and chest scan revealed mediastinal lymphadenopathy. She was subsequently transferred to the authors' institution. Her examination was notable for a febrile, tired-appearing girl in respiratory distress with a muffled voice and inspiratory stridor. Her laboratory tests revealed leukocytosis with left shift, microcytic anemia, and hypoalbuminemia, as well as elevated inflammatory markers, ferritin, and fecal calprotectin. Her peripheral smear, uric acid, and lactate dehydrogenase were all within normal limits. Infectious study results, including blood and urine cultures, cytomegalovirus serologies, and Bartonella serologies were negative. On the second read of her outside computed tomography imaging, her lymphadenopathy was felt to be nonpathologic. Based on a recommendation by rheumatology, an ophthalmologic examination was obtained, which revealed bilateral anterior uveitis; however, rheumatologic laboratory test results returned negative. Her fevers continued, and inflammatory markers remained elevated despite antibiotics. On day 6 of hospitalization, she developed worsening respiratory distress, necessitating intubation and transfer to the ICU. Repeat laryngoscopy and bronchoscopy revealed severe purulent tracheitis; however, throat cultures remained sterile. Her clinical deterioration without identification of an offending organism prompted additional evaluation for a systemic etiology.
Related Concept Videos
 01:29
Pneumonia II: Pathophysiology
 01:25
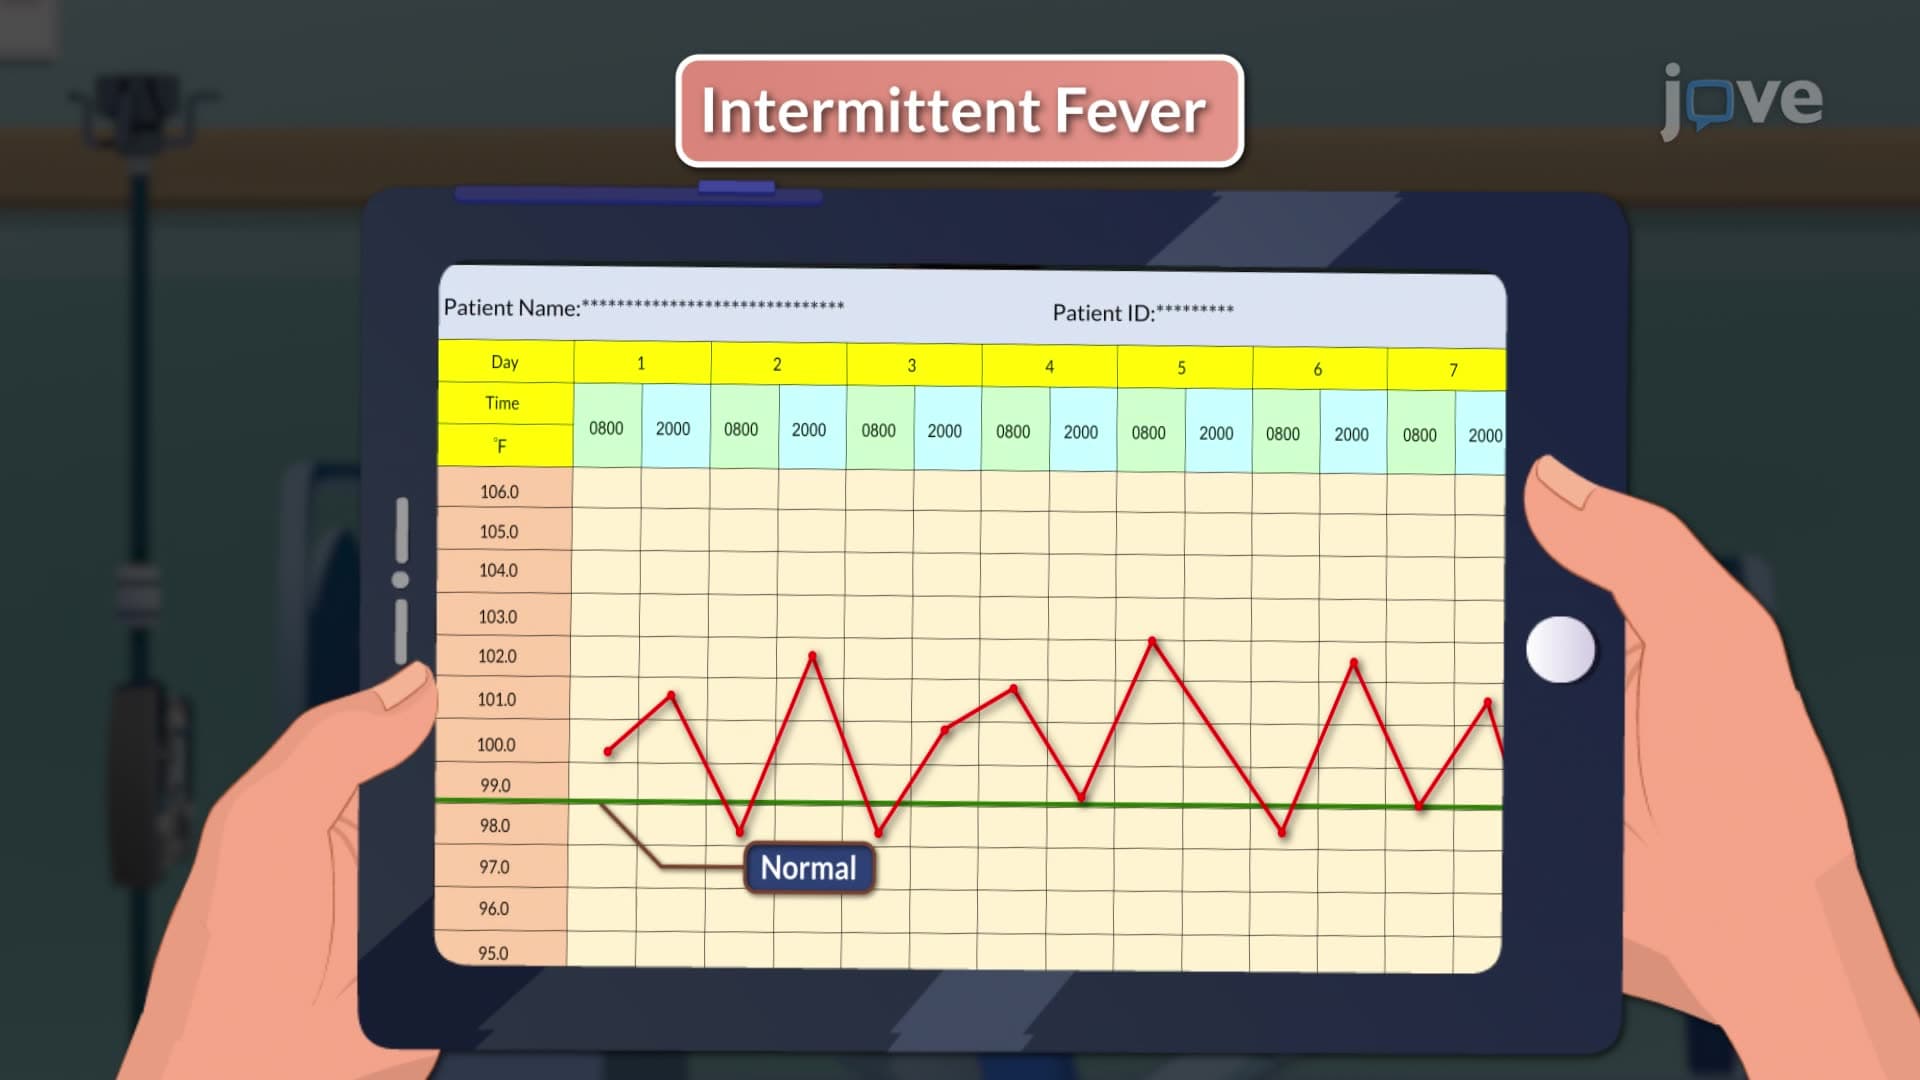
Types of Fever
Here are the different types of fever:
 01:26
Patterns of Fever
 01:30
Pneumonia III: Complications and Assessment
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....