Related Experiment Video
Updated: Aug 30, 2025

A High-throughput Method for Measurement of Glomerular Filtration Rate in Conscious Mice
Published on: May 10, 2013
Reliability of glomerular filtration rate estimating formulas compared to iohexol plasma clearance in critically ill
Evelyn Dhont1,2, Charlotte Windels3, Evelien Snauwaert4
1Department of Pediatric Intensive Care, Pediatric Intensive Care 1K12D, Ghent University Hospital, C. Heymanslaan 10, 9000, Ghent, Belgium. evelyn.dhont@uzgent.be.

Insights
Estimates of glomerular filtration rate (eGFR) formulas are inaccurate for critically ill children in the pediatric intensive care unit (PICU). Clinicians should use caution when applying these estimates for drug dosing and treatment decisions.
Area of Science:
- Pediatric Nephrology
- Critical Care Medicine
- Pharmacokinetics
Background:
- Accurate renal function assessment is vital for pediatric intensive care unit (PICU) patients, influencing critical decisions and drug dosing.
- Existing estimated glomerular filtration rate (eGFR) formulas, commonly used in critically ill children, lack validation against measured GFR (mGFR) in this specific population.
- Biomarkers used in eGFR calculations have limitations in PICU settings, and their formulas have not been previously verified against mGFR in critically ill children.
Purpose of the Study:
- To evaluate the reliability of commonly used eGFR formulas compared to measured GFR (mGFR) using iohexol plasma clearance (CLiohexol) in a pediatric intensive care unit (PICU) population.
- To assess the prevalence of acute kidney injury (AKI) and augmented renal clearance (ARC) within 48 hours of admission using both mGFR and eGFR.
- To compare the diagnostic accuracy of eGFR formulas versus mGFR for AKI and ARC in critically ill children.
Main Methods:
- GFR was measured using iohexol plasma clearance (CLiohexol) and estimated using 26 formulas (creatinine, cystatin C, betatrace protein-based) in 98 children (0-15 years) admitted to the PICU.
- Statistical analyses included Bland-Altman analysis to assess bias, precision, and accuracy (P30, P10) of eGFR formulas against mGFR.
- Prevalence of AKI and ARC was determined based on mGFR and compared with diagnoses derived from the revised Schwartz eGFR formula.
Main Results:
- Most eGFR formulas, including the widely used revised Schwartz formula, significantly overestimated mGFR, exhibiting large bias and poor precision.
- The revised Schwartz formula showed a bias of -18 ± 51%, with only 51% of estimates within 30% of mGFR (P30).
- Agreement between the revised Schwartz formula and mGFR for diagnosing AKI and ARC was poor (kappa values of 0.342), with low sensitivity for AKI (30%).
Conclusions:
- Established eGFR formulas demonstrate significant inaccuracies in critically ill children within the PICU setting.
- Clinicians must exercise caution when using eGFR formulas for therapeutic decisions, including drug dosing, in this vulnerable patient group.
- Further research is needed in specific pediatric subgroups to determine the generalizability of these findings and explore alternatives like iohexol plasma clearance for precise GFR assessment.
Abstract:
Accurate renal function assessment is crucial to guide intensive care decision-making and drug dosing. Estimates of glomerular filtration rate (eGFR) are routinely used in critically ill children; however, these formulas were never evaluated against measured GFR (mGFR) in this population. We aimed to assess the reliability of common eGFR formulas compared to iohexol plasma clearance (CLiohexol) in a pediatric intensive care (PICU) population. Secondary outcomes were the prevalence of acute kidney injury (AKI) (by pRIFLE criteria) and augmented renal clearance (ARC) (defined as standard GFR for age + 2 standard deviations (SD)) within 48 h after admission based on mGFR and eGFR by the revised Schwartz formula and the difference between these two methods to diagnose AKI and ARC. In children, between 0 and 15 years of age, without chronic renal disease, GFR was measured by CLiohexol and estimated using 26 formulas based on creatinine (Scr), cystatine C (CysC), and betatrace protein (BTP), early after PICU admission. eGFR and mGFR results were compared for the entire study population and in subgroups according to age, using Bland-Altman analysis with calculation of bias, precision, and accuracy expressed as percentage of eGFR results within 30% (P30) and 10% (P10) of mGFR. CLiohexol was measured in 98 patients. Mean CLiohexol (± SD) was 115 ± 54 ml/min/1.73m2. Most eGFR formulas showed overestimation of mGFR with large bias and poor precision reflected by wide limits of agreement (LoA). Bias was larger with CysC- and BTP-based formulas compared to Scr-based formulas. In the entire study population, none of the eGFR formulas showed the minimal desired P30 > 75%. The widely used revised Schwartz formula overestimated mGFR with a high percentage bias of - 18 ± 51% (95% confidence interval (CI) - 29; - 9), poor precision with 95% LoA from - 120 to 84% and insufficient accuracy reflected by P30 of only 51% (95% CI 41; 61), and P10 of 21% (95% CI 13; 66) in the overall population. Although performance of Scr-based formulas was worst in children below 1 month of age, exclusion of neonates and younger children did not result in improved agreement and accuracy. Based on mGFR, prevalence of AKI and ARC within 48 h was 17% and 45% of patients, respectively. There was poor agreement between revised Schwartz formula and mGFR to diagnose AKI (kappa value of 0.342, p < 0.001; sensitivity of 30%, 95% CI 5; 20%) and ARC (kappa value of 0.342, p < 0.001; sensitivity of 70%, 95% CI 33; 58).
Conclusion:
In this proof-of-concept study, eGFR formulas were found to be largely inaccurate in the PICU population. Clinicians should therefore use these formulas with caution to guide drug dosing and therapeutic interventions in critically ill children. More research in subgroup populations is warranted to conclude on generalizability of these study findings.
Clinicaltrials:
gov NCT05179564, registered retrospectively on January 5, 2022.
What Is Known:
• Both acute kidney injury and augmented renal clearance may be present in PICU patients and warrant adaptation of therapy, including drug dosing. • Biomarker-based eGFR formulas are widely used for GFR assessment in critically ill children, although endogenous filtration biomarkers have important limitations in PICU patients and eGFR formulas have never been validated against measured GFR in this population.
What Is New:
• eGFR formulas were found to be largely inaccurate in the PICU population when compared to measured GFR by iohexol clearance. Clinicians should therefore use these formulas with caution to guide drug dosing and therapeutic interventions in critically ill children. • Iohexol plasma clearance could be considered an alternative for accurate GFR assessment in PICU patients.

Related Concept Videos
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:07
Determination of Renal Drug Clearance: Graphical and Midpoint Methods
The graphical method involves plotting the rate of drug excretion in urine against the plasma drug concentration. By analyzing the graph, the clearance can be calculated and obtained. Drugs rapidly excreted by the kidneys exhibit a...
 01:11
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:06
Renal Drug Clearance: Overview
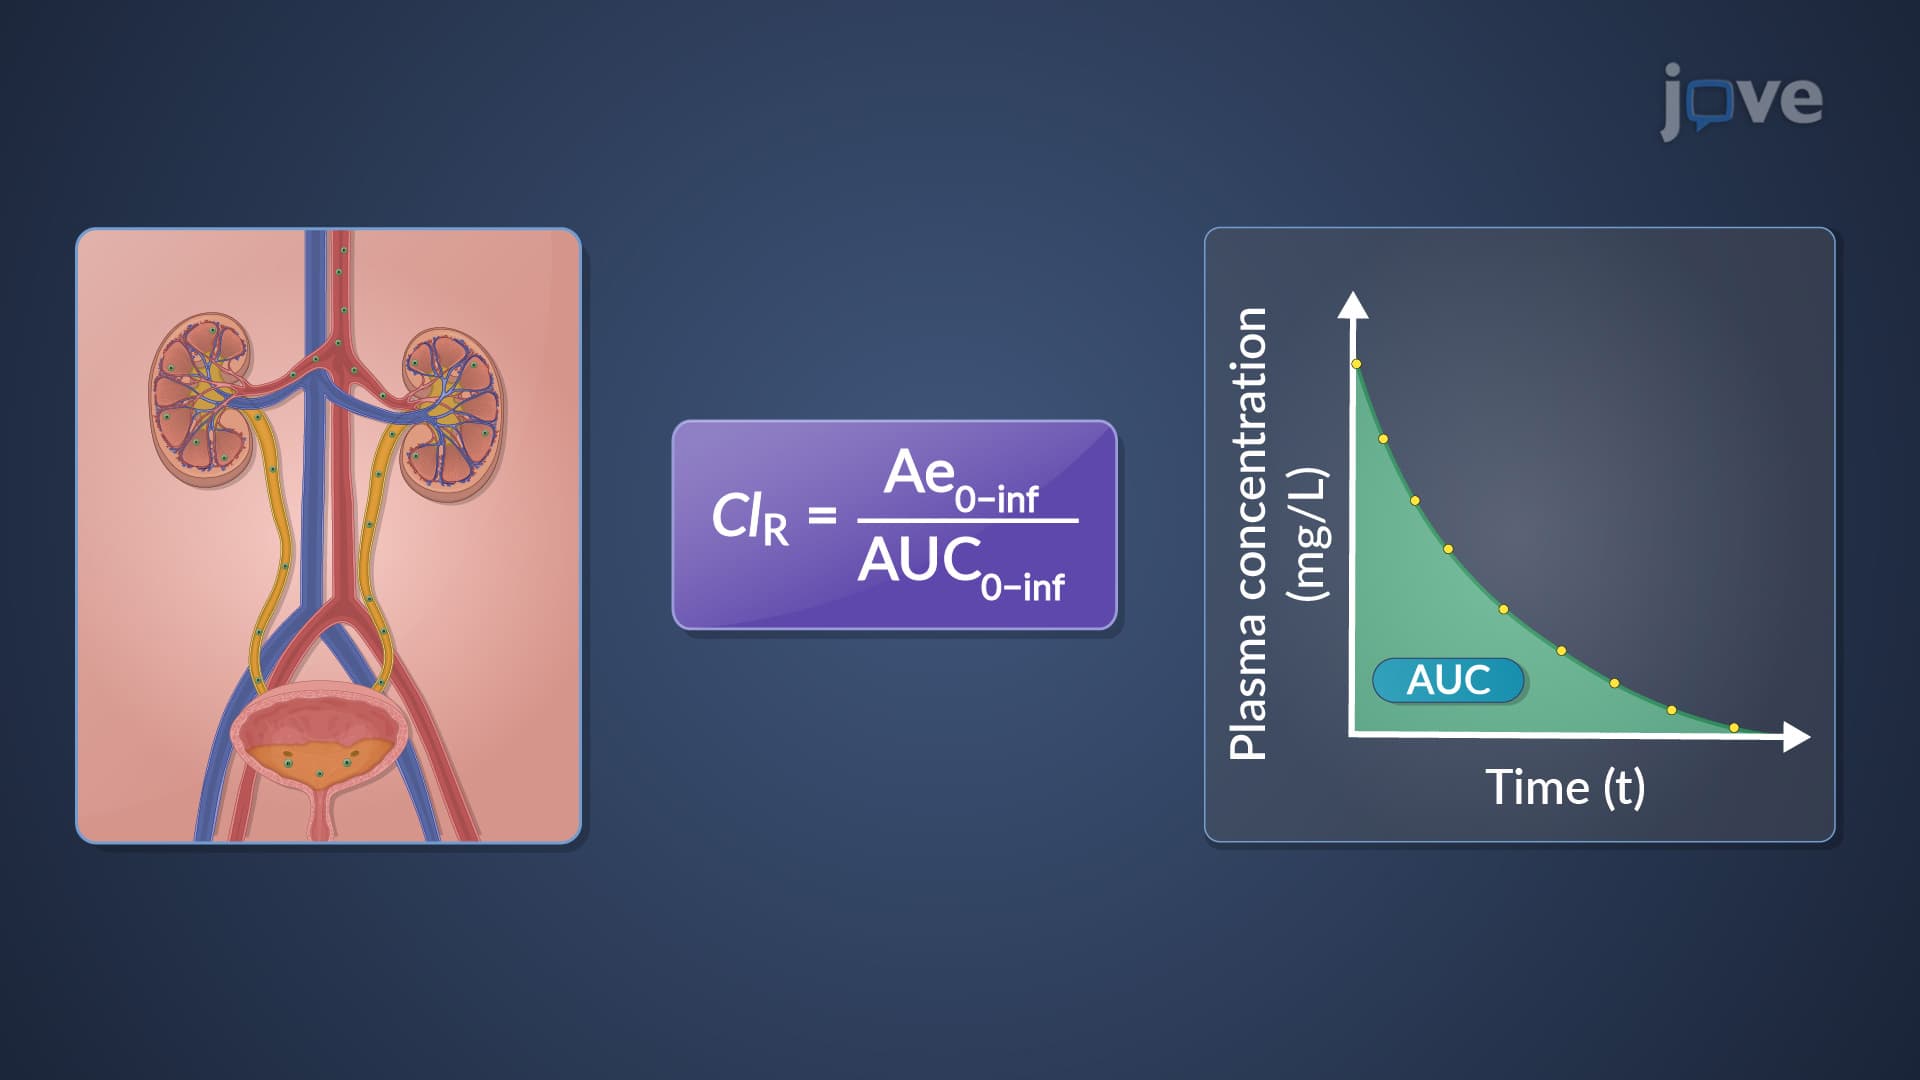
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...