Related Experiment Video
Updated: Aug 27, 2025
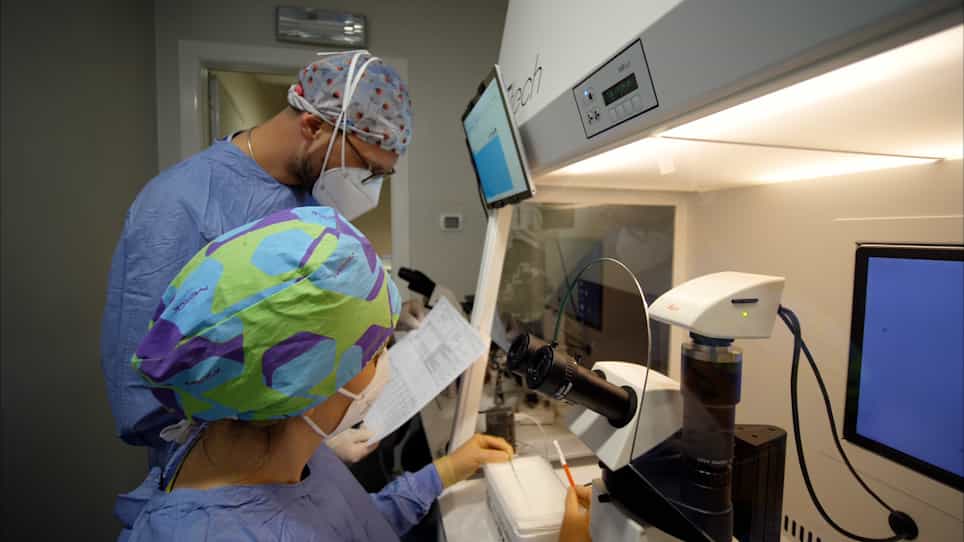

Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Oral Contraceptives and Female Rowers' Skeletal Health
Allen L Redinger1, Breanne S Baker
1Musculoskeletal Adaptations to Aging and exercise (MAAX) Lab, School of Kinesiology, Applied Health, and Recreation, Oklahoma State University, Stillwater, Oklahoma.

Abstract:
Redinger, AL and Baker, BS. Oral contraceptives and female rowers' skeletal health. J Strength Cond Res 37(3): 669-677, 2023-Previous studies suggest that women using oral contraceptives (OC) experience fewer skeletal benefits from exercise compared with non-OC users. These findings may be especially important for athletes competing in weight-supported sports with a high prevalence of low bone mineral density and fracture, such as rowing. The purpose of this study was to examine skeletal health and bone injuries in collegiate female rowers. Forty-nine National Collegiate Athletic Association Division I female rowers completed general health, menstrual history, and bone physical activity questionnaire (BPAQ) surveys. Dual-energy X-ray absorptiometry (DXA) and peripheral quantitative computed tomography (pQCT) scans were used to assess bone content, density, and geometry. Contraceptive (OC users n = 14, non-OC users n = 35) and self-reported stress fracture (SFx n = 11, None n = 38) groups were analyzed using analysis of covariance and independent t -tests. Additionally, effect sizes ( d ) were calculated and significance was set at p ≤ 0.05. Oral contraceptive users had reduced lumbar spine areal bone mineral density after adjustment for Total BPAQ ( d = 0.58; p = 0.041) compared with non-OC users, but all other total body and site-specific DXA measures of bone mineral content and density were similar between contraceptive and injury groups. When comparing bone geometry of the 4, 38, and 66% tibiae using pQCT, no significant differences were found after adjustment for either contraceptive or injury group (all p > 0.060). Our findings suggest that OC usage was not associated with reduced skeletal health in competitive female rowers as evidenced by all Z-scores being above -2.0 and similar bone indices of mineralized content, density, geometry, and estimated strength between the groups.
More Related Videos


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 02:07
Oogenesis
 01:31
Osteoclasts in Bone Remodeling
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...