Adult-onset Still's disease and fever of unknown origin in India
Related Experiment Video
Updated: Aug 27, 2025
Author Spotlight: AI-Driven Trypanosome Species Detection from Microscopic Images
Published on: October 27, 2023
Ashok Kumar Pannu1, Vidhi Singla1, Vikas Suri1
1Department of Internal Medicine, Postgraduate Institute of Medical Education and Research, Nehru Hospital, Sector 12, 4th floor, F block, Chandigarh, 160012, India.

Abstract:
Despite an essential differential diagnosis for fever of unknown origin (FUO) in young adults, adult-onset Still's disease (AOSD) is infrequently considered and remained underdiagnosed in low-middle-income countries. The present study analyzed the clinical, serological, radiological, and pathological characteristics of AOSD presented as FUO in India. A hospital-based retrospective study of patients aged > 13 years admitted with FUO and later diagnosed with AOSD in Postgraduate Institute of Medical Education and Research, Chandigarh (India), was conducted between January 2014 and December 2020. Petersdorf and Beeson's criteria were used to define FUO. The diagnosis of AOSD was made based on Yamaguchi's criteria. Twenty-seven patients (median age 26 years, 14 females) were enrolled. All presented with intermittent fever with a median duration of 10 weeks. The typical features of AOSD at admission were arthralgia (n = 24), hepatosplenomegaly (n = 21), spiking fever ≥ 39 °C (n = 19), lymphadenopathy (n = 18), typical rash (n = 17), and sore throat (n = 11). Leukocytosis (n = 25) and neutrophilia (n = 19) were frequent. Hyperferritinemia was universal (range, 700-145,003 ng/ml; ≥ 2000, n = 23). At admission, AOSD was suspected in only nine FUO cases, while tuberculosis (n = 16), undifferentiated connective tissue disorder (n = 14), and lymphoproliferative disorder (n = 11) were common diagnostic possibilities. Crispin et al. clinical scale detected AOSD in only 15 (55.5%) FUO patients. Whole-body imaging (n = 27), including fluorodeoxyglucose positron emission tomography (n = 12), demonstrated reticuloendothelial organ-system involvement and serositis. Seventeen (63%) patients had macrophage activation syndrome at the time of AOSD diagnosis. AOSD FUO presents with typical but nonspecific features; thus, early differentiation from common causes (e.g., tuberculosis, lymphoma) is difficult. Macrophage activation syndrome is common in AOSD with FUO presentation.
More Related Videos
 10:04
Analysis of 18FDG PET/CT Imaging as a Tool for Studying Mycobacterium tuberculosis Infection and Treatment in Non-human Primates
Published on: September 5, 2017
 08:44
Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
Related Concept Videos
 01:25
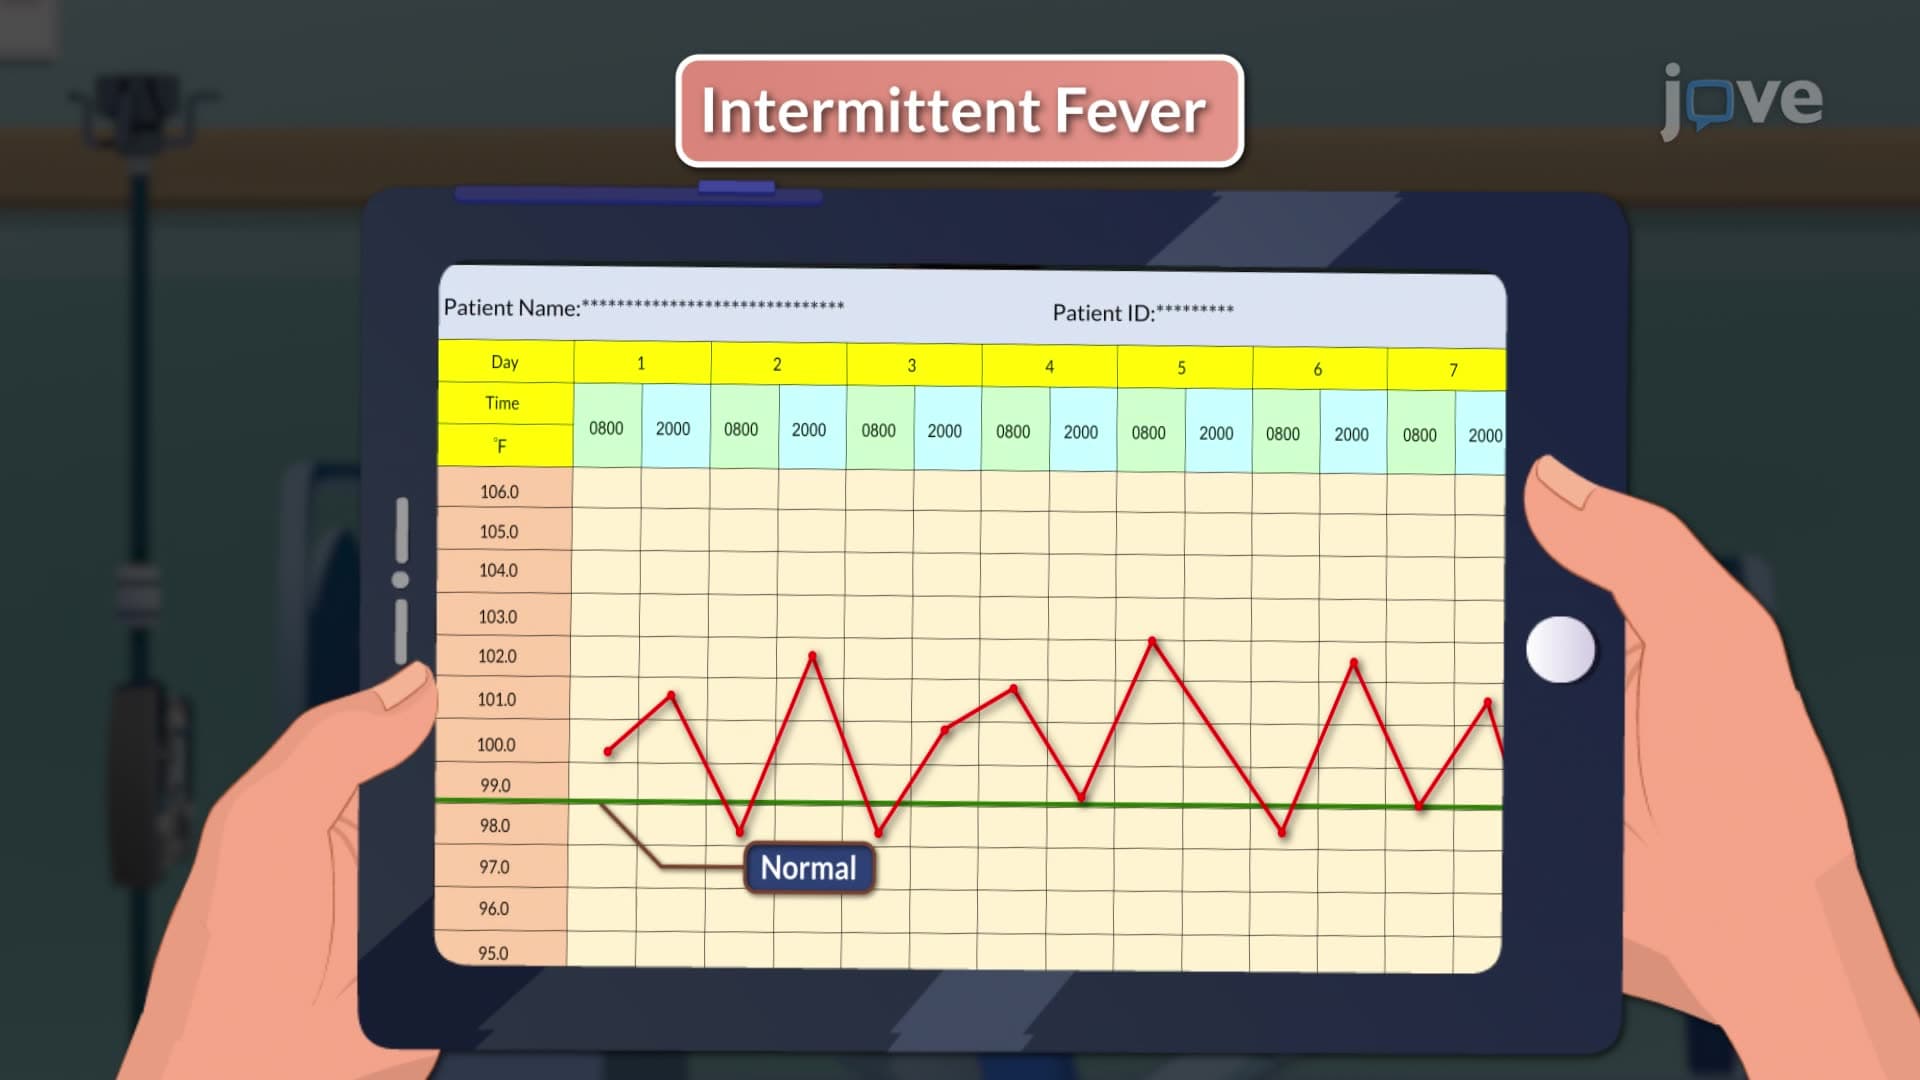
Types of Fever
Here are the different types of fever:
 01:26
Patterns of Fever
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:25
Increased Body Temperature
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis