Related Experiment Video
Updated: Oct 13, 2026
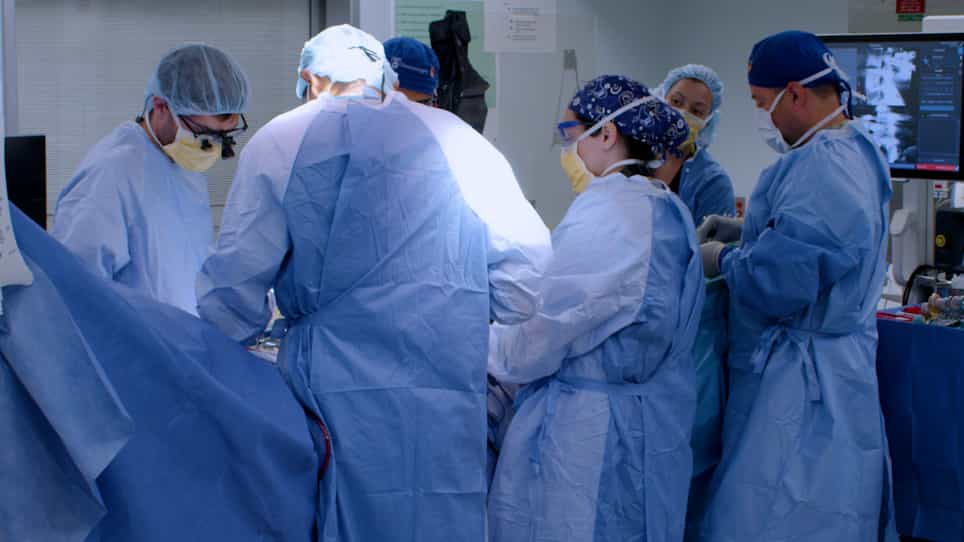
Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021
Editorial Commentary: The Pelvis is the Lowest Vertebral Level: Diagnostic Approach to Hip-Spine Syndrome

Abstract:
The human pelvis represents a wonderful example of apparent idealistic simplicity overwhelmed by realistic complexity. Traditionally, the pelvis has been termed a "ring" linking the lower extremity to the spine via the sacroiliac joint. In essence, the pelvis is the lowest vertebral level-"the hip bone's connected to the spine bone." Thus, the law of parsimony seemingly applies in the diagnosis and management of both arthritic and nonarthritic hip and spine disorders in isolation or combination. However, an inverse Occam's razor is much more likely. The layered theory of hip disorders illustrates how a base osteochondral layer (femoroacetabular impingement syndrome, ischiofemoral impingement from either the lesser trochanter or greater trochanter, arthritis), a static inert soft-tissue layer (labrum, capsule, ligament), a dynamic soft-tissue layer (muscle, tendon), and a neurokinetic chain layer all interact and can lead to hundreds, if not thousands, of different combinations of primary and secondary symptom sources. Although correlation does not equal causation, intuitively and overly simplistically, a stiff painful hip can transfer stress across the pelvic ring to the spine, causing back pain. Alternatively, 2 separate symptom sources could be present at the same time. Biomechanical stress transfer can occur from flexion-based (e.g., femoroacetabular impingement syndrome) or extension-based (e.g., ischiofemoral impingement) problems. The diagnosis of hip-spine syndrome in patients becomes really complicated usually really fast, encompassing the hip joint, peritrochanteric space, deep gluteal space, pelvis and pelvic floor, sacroiliac joint, and lumbosacral spine-and don't forget mental health and the mind controls the musculotendinous system in these challenging, often frustrated, patients. Static imaging findings necessitate dynamic symptom correlation, especially via pertinent values including pelvic incidence; pelvic tilt; sacral slope; lumbar lordosis; femoral and acetabular version; cam, pincer, and dysplastic morphologies; and leg length. Judicious diagnostic injections can greatly assist in clinical symptom interpretation. Successful treatment requires consideration and management of the primary etiology and pertinent secondary downstream effects. When a patient's hip hurts, one should always look at the patient's back; when a patient's back hurts, one should always look at the patient's hip.
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:16
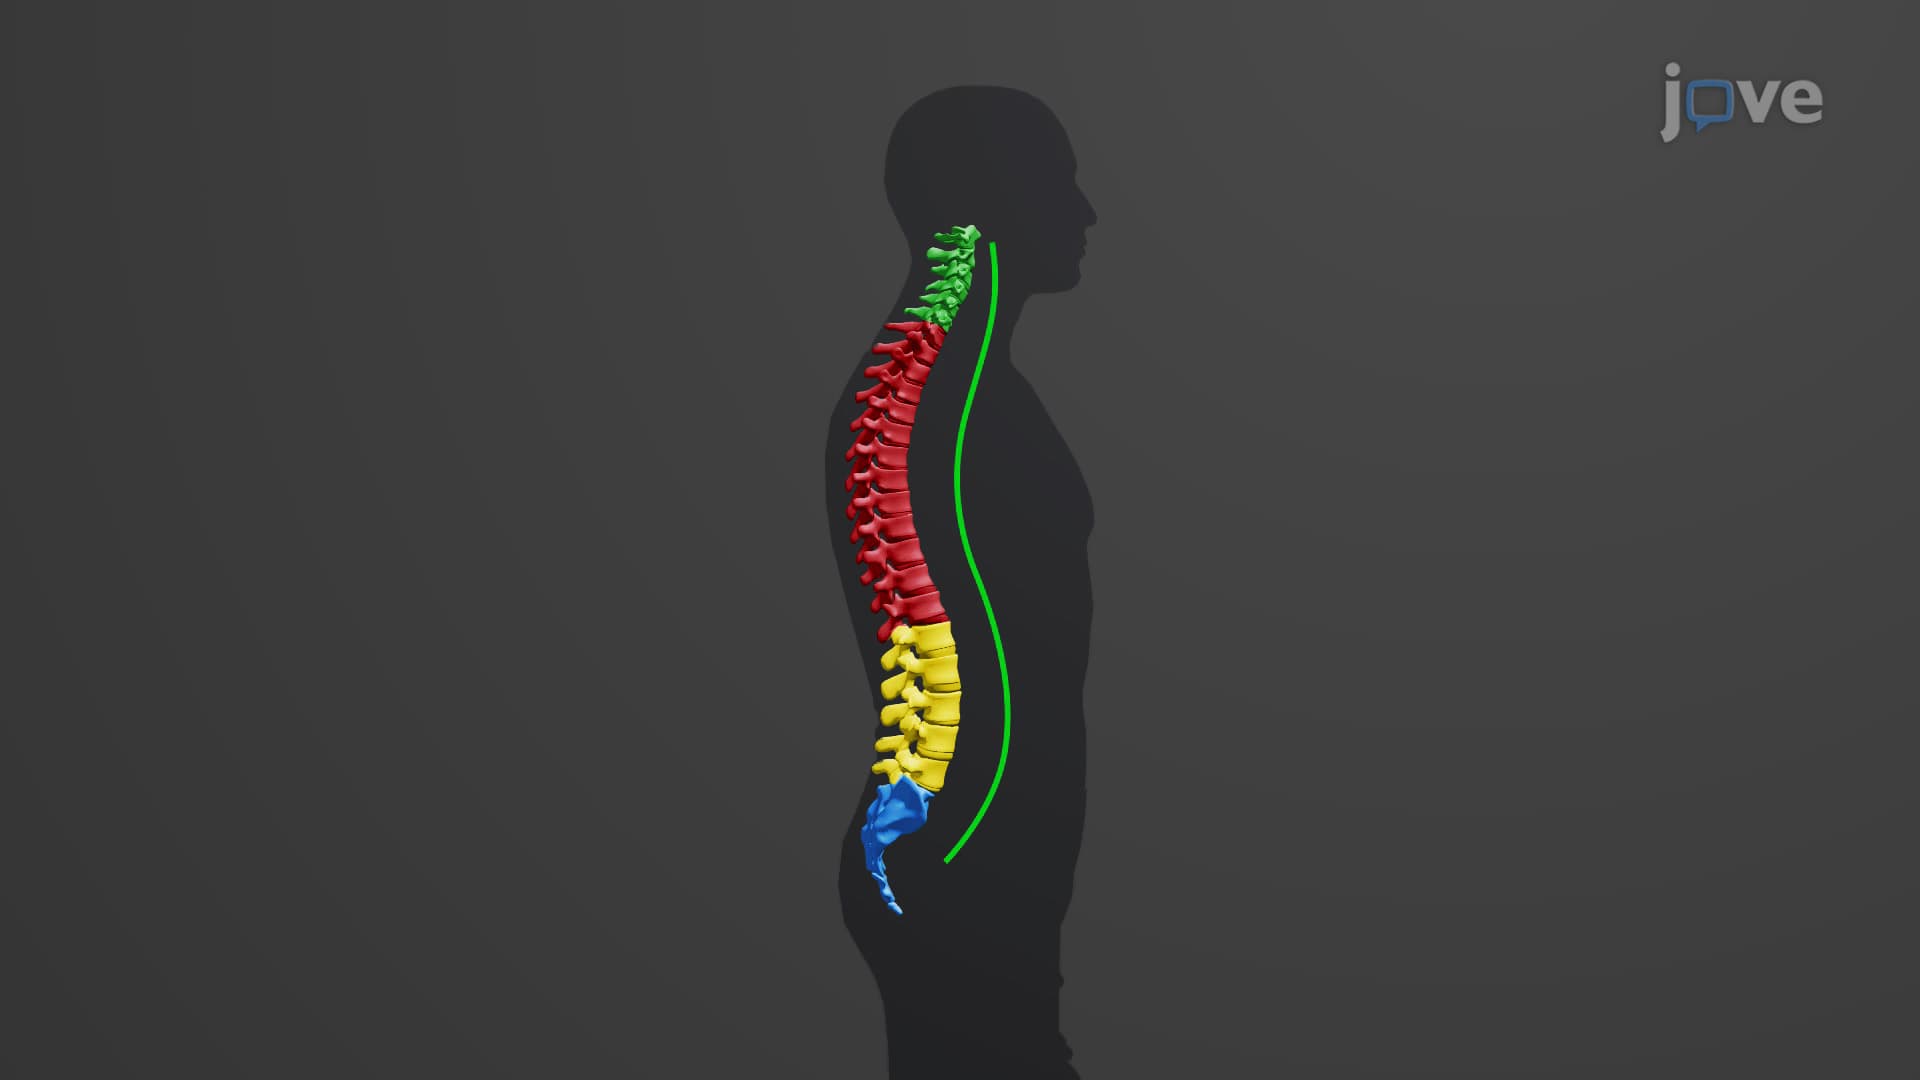
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four quadrants...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:29
Herniated Intervertebral Disc l: Introduction