Related Experiment Video
Updated: Aug 26, 2025
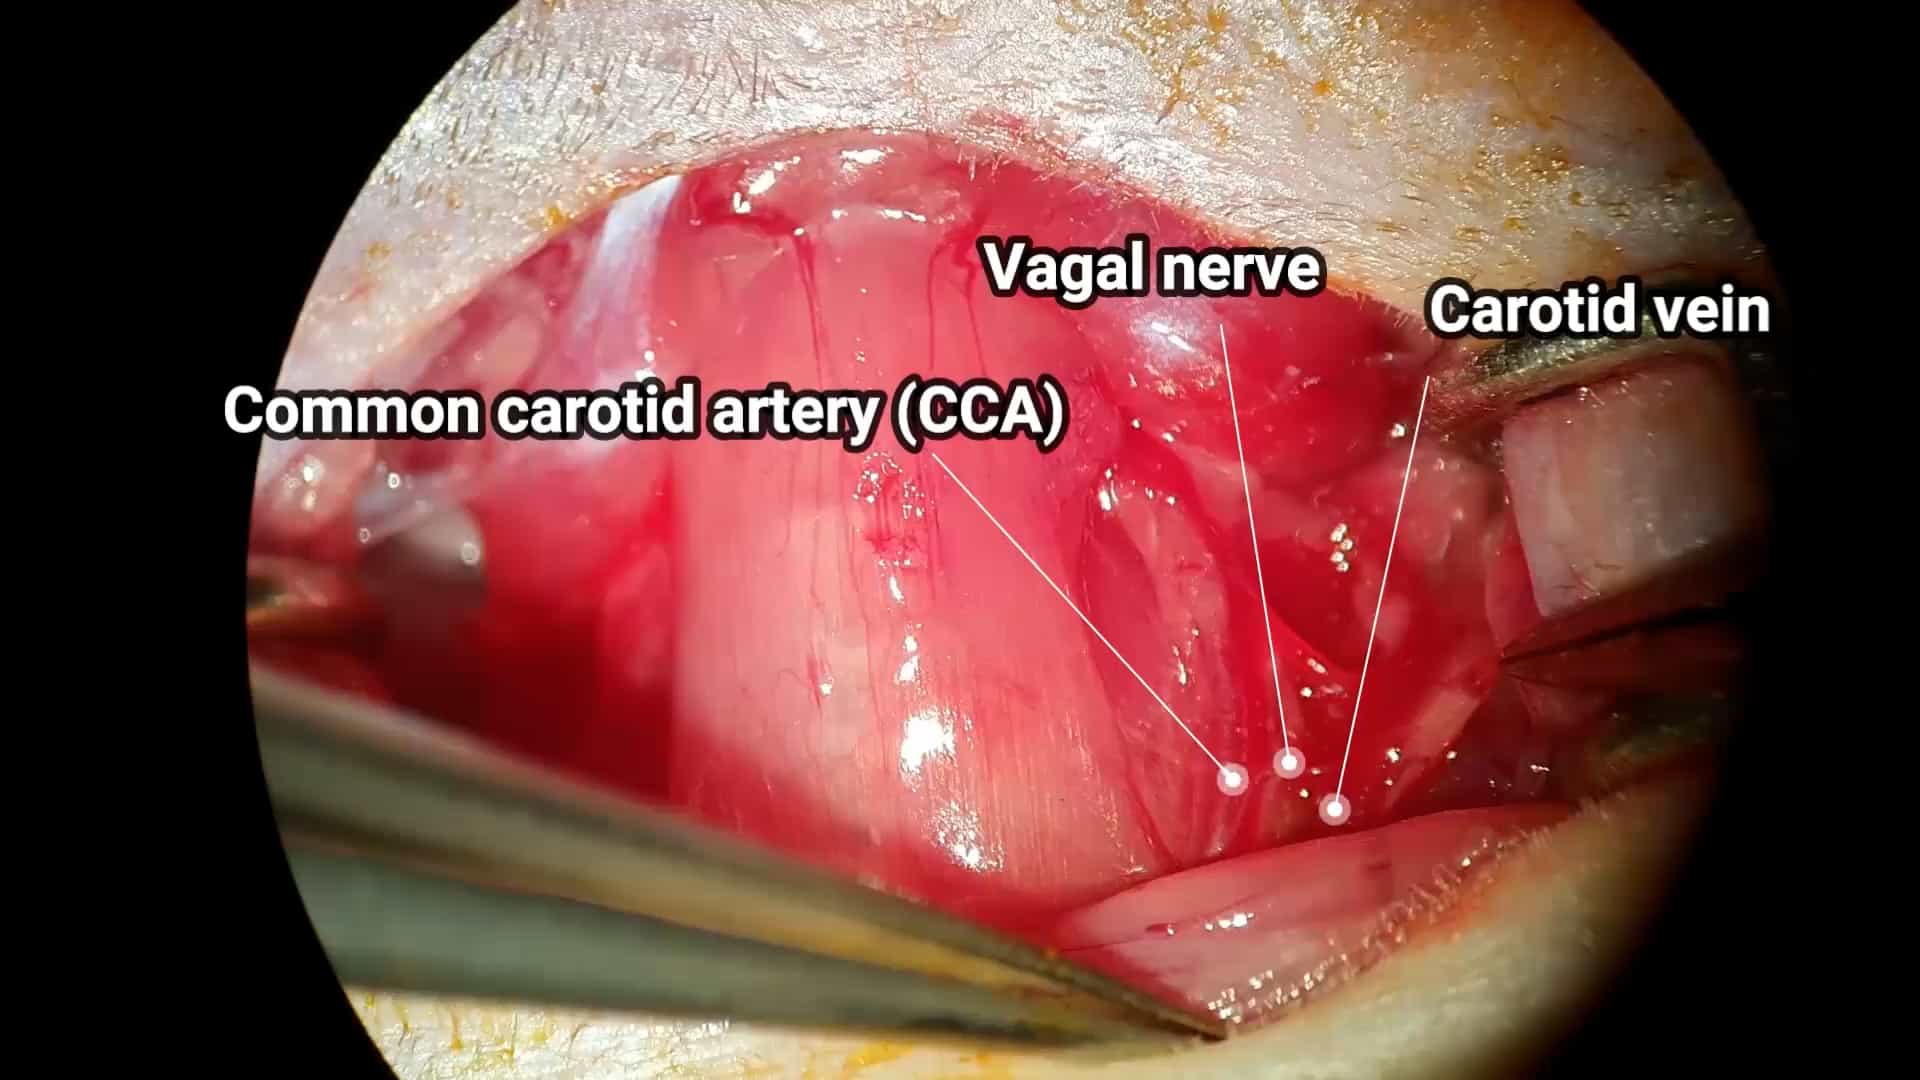

Optimization of the Longa Middle Cerebral Artery Occlusion Method for Complete Reperfusion
Published on: November 22, 2024
A Systematic Review and Meta-Analysis of Clinical Outcomes of Patients Undergoing Chronic Total Occlusion
Bahadir Simsek, Spyridon Kostantinis, Judit Karacsonyi
1Director of the Center for Complex Coronary Interventions, Minneapolis Heart Institute, Chairman of the Center for Coronary Artery Disease at the Minneapolis Heart Institute Foundation, 920 East 28th Street #300, Minneapolis, MN 55407 USA. esbrilakis@gmail.com.

Objectives:
Chronic total occlusion (CTO) percutaneous coronary intervention (PCI) can improve patient symptoms, but it remains controversial whether it impacts subsequent clinical outcomes.
Methods:
In this systematic review and meta-analysis, we queried PubMed, ScienceDirect, Cochrane Library, Web of Science, and Embase databases (last search: September 15, 2021). We investigated the impact of CTO-PCI on clinical events including all-cause mortality, cardiovascular death, myocardial infarction (MI), major adverse cardiovascular event (MACE), stroke, subsequent coronary artery bypass surgery, target-vessel revascularization, and heart failure hospitalizations. Pooled analysis was performed using a random-effects model.
Results:
A total of 58 publications with 54,540 patients were included in this analysis, of which 33 were observational studies of successful vs failed CTO-PCI, 19 were observational studies of CTO-PCI vs no CTO-PCI, and 6 were randomized controlled trials (RCTs). In observational studies, but not RCTs, CTO-PCI was associated with better clinical outcomes. Odds ratios (ORs) and 95% confidence intervals (CIs) for all-cause mortality, MACE, and MI were 0.52 (95% CI, 0.42-0.64), 0.46 (95% CI, 0.37-0.58), 0.66 (95% CI, 0.50-0.86), respectively for successful vs failed CTO-PCI studies; 0.38 (95% CI, 0.31-0.45), 0.57 (95% CI, 0.42-0.78), 0.65 (95% CI, 0.42-0.99), respectively, for observational studies of CTO-PCI vs no CTO-PCI; 0.72 (95% CI, 0.39-1.32), 0.69 (95% CI, 0.38-1.25), and 1.04 (95% CI, 0.46-2.37), respectively for RCTs.
Conclusions:
CTO-PCI is associated with better subsequent clinical outcomes in observational studies but not in RCTs. Appropriately powered RCTs are needed to conclusively determine the impact of CTO-PCI on clinical outcomes.


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:26
Coronary Artery Disease II: Pathophysiology