Related Experiment Video
Updated: Aug 24, 2025


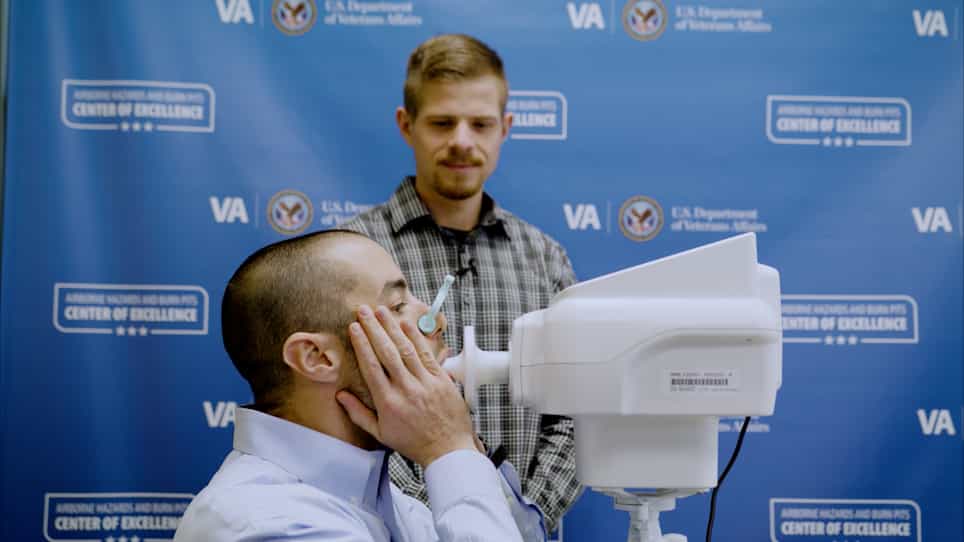
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Characterization of chronic lung allograft dysfunction phenotypes using spectral and intrabreath oscillometry
Anne Fu1, Anastasiia Vasileva1, Nour Hanafi1
1Division of Respirology, Department of Medicine, Temerty Faculty of Medicine, University of Toronto, Toronto, ON, Canada.

Abstract:
Background: Chronic lung allograft dysfunction (CLAD) is the major cause of death beyond 2 years after lung transplantation and develops in 50% of all patients by 5 years post-transplant. CLAD is diagnosed on the basis of a sustained drop of 20% for at least 3 months in the forced expiratory volume (FEV1), compared to the best baseline value achieved post-transplant. CLAD presents as two main phenotypes: bronchiolitis obliterans syndrome (BOS) is more common and has better prognosis than restrictive allograft syndrome (RAS). Respiratory oscillometry is a different modality of lung function testing that is highly sensitive to lung mechanics. The current study investigated whether spectral and intrabreath oscillometry can differentiate between CLAD-free, BOS- and RAS-CLAD at CLAD onset, i.e., at the time of the initial 20% drop in the FEV1. Methods: A retrospective, cross-sectional analysis of 263 double lung transplant recipients who underwent paired testing with oscillometry and spirometry at the Toronto General Pulmonary Function Laboratory from 2017 to 2022 was conducted. All pulmonary function testing and CLAD diagnostics were performed following international guidelines. Statistical analysis was conducted using multiple comparisons. Findings: The RAS (n = 6) spectral oscillometry pattern differs from CLAD-free (n = 225) by right-ward shift of reactance curve similar to idiopathic pulmonary fibrosis whereas BOS (n = 32) has a pattern similar to obstructive lung disease. Significant differences were found in most spectral and intrabreath parameters between BOS, RAS, and time-matched CLAD-free patients. Post-hoc analysis revealed these differences were primarily driven by BOS instead of RAS. While no differences were found between CLAD-free and RAS patients with regards to spectral oscillometry, the intrabreath metric of reactance at end-inspiration (XeI) was significantly different (p < 0.05). BOS and RAS were differentiated by spectral oscillometry measure R5, and intrabreath resistance at end expiration, ReE (p < 0.05 for both). Conclusion: Both spectral and intrabreath oscillometry can differentiate BOS-CLAD from CLAD-free states while intrabreath oscillometry, specifically XeI, can uniquely distinguish RAS-CLAD from CLAD-free. Spectral and intrabreath oscillometry offer complementary information regarding lung mechanics in CLAD patients to help distinguish the two phenotypes and could prove useful in prognostication.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...