Related Experiment Video
Updated: Aug 20, 2025
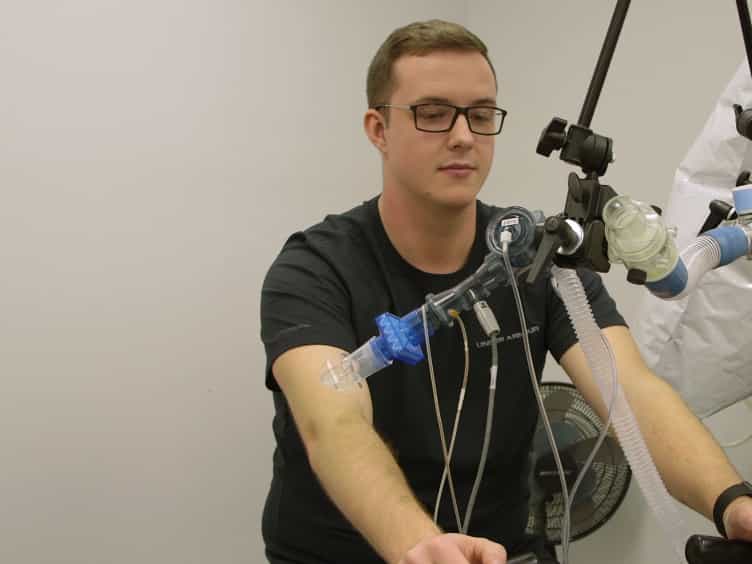

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Preserved peak exercise capacity in Andean highlanders with excessive erythrocytosis both before and after isovolumic
Cecilia Anza-Ramírez1, Wanjun Gu2, José L Macarlupú1
1Facultad de Ciencias y Filosofía, Laboratorio de Fisiología Comparada/Laboratorio de Fisiología del Transporte de Oxígeno, Universidad Peruana Cayetano Heredia, Lima, Perú.

In chronic mountain sickness (CMS), increased blood oxygen (O2)-carrying capacity due to excessive erythrocytosis (EE, [Hb] ≥ 21 g/dL) could be offset, especially during exercise by both impaired cardiac output (Q̇t) and O2 diffusion limitation in lungs and muscle. We hypothesized that EE results in reduced peak V̇o2 despite increased blood O2-carrying capacity, and that isovolumic hemodilution (IVHD) improves exercise capacity. In 14 male residents of Cerro de Pasco, Peru (4,340 m), six with and eight without EE, we measured peak cycle-exercise capacity, V̇o2, Q̇t, arterial blood gas parameters, and (resting) blood volume. This was repeated for participants with EE after IVHD, reducing hematocrit by 20% (from 67% to 53%). From these data, we quantified the major O2 transport pathway components (ventilation, pulmonary alveolar-capillary diffusion, Q̇t, and blood-muscle mitochondria diffusion). Participants with EE had similar peak V̇o2, systemic O2 delivery, and O2 extraction as non-EE controls, however, with lower Q̇t and higher arterial [O2]. After IVHD, peak V̇o2 was preserved (but not enhanced), with lower O2 delivery (despite higher Q̇t) balanced by greater O2 extraction. The considerable variance in exercise capacity across the 14 individuals was explained essentially completely by differences in both pulmonary and muscle O2 diffusional conductances and not by any differences in ventilation, [Hb], nor Q̇t. In conclusion, EE does not result in lower peak V̇o2 in Andean males, and IVHD maintains, but does not enhance, exercise capacity.NEW & NOTEWORTHY Male Andean highlanders with and without excessive erythrocytosis (EE) have similar peak V̇o2 at 4,340 m, with higher arterial [O2] in EE and lower cardiac output (Q̇t), thus maintaining similar O2 delivery. Peak V̇o2 in participants with EE was unaffected by isovolumic hemodilution (hematocrit reduced from 67% to 53%), with lower O2 delivery balanced by slightly increased Q̇t and greater O2 extraction. Differences in lung and muscle diffusing capacity, and not hematocrit variation, accounted for essentially all interindividual variance in peak V̇o2.
In chronic mountain sickness (CMS), increased blood oxygen (O2)-carrying capacity due to excessive erythrocytosis (EE, [Hb] ≥ 21 g/dL) could be offset, especially during exercise by both impaired cardiac output (Q̇t) and O2 diffusion limitation in lungs and muscle. We hypothesized that EE results in reduced peak V̇o2 despite increased blood O2-carrying capacity, and that isovolumic hemodilution (IVHD) improves exercise capacity. In 14 male residents of Cerro de Pasco, Peru (4,340 m), six with and eight without EE, we measured peak cycle-exercise capacity, V̇o2, Q̇t, arterial blood gas parameters, and (resting) blood volume. This was repeated for participants with EE after IVHD, reducing hematocrit by 20% (from 67% to 53%). From these data, we quantified the major O2 transport pathway components (ventilation, pulmonary alveolar-capillary diffusion, Q̇t, and blood-muscle mitochondria diffusion). Participants with EE had similar peak V̇o2, systemic O2 delivery, and O2 extraction as non-EE controls, however, with lower Q̇t and higher arterial [O2]. After IVHD, peak V̇o2 was preserved (but not enhanced), with lower O2 delivery (despite higher Q̇t) balanced by greater O2 extraction. The considerable variance in exercise capacity across the 14 individuals was explained essentially completely by differences in both pulmonary and muscle O2 diffusional conductances and not by any differences in ventilation, [Hb], nor Q̇t. In conclusion, EE does not result in lower peak V̇o2 in Andean males, and IVHD maintains, but does not enhance, exercise capacity.NEW & NOTEWORTHY Male Andean highlanders with and without excessive erythrocytosis (EE) have similar peak V̇o2 at 4,340 m, with higher arterial [O2] in EE and lower cardiac output (Q̇t), thus maintaining similar O2 delivery. Peak V̇o2 in participants with EE was unaffected by isovolumic hemodilution (hematocrit reduced from 67% to 53%), with lower O2 delivery balanced by slightly increased Q̇t and greater O2 extraction. Differences in lung and muscle diffusing capacity, and not hematocrit variation, accounted for essentially all interindividual variance in peak V̇o2.
More Related Videos
 12:37
Surgical Placement of Catheters for Long-term Cardiovascular Exercise Testing in Swine
Published on: February 9, 2016
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
Related Concept Videos
 01:24
Factors Affecting Erythropoiesis
Several factors influence the erythrocyte production rate, with tissue oxygen level being among the most critical. Intense exercise or high altitudes can cause tissue hypoxia, which triggers the kidneys to release more erythropoietin (EPO) into the bloodstream.
EPO then...
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction...