Related Experiment Video
Updated: Aug 18, 2025

Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Robotic-assisted Laparoscopic Supracervical Repair of a Chronic Puerperal Uterine Inversion
Matthew Fallon1, William Nolan1, Praba Jeyalingam1
1From the Department of Obstetrics and Gynecology, Sisters of Charity Hospital, University at Buffalo, Buffalo, New York (all authors).

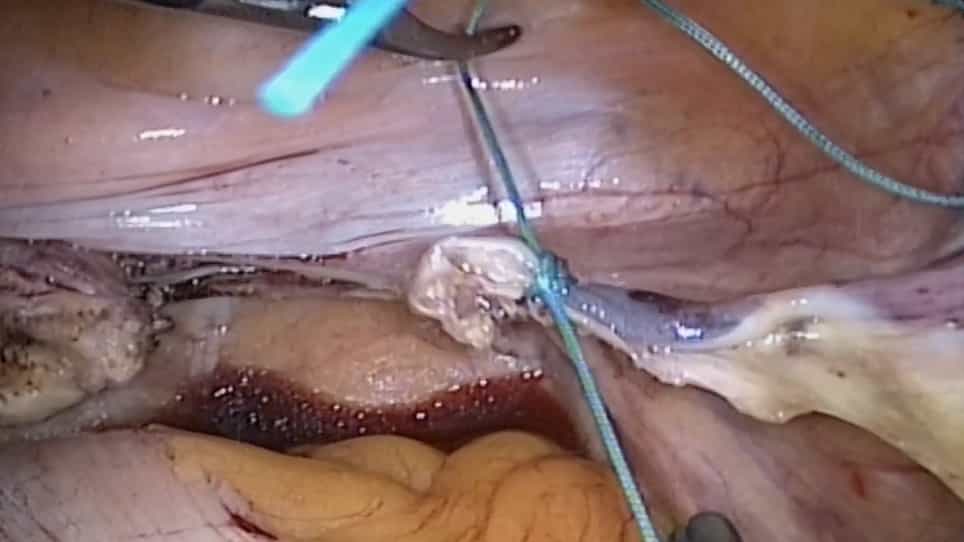
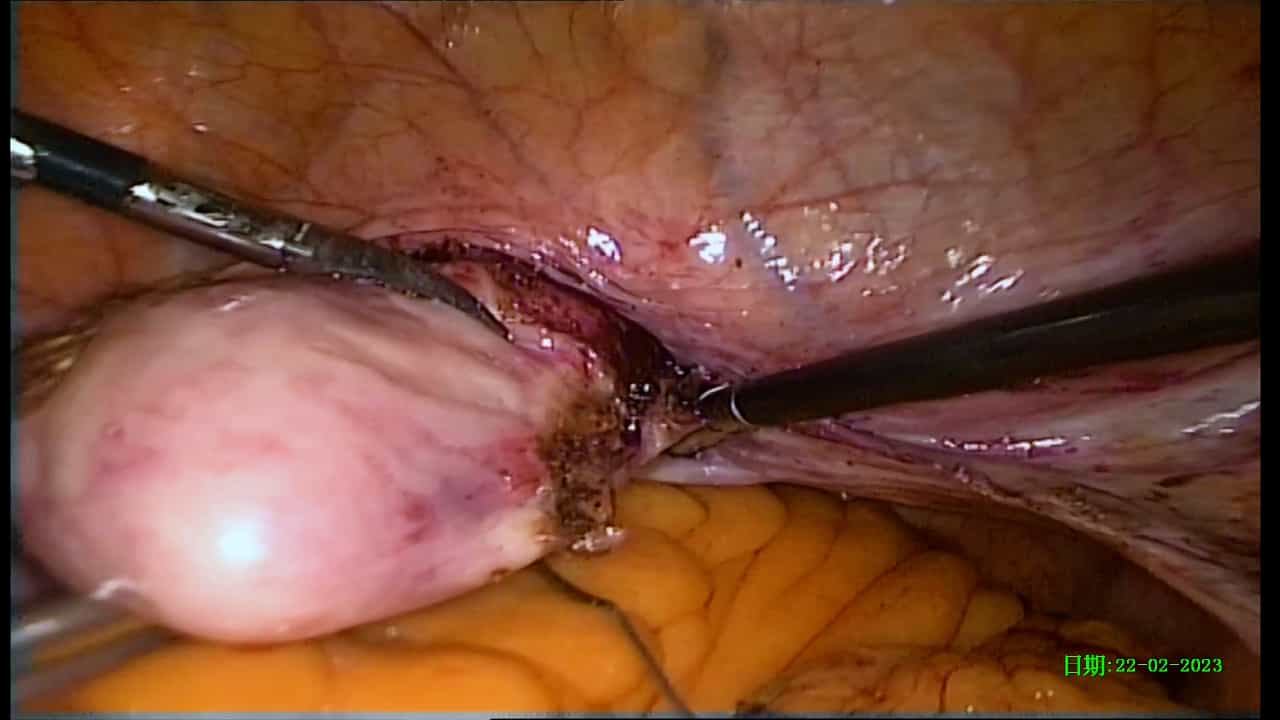
Surgical correction of a chronic puerperal uterine inversion traditionally requires an anterior or posterior cervical incision to relieve the constricting band. This case is only the second reported case of robotic-assisted correction of a chronic puerperal uterine inversion and the first to avoid a cervical incision. The patient was 5 months postpartum and desired future pregnancy. After a laparoscopic Huntington technique was unsuccessful, a vertical hysterotomy was created in the anterior lower uterine segment and extended toward the fundus until the inversion could be relieved. The incision was repaired in 3 layers and a round ligament plication was performed to provide additional support within the pelvis. The patient's symptoms gradually improved during her postoperative course, and ultrasound 2 weeks after the procedure revealed the uterus in anatomic position in the pelvis. With a paucity of reported cases of laparoscopic correction of chronic puerperal uterine inversion, the present case offers a novel surgical approach that maintains cervical integrity and thereby minimizes long-term effects of the procedure on future pregnancies.
Surgical correction of a chronic puerperal uterine inversion traditionally requires an anterior or posterior cervical incision to relieve the constricting band. This case is only the second reported case of robotic-assisted correction of a chronic puerperal uterine inversion and the first to avoid a cervical incision. The patient was 5 months postpartum and desired future pregnancy. After a laparoscopic Huntington technique was unsuccessful, a vertical hysterotomy was created in the anterior lower uterine segment and extended toward the fundus until the inversion could be relieved. The incision was repaired in 3 layers and a round ligament plication was performed to provide additional support within the pelvis. The patient's symptoms gradually improved during her postoperative course, and ultrasound 2 weeks after the procedure revealed the uterus in anatomic position in the pelvis. With a paucity of reported cases of laparoscopic correction of chronic puerperal uterine inversion, the present case offers a novel surgical approach that maintains cervical integrity and thereby minimizes long-term effects of the procedure on future pregnancies.