Related Experiment Video
Updated: Jul 5, 2026
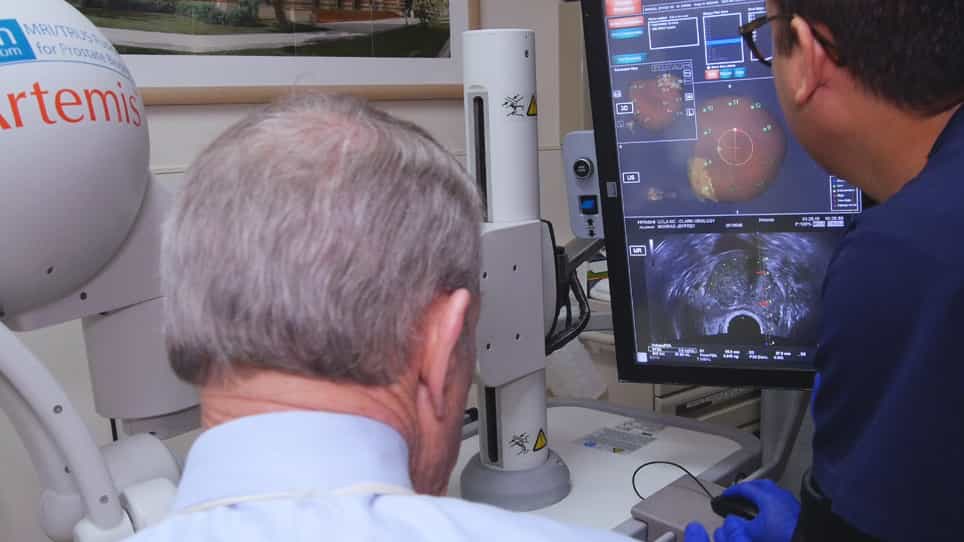

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Positive Margin Location and Prostate Biopsy Route: A Consecutive Cohort Comparison of Transperineal and Transrectal
Abdullah Al-Khanaty1,2, Kieran Sandhu1, Marian S Wettstein2
1Division of Cancer Surgery, Peter MacCallum Cancer Centre, 305 Grattan Street, Melbourne, VIC 3000, Australia.

Abstract:
Background: Transperineal (TP) prostate biopsy is increasingly used due to its superior infectious safety and enhanced sampling of anterior and apical prostate regions. Concerns have been raised that TP biopsy may induce greater post-biopsy fibrosis, particularly at the apex, potentially increasing positive surgical margin (PSM) rates at radical prostatectomy (RP). We evaluated whether biopsy technique influences overall or location-specific PSMs at RP. Methods: We performed a retrospective comparative cohort study of 1027 consecutive men who underwent TR biopsy and TP biopsy at our institution as we transitioned from TR to TP diagnostic technique. Patients from this cohort who were subsequently diagnosed with clinically localised prostate cancer and underwent RP were analysed. Clinical, biopsy, and pathological data were collected; all Gleason scores were standardised to Prognostic Grade Groups. PSMs were defined as tumour at the inked margin and categorised as apical, lateroposterior, or basal. Associations between biopsy technique and PSM outcomes were analysed using uni- and multivariable logistic regression. Results: Among 1027 biopsies, 260 men proceeded to RP, including 114 following TP biopsy and 146 following TR biopsy. Baseline pathological characteristics were similar between groups. Overall PSM rates did not differ between TP and TR cohorts (38.6 percent vs. 41.8 percent, p = 0.604). Margin location was also comparable at the apex (11.9 percent vs. 13.5 percent), lateroposterior (5.4 percent vs. 10.8 percent), and base (4.2 percent vs. 5.8 percent) respectively. In adjusted analyses controlling for age, PSA, grade, tumour stage, nodal status, and surgical approach, biopsy technique was not associated with overall PSMs (OR 0.70; 95 percent CI 0.39-1.24; p = 0.22) or with any location-specific PSMs. Conclusions: TP biopsy did not increase the risk of positive surgical margins at radical prostatectomy, either overall or at the apex. These findings do not support concerns that TP biopsy disrupts apical tissue planes or compromises oncologic outcomes. The results reinforce the safety of TP biopsy as a contemporary diagnostic standard, while highlighting the need for larger prospective studies to confirm these observations.