Related Experiment Video
Updated: Aug 13, 2025


3D-Neuronavigation In Vivo Through a Patient's Brain During a Spontaneous Migraine Headache
Published on: June 2, 2014
Prepregnancy Migraine, Migraine Phenotype, and Risk of Adverse Pregnancy Outcomes
Alexandra C Purdue-Smithe1, Jennifer J Stuart2, Leslie V Farland2
1From the Division of Women's Health (A.C.P.-S., J.J.S., J.W.R.-E., K.R.) and Channing Division of Network Medicine (J.H.K.), Department of Medicine, Brigham and Women's Hospital and Harvard Medical School, Boston, MA; Department of Epidemiology (J.J.S., J.W.R.-E.), Harvard T.H. Chan School of Public Health, Boston; Department of Epidemiology and Biostatistics (L.V.F.), Mel and Enid Zuckerman College of Public Health, University of Arizona, Tucson; Department of Obstetrics and Gynecology (L.V.F.), University of Arizona, College of Medicine, Tucson; and Department of Neurology (A.M.H.), Mass General Hospital and Harvard Medical School, Boston, MA. apurdue-smithe@bwh.harvard.edu.

Background And Objective:
Migraine is a highly prevalent neurovascular disorder among reproductive-aged women. Whether migraine history and migraine phenotype might serve as clinically useful markers of obstetric risk is not clear. The primary objective of this study was to examine associations of prepregnancy migraine and migraine phenotype with risks of adverse pregnancy outcomes.
Methods:
We estimated associations of self-reported physician-diagnosed migraine and migraine phenotype with adverse pregnancy outcomes in the prospective Nurses' Health Study II (1989-2009). Log-binomial and log-Poisson models with generalized estimating equations were used to estimate relative risks (RRs) and 95% CIs for gestational diabetes mellitus (GDM), preeclampsia, gestational hypertension, preterm delivery, and low birthweight.
Results:
The analysis included 30,555 incident pregnancies after cohort enrollment among 19,694 participants without a history of cardiovascular disease, diabetes, or cancer. After adjusting for age, adiposity, and other health and behavioral factors, prepregnancy migraine (11%) was associated with higher risks of preterm delivery (RR = 1.17; 95% CI = 1.05-1.30), gestational hypertension (RR = 1.28; 95% CI = 1.11-1.48), and preeclampsia (RR = 1.40; 95% CI = 1.19-1.65) compared with no migraine. Migraine was not associated with low birthweight (RR = 0.99; 95% CI = 0.85-1.16) or GDM (RR = 1.05; 95% CI = 0.91-1.22). Risk of preeclampsia was somewhat higher among participants with migraine with aura (RR vs no migraine = 1.51; 95% CI = 1.22-1.88) than migraine without aura (RR vs no migraine = 1.30; 95% CI = 1.04-1.61; p-heterogeneity = 0.32), whereas other outcomes were similar by migraine phenotype. Participants with migraine who reported regular prepregnancy aspirin use had lower risks of preterm delivery (<2×/week RR = 1.24; 95% CI = 1.11-1.38; ≥2×/week RR = 0.55; 95% CI = 0.35-0.86; p-interaction < 0.01) and preeclampsia (<2×/week RR = 1.48; 95% CI = 1.25-1.75; ≥2×/week RR = 1.10; 95% CI = 0.62-1.96; p-interaction = 0.39); however, power for these stratified analyses was limited.
Discussion:
Migraine history, and to a lesser extent migraine phenotype, appear to be important considerations in obstetric risk assessment and management. Future research should determine whether aspirin prophylaxis may be beneficial for preventing adverse pregnancy outcomes among pregnant individuals with a history of migraine.
More Related Videos
 05:49
Author Spotlight: Deciphering Electrical Networks Behind Complex Brain Activities and Disorders
Published on: November 1, 2024
 06:39
Using a Murine Model of Psychosocial Stress in Pregnancy as a Translationally Relevant Paradigm for Psychiatric Disorders in Mothers and Infants
Published on: June 13, 2021
Related Concept Videos
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:24
Disorders of the Female Reproductive System
 01:07
Teratogenicity
 01:30
Bulimia Nervosa
 02:57
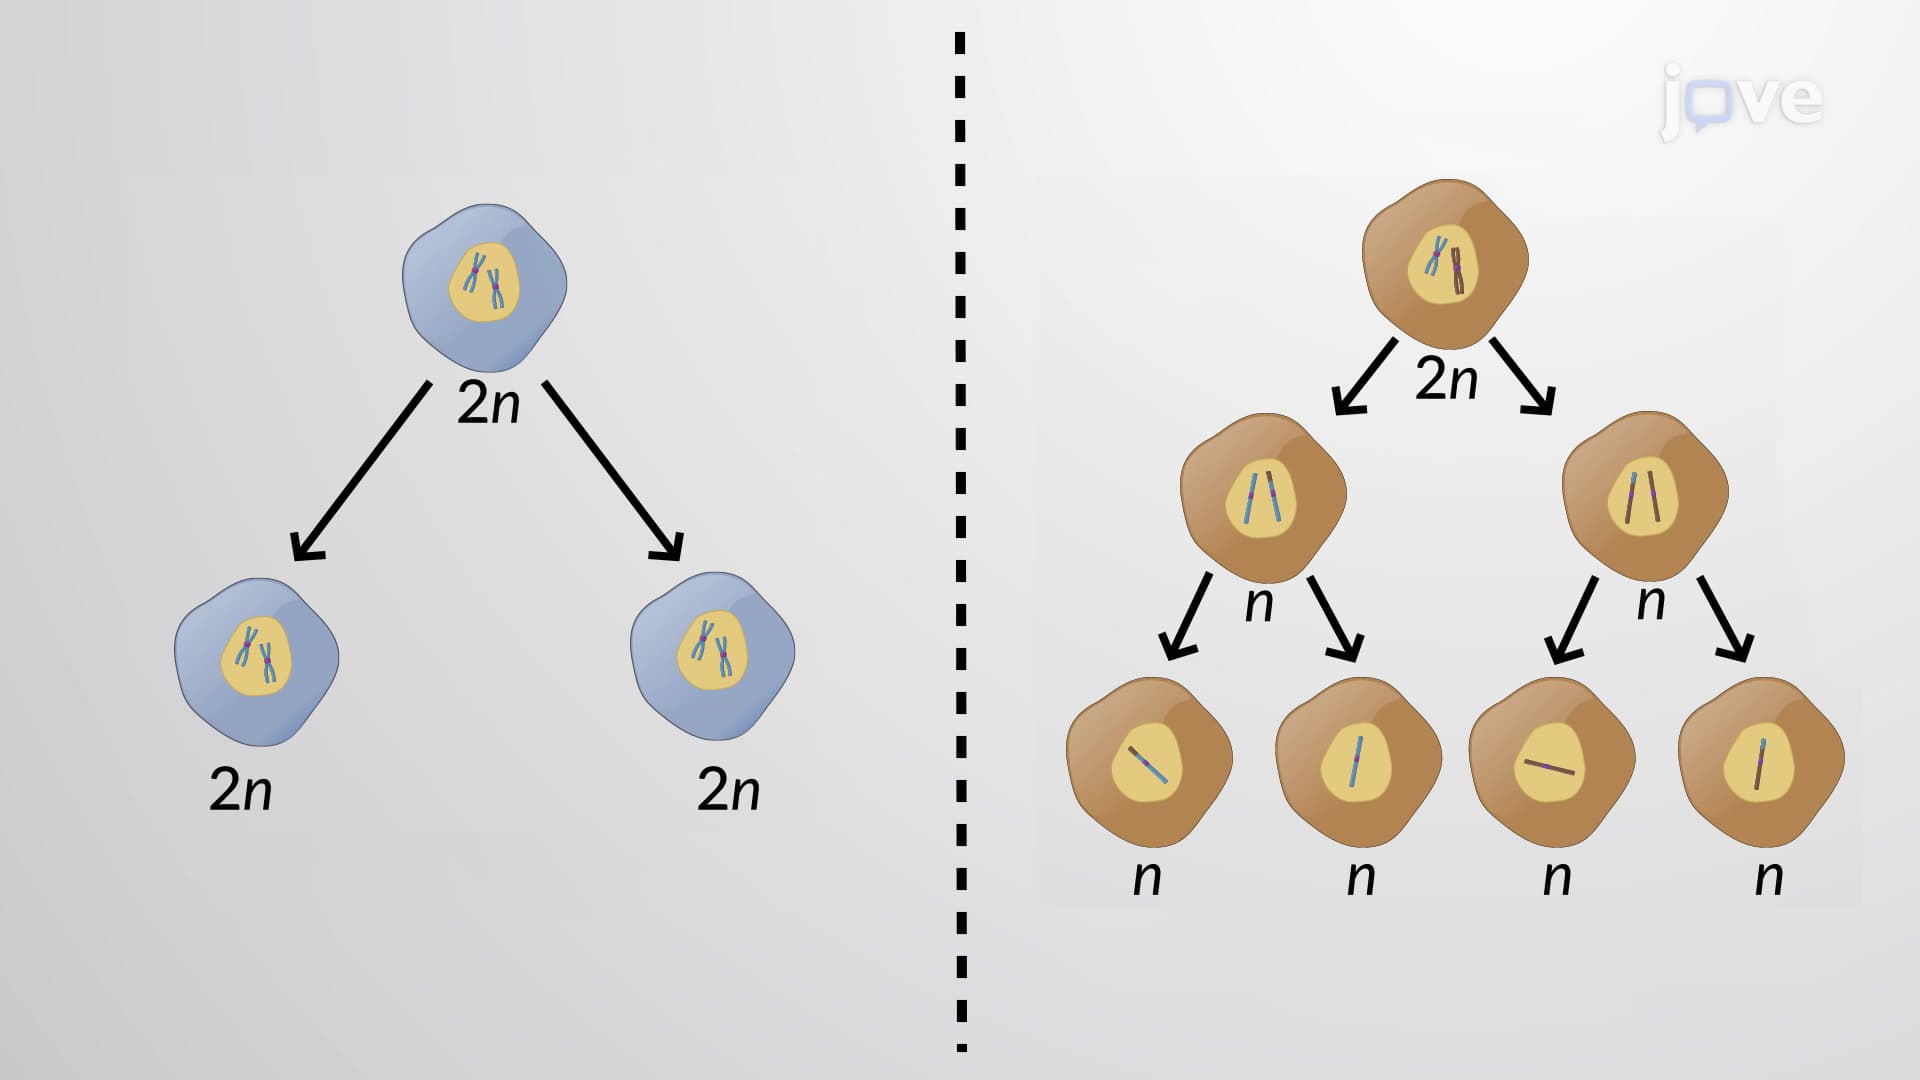
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...