Related Experiment Video
Updated: Aug 13, 2025


Author Spotlight: Advancements in Retroperitoneal Approach for Necrotizing Pancreatitis
Published on: March 15, 2024
[Diagnosis and treatment of blunt high-grade pancreatic trauma]
1Department of Hepatobiliary Pancreatic Surgery, Changhai Hospital, Naval Military Medical University, Shanghai 200433, China.

Abstract:
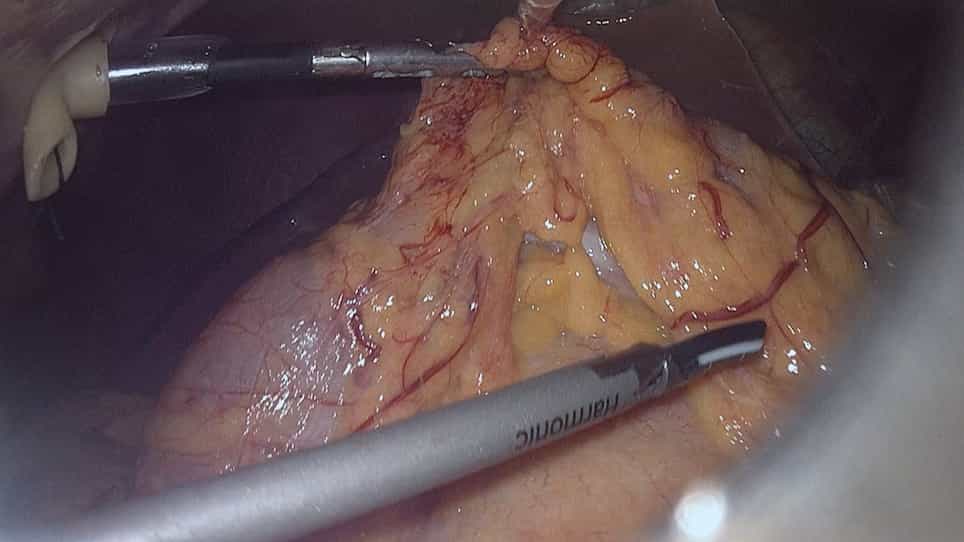
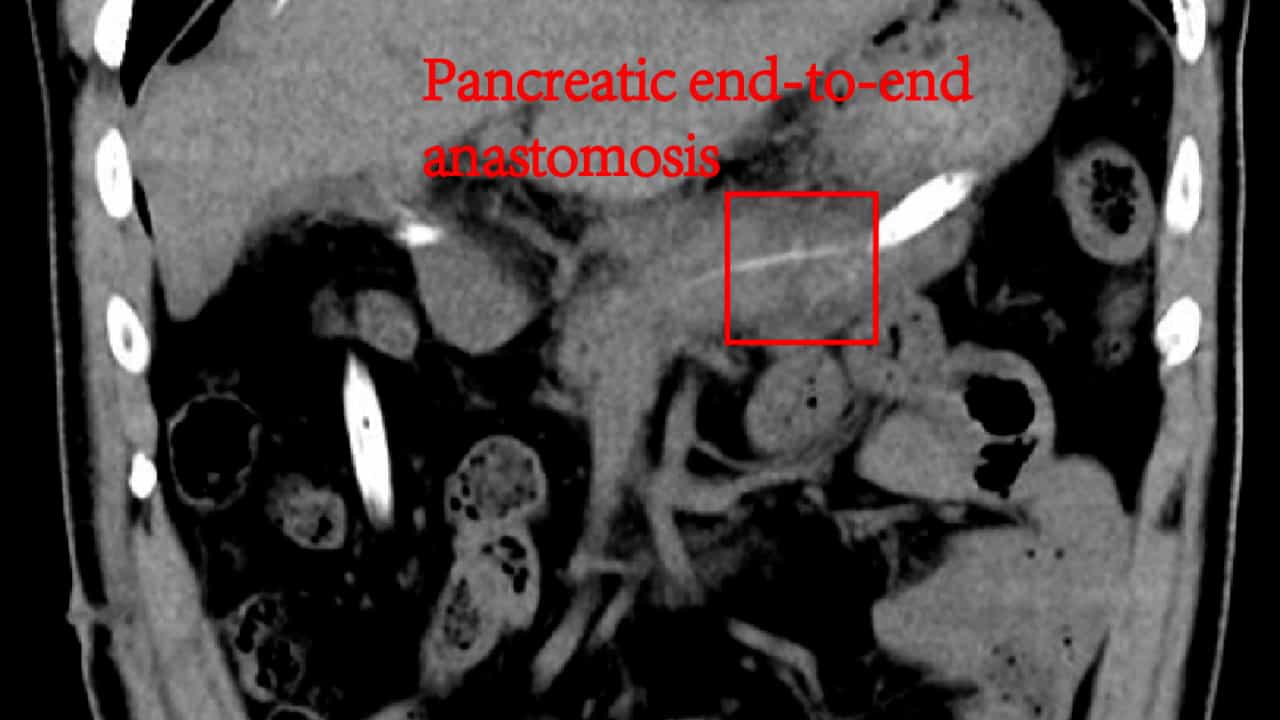
The clinical data of 20 patients with blunt high-grade pancreatic trauma who were admitted to the Department of Hepatobiliary and Pancreatic Surgery of Changhai Hospital Affiliated to Naval Military Medical University from December 2003 to February 2022 were retrospectively analyzed. There were 15 males and 5 females with a median age of 39 years (range: 14-54 years). The degree of pancreatic injury was graded according to the American Association for the Surgery of Trauma (AAST) scale, including 10 cases of grade Ⅲ (50%), 8 cases of grade Ⅳ (40%), and 2 cases of grade Ⅴ (10%). Then, the strategy of diagnosis and treatment for blunt high-grade pancreatic trauma was summarized. The diagnostic rate of CT was 78.9%. Finally, 17 cases (85%) were cured and 3 cases (15%) died. Among the 10 patients with grade Ⅲ pancreatic injury, 7 cases received distal pancreatectomy and splenectomy, 1 case received distal pancreatectomy with spleen preserved, 1 case received pancreatic duct stent placement under endoscopic retrograde cholangiopancreatography (ERCP) and percutaneous catheter drainage (PCD), and 1 case received only PCD. Among 8 cases of grade Ⅳ, 3 cases underwent Roux-en-Y pancreaticojejunostomy, 1 case received distal pancreatectomy and splenectomy, 1 case underwent distal pancreatectomy with spleen preserved, 2 cases received necrotic tissue removal+external drainage of pancreatic duct+abdominal drainage, and 1 case received exploratory laparotomy and gauze packing hemostasis. For 2 cases of grade Ⅴ, 1 underwent pylorus preserving pancreaticoduodenectomy, and the other case underwent pancreaticoduodenectomy combined with right hemicolectomy and splenectomy. Therefore, the treatment of blunt high-grade pancreatic trauma should follow the individualized treatment strategy, pay attention to the control of bleeding, extensive external drainage, appropriate debridement and resection and rational application of damage control surgery, select appropriate patients for conservative treatment, and ultimately benefit the patient.
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:26
Endoscopic Procedures V: ERCP
Patient...