Related Experiment Video
Updated: Aug 12, 2025

Non-invasive Optical Measurement of Cerebral Metabolism and Hemodynamics in Infants
Published on: March 14, 2013
Automated oxygen control for very preterm infants and neurodevelopmental outcome at 2 years-a retrospective cohort
Hylke H Salverda1, N Nathalie J Oldenburger2, Monique Rijken2
1Department of Paediatrics, Division of Neonatology, Willem-Alexander Children's Hospital, Leiden University Medical Center, PO Box 9600, Leiden, the Netherlands. H.H.Salverda@lumc.nl.

Insights
Automated oxygen control (AOC) in preterm infants did not significantly change neurodevelopmental outcomes at two years. This study found no difference in mortality or severe impairment after implementing AOC as standard NICU care.
Area of Science:
- Neonatal care
- Pediatric neurodevelopment
- Respiratory support
Background:
- Hypoxemia and hyperoxaemia in preterm infants are linked to neurodevelopmental impairment.
- Automated oxygen control (AOC) may improve oxygen saturation stability.
- Faster resolution of oxygen events could reduce long-term impairment.
Purpose of the Study:
- To compare neurodevelopmental outcomes at two years of age in preterm infants before and after the implementation of automated oxygen control (AOC).
- To assess the impact of AOC on mortality, severe and mild-moderate neurodevelopmental impairment, and other developmental outcomes.
Main Methods:
- A cohort study comparing preterm infants (24-29 weeks gestational age) before (2012-2015) and after (2015-2018) AOC implementation.
- Neurodevelopmental outcomes, including mortality, severe/mild-moderate impairment, cerebral palsy, and behavioral scores, were assessed at two years.
- A total of 581 infants were included (289 pre-AOC, 292 post-AOC).
Main Results:
- No statistically significant difference was found in the composite outcome of mortality or severe neurodevelopmental impairment (17.9% pre-AOC vs. 24.0% post-AOC, p=0.12).
- Secondary outcomes including mild-moderate NDI, Bayley-III scores, and cerebral palsy (GMFCS) also showed no significant differences.
- Parent-reported readmissions were less frequent in the post-AOC group.
Conclusions:
- Implementation of automated oxygen control as standard care in a NICU did not lead to a statistically significant difference in neurodevelopmental outcomes at two years of age for preterm infants.
- While AOC did not alter primary neurodevelopmental outcomes, it was associated with fewer readmissions.
Abstract:
Faster resolution of hypoxaemic or hyperoxaemic events in preterm infants may reduce long-term neurodevelopmental impairment. Automatic titration of inspiratory oxygen increases time within the oxygen saturation target range and may provide a more prompt response to hypoxic and hyperoxic events. We assessed routinely performed follow-up at 2 years of age after the implementation of automated oxygen control (AOC) as standard care and compared this with a historical cohort. Neurodevelopmental outcomes at 2 years of age were compared for infants born at 24-29 weeks gestational age before (2012-2015) and after (2015-2018) the implementation of AOC as standard of care. The primary outcome was a composite outcome of either mortality or severe neurodevelopmental impairment (NDI), and other outcomes assessed were mild-moderate NDI, Bayley-III composite scores, cerebral palsy GMFCS, and CBCL problem behaviour scores. A total of 289 infants were included in the pre-AOC epoch and 292 in the post-AOC epoch. Baseline characteristics were not significantly different. Fifty-one infants were lost to follow-up (pre-AOC 6.9% (20/289), post-implementation 10.6% (31/292). The composite outcome of mortality or severe NDI was observed in 17.9% pre-AOC (41/229) vs. 24.0% (47/196) post-AOC (p = 0.12). No significant differences were found for the secondary outcomes such as mild-moderate NDI, Bayley-III composite scores, cerebral palsy GMFCS, and problem behaviour scores, with the exception of parent-reported readmissions until the moment of follow-up which was less frequent post-AOC than pre-AOC.
Conclusion:
In this cohort study, the implementation of automated oxygen control in our NICU as standard of care for preterm infants led to no statistically significant difference in neurodevelopmental outcome at 2 years of age.
What Is Known:
• Neurodevelopmental outcome is linked to hypoxemia, hyperoxaemia and choice of SpO2 target range. • Automated titration of inspired oxygen may provide a faster resolution of hypoxaemic and hyperoxaemic events.
What Is New:
• This cohort study did not find a significant difference in neurodevelopmental outcome at two years of age after implementing automated oxygen control as standard of care.

Related Concept Videos
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:18
Neural Control of Respiration
Respiratory Centers in the Brainstem
Two primary areas comprise the respiratory center: the medullary respiratory center in the medulla oblongata and the pontine respiratory group in the pons. The...
 01:22
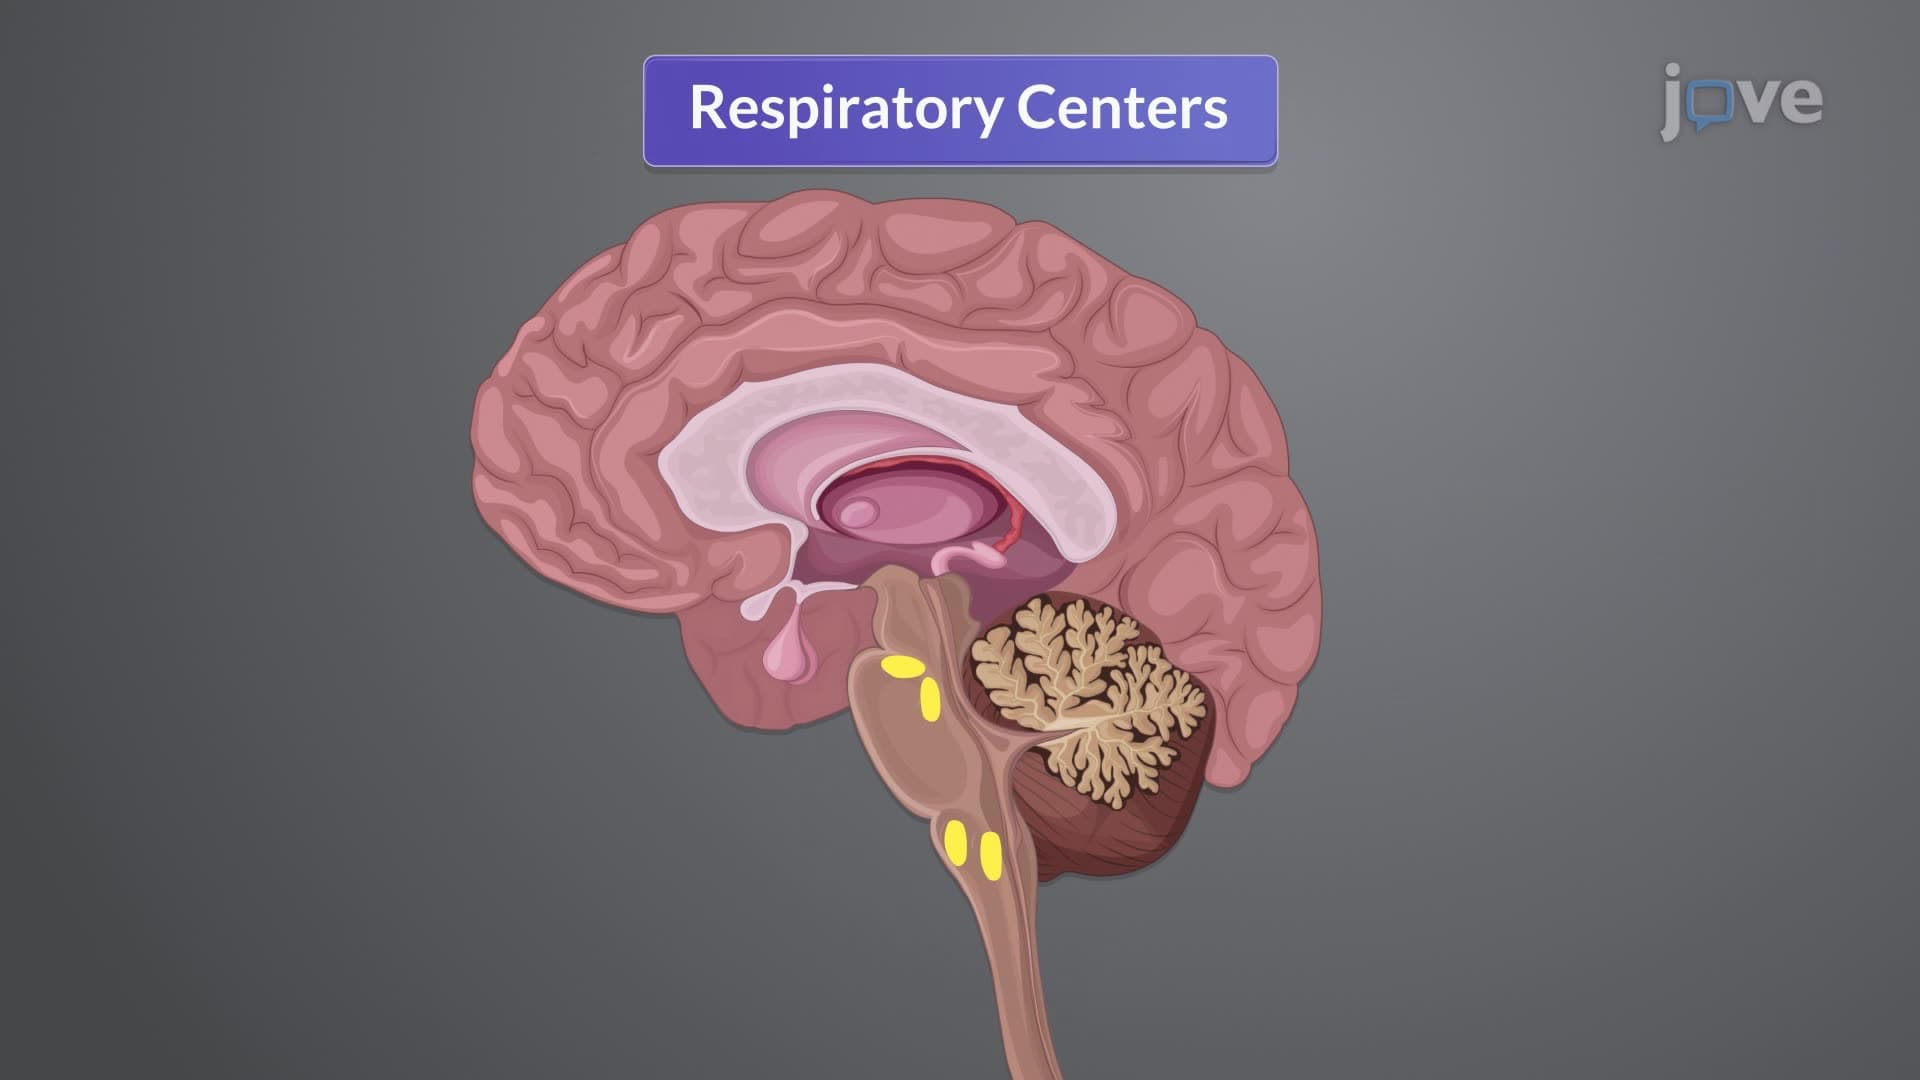
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers: