Related Experiment Video
Updated: Aug 11, 2025
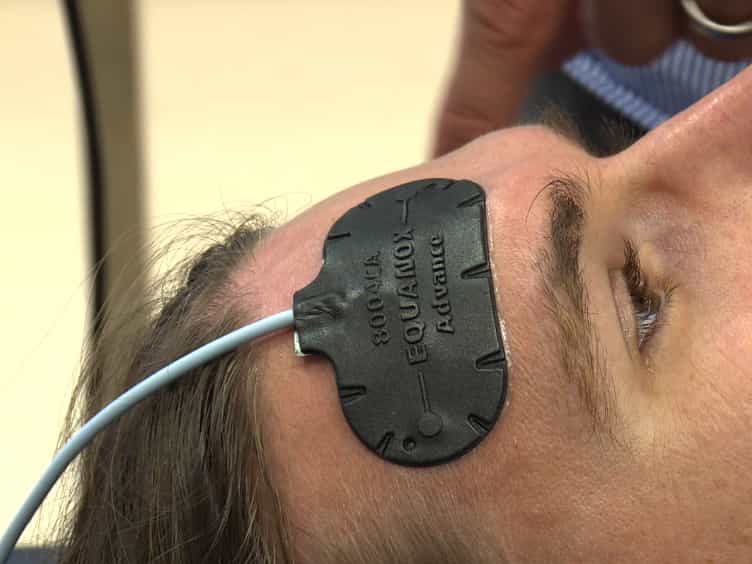

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Oral Oxycodone-Induced Respiratory Depression During Normocapnia and Hypercapnia: A Pharmacokinetic-Pharmacodynamic
Marieke Hellinga1, Marijke Hyke Algera1, Erik Olofsen1
1Department of Anesthesiology, Leiden University Medical Center, Leiden, The Netherlands.

Abstract:
The widely prescribed opioid oxycodone may cause lethal respiratory depression. We compared the effects of oxycodone on breathing and antinociception in healthy young volunteers. After pharmacokinetic/pharmacodynamic (PK/PD) modeling, we constructed utility functions to combine the wanted and unwanted end points into a single function. We hypothesized that the function would be predominantly negative over the tested oxycodone concentration range. Twenty-four male and female volunteers received 20 (n = 12) or 40 (n = 12) mg oral oxycodone immediate-release tablets. Hypercapnic ventilatory responses (visit 1) or responses to 3 nociceptive assays (pain pressure, electrical, and thermal tests; visit 2) were measured at regular intervals for 7 hours. the PK/PD analyses, that included carbon dioxide kinetics, stood at the basis of the utility function: probability of antinociception minus probability of respiratory depression. Oxycodone had rapid onset/offset times (30-40 minutes) with potency values (effect-site concentration causing 50% of effect) ranging from 0.05 to 0.13 ng/mL for respiratory variables obtained at hypercapnia and antinociceptive responses. Ventilation at an extrapolated end-tidal carbon dioxide partial pressure of 55 mmHg, was used for creation of 3 utility functions, one for each of the nociceptive tests. Contrary to expectation, the utility functions were close to zero or positive over the clinical oxycodone concentration range. The similar or better likelihood for antinociception relative to respiratory depression may be related to oxycodone's receptor activation profile or to is high likeability that possibly alters the modulation of nociceptive input. Oxycodone differs from other μ-opioids, such as fentanyl, that have a consistent negative utility.


Related Concept Videos
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal...
 01:15
Model Approaches for Pharmacokinetic Data: Physiological Models
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant,...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:30
Acute Respiratory Failure-III
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...