

Rule-out of non-ST-segment elevation acute coronary syndrome by a single, pre-hospital troponin measurement: a
Cyril Camaro1, Goaris W A Aarts1, Eddy M M Adang2
1Department of Cardiology, Radboud University Medical Centre, P.O. Box 9101, Geert Grooteplein Zuid 10, 6525 GA Nijmegen, Gelderland, The Netherlands.

Aims:
Patients with suspected non-ST-segment elevation acute coronary syndrome (NSTE-ACS) are routinely transferred to the emergency department (ED). A clinical risk score with point-of-care (POC) troponin measurement might enable ambulance paramedics to identify low-risk patients in whom ED evaluation is unnecessary. The aim was to assess safety and healthcare costs of a pre-hospital rule-out strategy using a POC troponin measurement in low-risk suspected NSTE-ACS patients.
Methods And Results:
This investigator-initiated, randomized clinical trial was conducted in five ambulance regions in the Netherlands. Suspected NSTE-ACS patients with HEAR (History, ECG, Age, Risk factors) score ≤3 were randomized to pre-hospital rule-out with POC troponin measurement or direct transfer to the ED. The sample size calculation was based on the primary outcome of 30-day healthcare costs. Secondary outcome was safety, defined as 30-day major adverse cardiac events (MACE), consisting of ACS, unplanned revascularization or all-cause death. : A total of 863 participants were randomized. Healthcare costs were significantly lower in the pre-hospital strategy (€1349 ± €2051 vs. €1960 ± €1808) with a mean difference of €611 [95% confidence interval (CI): 353-869; P < 0.001]. In the total population, MACE were comparable between groups [3.9% (17/434) in pre-hospital strategy vs. 3.7% (16/429) in ED strategy; P = 0.89]. In the ruled-out ACS population, MACE were very low [0.5% (2/419) vs. 1.0% (4/417)], with a risk difference of -0.5% (95% CI -1.6%-0.7%; P = 0.41) in favour of the pre-hospital strategy.
Conclusion:
Pre-hospital rule-out of ACS with a POC troponin measurement in low-risk patients significantly reduces healthcare costs while incidence of MACE was low in both strategies.
Trial Registration:
Clinicaltrials.gov identifier NCT05466591 and International Clinical Trials Registry Platform id NTR 7346.


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:26
Exercise Stress Test
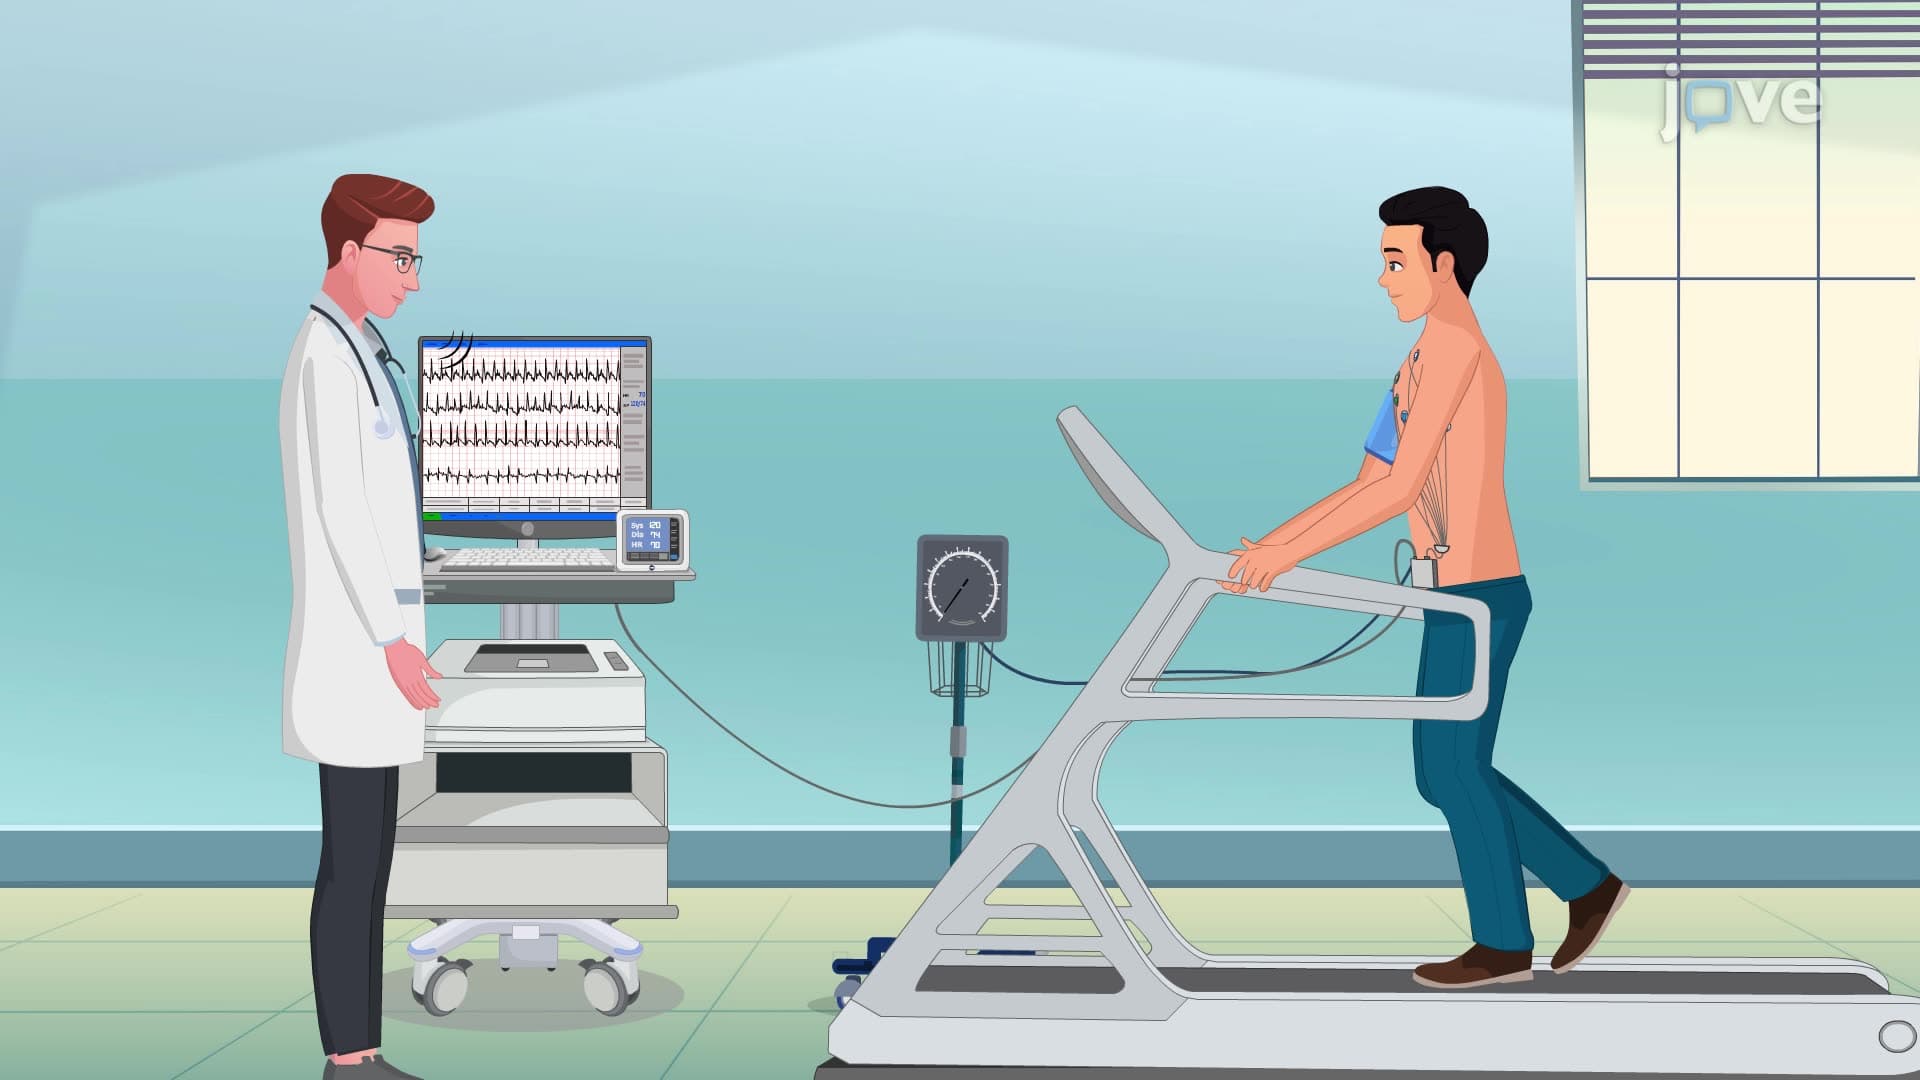
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:28
Acute Coronary Syndrome IV: Interprofessional Care