Related Experiment Video
Updated: Aug 10, 2025
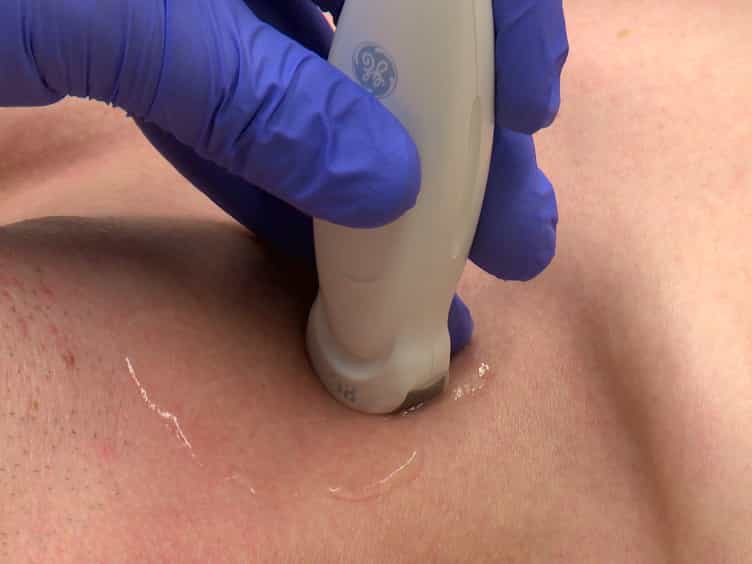
The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Malposition of the central venous catheter secondary to accessory hemiazygos vein variant
Haidar Hajeh1, Austin Garcia2, Shikha Mishra1
1UCLA - David Geffen School of Medicine - Kern Medical Center, Bakersfield, CA, USA.

A 36-year-old female with sickle cell disease presented with sickle cell pain crisis. After failure to establish peripheral venous access, an internal jugular central venous catheter (CVC) was placed. Confirmation of internal jugular cannulation was performed with bedside ultrasound. A confirmatory chest X-ray revealed an unusual position of the catheter, taking a course inferiorly, making a loop and remaining on the left side of the mediastinum. A lateral view was done and revealed that the catheter passed inferiorly through the internal jugular vein then posteriorly and inferiorly giving the looped appearance. This is better delineated on a sagittal view CT scan showing the tip of the catheter terminating in the accessory hemiazygos vein. This unusual course is due to a variant of the accessory hemiazygos vein which is connected to the left superior intercostal vein. This creates a lower resistance pathway for the CVC which passes from the internal jugular vein, down the left superior intercostal vein (instead of the left brachiocephalic vein) and into the accessory hemiazygos vein. Discussion: The correct tip placement of an internal jugular CVC terminates in the superior vena cava just above the cardiac silhouette. In 1%-2% of individuals, a connection between the accessory hemiazygos and the left superior intercostal vein is present. Rare cases are discovered incidentally during CVC placement. The diameter of the accessory hemiazygos vein is less than half of that of the superior vena cava. The catheter should not be used as central venous access and removal is recommended. Malpositioning of central catheters is unpredictable but can be easily avoided by using intraprocedural methods to confirm tip position. Such modalities include intracavitary ECG or ultrasound with agitated saline injection as described in the SIC (Safe Insertion of Centrally Inserted Central Catheters) protocol.
A 36-year-old female with sickle cell disease presented with sickle cell pain crisis. After failure to establish peripheral venous access, an internal jugular central venous catheter (CVC) was placed. Confirmation of internal jugular cannulation was performed with bedside ultrasound. A confirmatory chest X-ray revealed an unusual position of the catheter, taking a course inferiorly, making a loop and remaining on the left side of the mediastinum. A lateral view was done and revealed that the catheter passed inferiorly through the internal jugular vein then posteriorly and inferiorly giving the looped appearance. This is better delineated on a sagittal view CT scan showing the tip of the catheter terminating in the accessory hemiazygos vein. This unusual course is due to a variant of the accessory hemiazygos vein which is connected to the left superior intercostal vein. This creates a lower resistance pathway for the CVC which passes from the internal jugular vein, down the left superior intercostal vein (instead of the left brachiocephalic vein) and into the accessory hemiazygos vein. Discussion: The correct tip placement of an internal jugular CVC terminates in the superior vena cava just above the cardiac silhouette. In 1%-2% of individuals, a connection between the accessory hemiazygos and the left superior intercostal vein is present. Rare cases are discovered incidentally during CVC placement. The diameter of the accessory hemiazygos vein is less than half of that of the superior vena cava. The catheter should not be used as central venous access and removal is recommended. Malpositioning of central catheters is unpredictable but can be easily avoided by using intraprocedural methods to confirm tip position. Such modalities include intracavitary ECG or ultrasound with agitated saline injection as described in the SIC (Safe Insertion of Centrally Inserted Central Catheters) protocol.


Related Concept Videos
 01:19
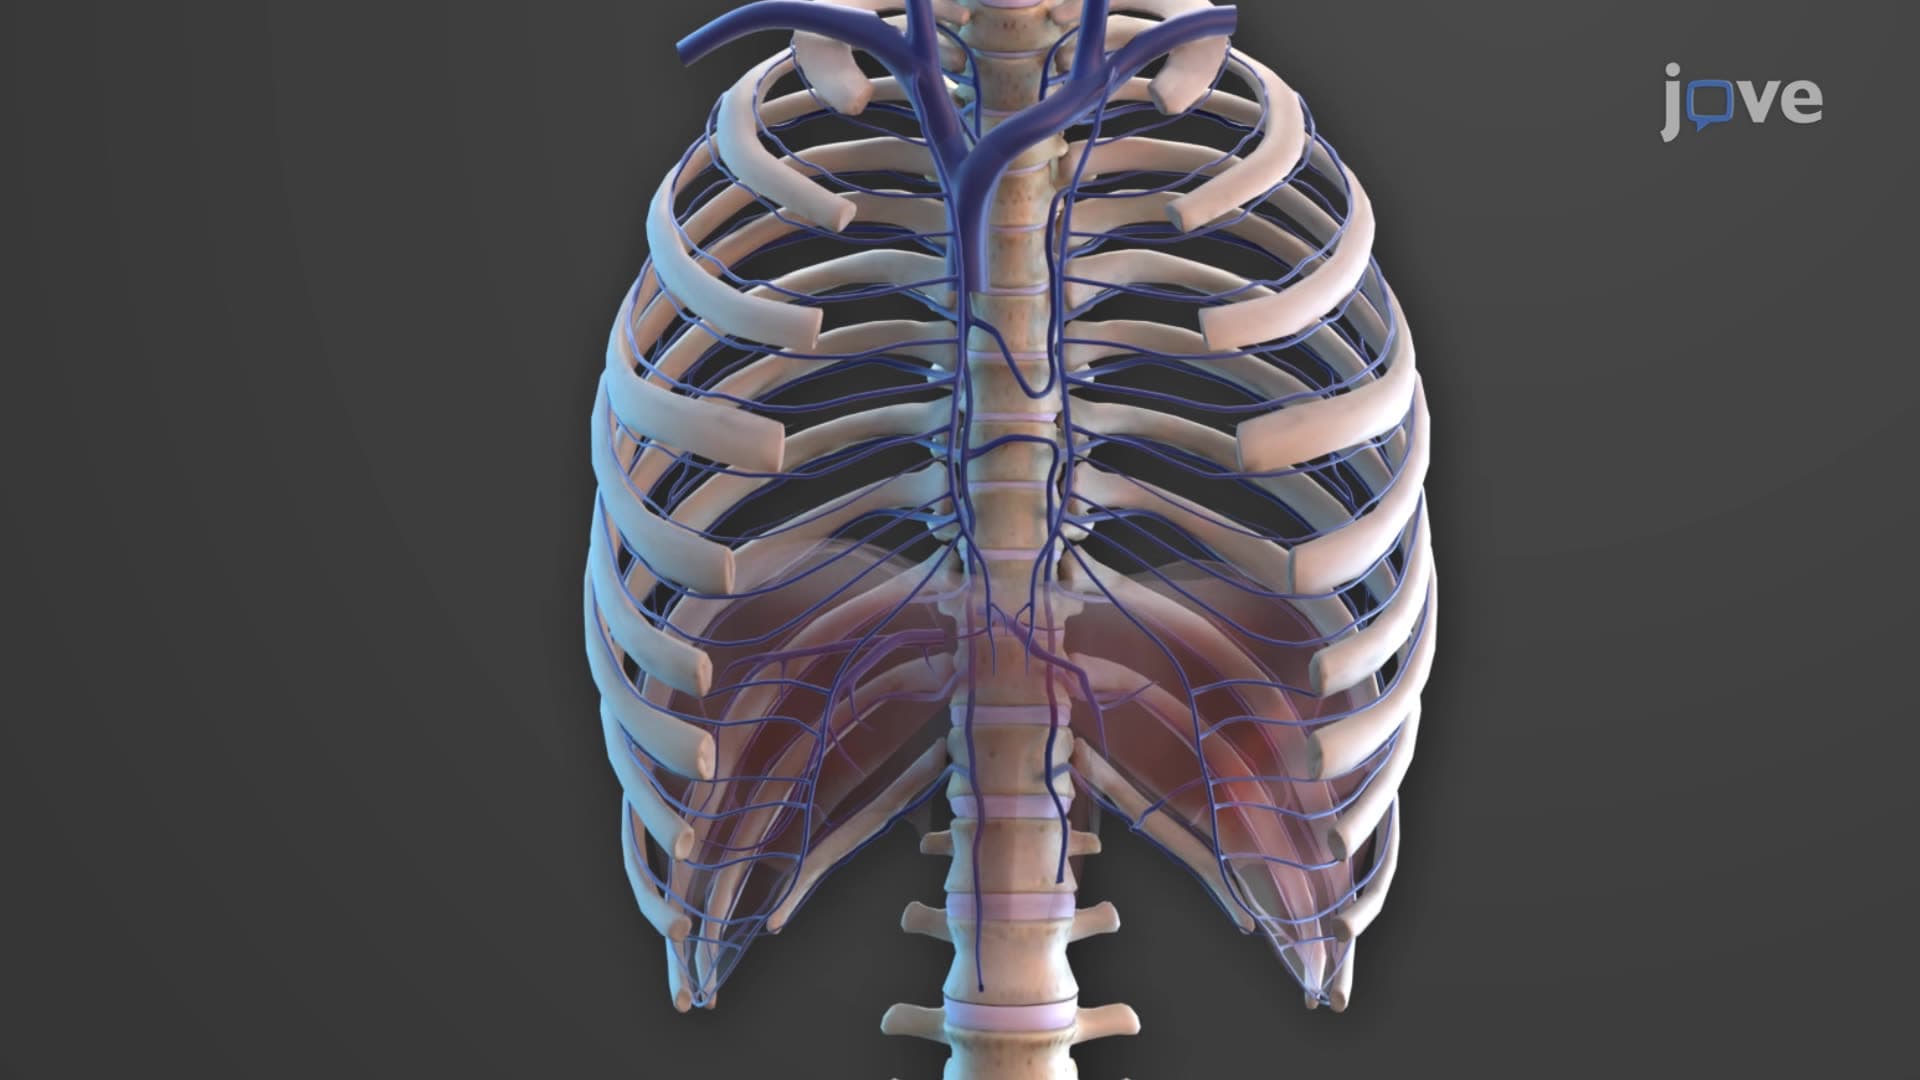
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:18
Veins of the Abdomen and Pelvis
The inferior vena cava is fed by numerous smaller veins. The lumbar veins, for instance, drain the posterior abdominal wall, emptying both directly into the inferior vena cava and into the...
 01:17
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:26
Varicose Veins I: Introduction