Related Experiment Video
Updated: Aug 10, 2025
Surgical Techniques for Catheter Placement and 5/6 Nephrectomy in Murine Models of Peritoneal Dialysis
Published on: July 19, 2018
Pharmacokinetics and pharmacodynamics of sacubitril/valsartan in peritoneal dialysis patients
1Kidney Research Institute, Department of Nephrology, West China Hospital of Sichuan University, Sichuan, Chengdu, China.

Background:
There is little information on the pharmacokinetics and pharmacodynamics of sacubitril/valsartan (SV) in patients undergoing peritoneal dialysis (PD) complicated with hypertension or heart failure (HF). This study was designed to evaluate the pharmacokinetics and pharmacodynamics of SV in PD patients with complications of hypertension or HF.
Methods:
This was an open-label and cross-sectional study investigating PD patients diagnosed with hypertension or New York Heart Association Class II-IV HF. The concentrations of valsartan, sacubitril and sacubitrilat (LBQ657) were measured by ultra-performance liquid chromatography tandem mass spectrometry in plasma, urine and peritoneal dialysate samples. Pharmacodynamics were evaluated by comparing changes in mean sitting systolic blood pressure (msSBP), mean sitting diastolic blood pressure (msDBP), mean sitting heart rate, N-terminal-pro B-type natriuretic peptide (NT-proBNP) and left ventricular ejection fraction (LVEF).
Results:
Forty patients with PD were enrolled including 27 (67.5%) patients with hypertension, 4 (10%) patients with HF and 9 (22.5%) patients with both hypertension and HF. This study included three treatment cohorts: 50 mg twice daily (BID), 100 mg once daily and 100 mg BID. The plasma maximum drug concentrations in the 100 mg BID group were 1995 ± 1499 ng/mL for valsartan, 171 ± 148 ng/mL for sacubitril and 13 686 ± 7418 ng/mL for LBQ657. The 24-h recovery rate of LBQ657 was 3.77% in urine and 2.23% in peritoneal dialysate. After taking SV, msSBP and msDBP decreased by 19.25 ± 10.32 mmHg and 10.10 ± 8.00 mmHg from baseline, respectively. NT-proBNP decreased by 1436.50 (0.00-18 198.00) from baseline, while LVEF increased by 5.00 (-0.25 to 9.25) from baseline after SV treatment.
Conclusions:
PD and residual renal function contributed only to a minor degree to the elimination of LBQ657. Additionally, a dose of 100 mg BID SV is safe and effective in patients with PD with complications of hypertension or HF.

Related Concept Videos
 01:28
Renal Drug Excretion: Tubular Secretion
 01:06
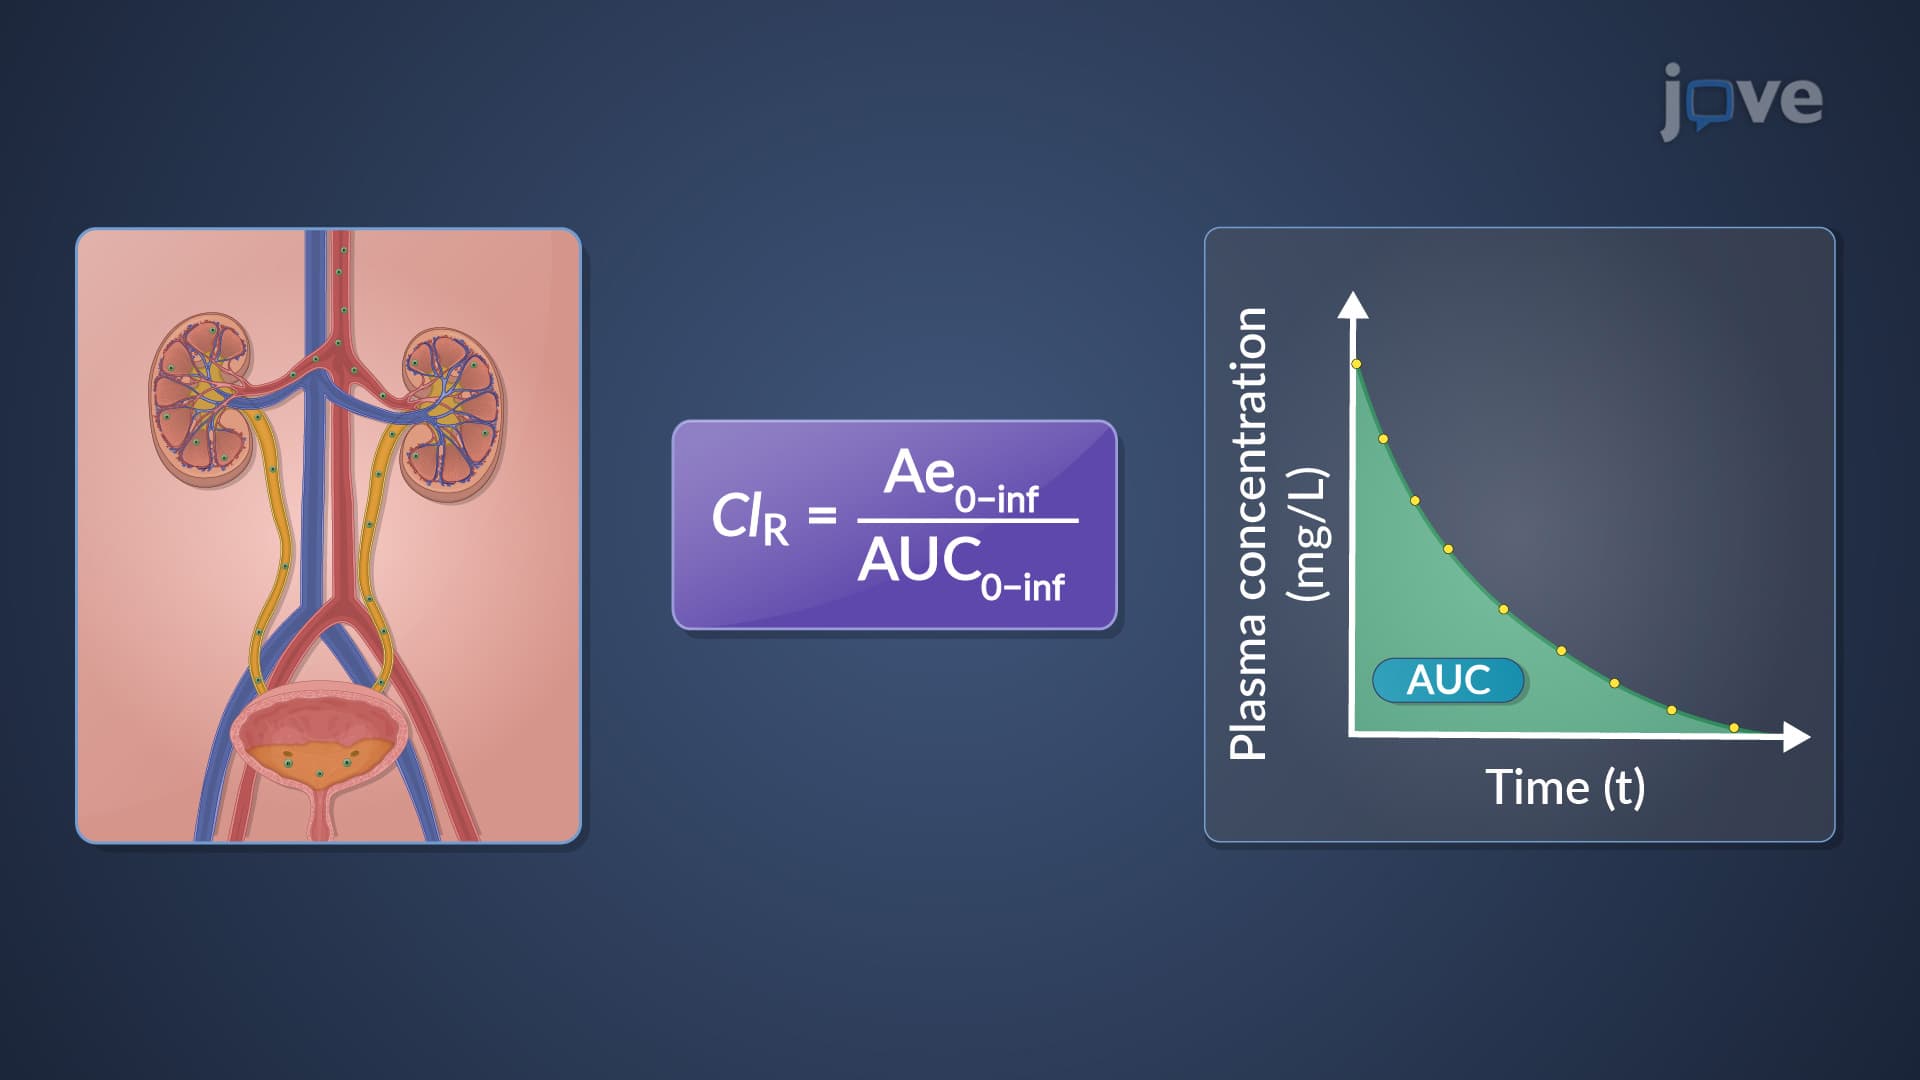
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:31
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...