Related Experiment Video
Updated: Aug 8, 2025


Ischemia-reperfusion Model of Acute Kidney Injury and Post Injury Fibrosis in Mice
Published on: August 9, 2013
Quantitative Consideration of Clinical Increases in Serum Creatinine Caused by Renal Transporter Inhibition
Tomohisa Nakada1, Toshiyuki Kudo1, Kiyomi Ito2
1Sohyaku Innovative Research Division, Mitsubishi Tanabe Pharma Corporation, Yokohama, Japan (T.N.) and Research Institute of Pharmaceutical Sciences, Musashino University, Tokyo, Japan (T.K., K.I.).

Abstract:
Creatinine is a common biomarker of renal function and is secreted in the renal tubular cells via drug transporters, such as organic cation transporter 2 and multidrug and toxin extrusion (MATE) 1/2-K. To differentiate between drug-induced acute kidney injury (AKI) and drug interactions through the renal transporter, it has been examined whether these transporter inhibitions quantitatively explained increases in serum creatinine (SCr) at their clinically relevant concentrations using drugs without any changes in renal function. For such renal transporter inhibitors and recently approved tyrosine kinase inhibitors (TKIs), this mini-review describes clinical increases in SCr and inhibitory potentials against the renal transporters. Most cases of SCr elevations can be explained by considering the renal transporter inhibitions based on unbound maximum plasma concentrations, except for drugs associated with obvious changes in renal function. SCr increases for cobicistat, dolutegravir, and dronedarone, and some TKIs were significantly underestimated, and these underestimations were suggested to be associated with low plasma unbound fractions. Sensitivity analysis of SCr elevations regarding inhibitory potentials of MATE1/2-K demonstrated that typical inhibitors such as cimetidine, DX-619, pyrimethamine, and trimethoprim could give false interpretations of AKI according to the criteria based on relative or absolute levels of SCr elevations. Recent progress and current challenges of physiologically-based pharmacokinetics modeling for creatinine disposition were also summarized. Although it should be noted for the potential impact of in vitro assay designs on clinical translatability of transporter inhibitions data, mechanistic approaches could support decision-making in clinical development to differentiate between AKI and creatinine-drug interactions. SIGNIFICANCE STATEMENT: Serum creatinine (SCr) is widely used as an indicator of kidney function, but it increases due to inhibitions of renal transporters, such as multidrug and toxin extrusion protein 1/2-K despite no functional changes in the kidney. Such SCr elevations were quantitatively explained by renal transporter inhibitions except for some drugs with high protein binding. The present analysis demonstrated that clinically relevant inhibitors of the renal transporters could cause SCr elevations above levels corresponding to acute kidney injury criteria.

Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:08
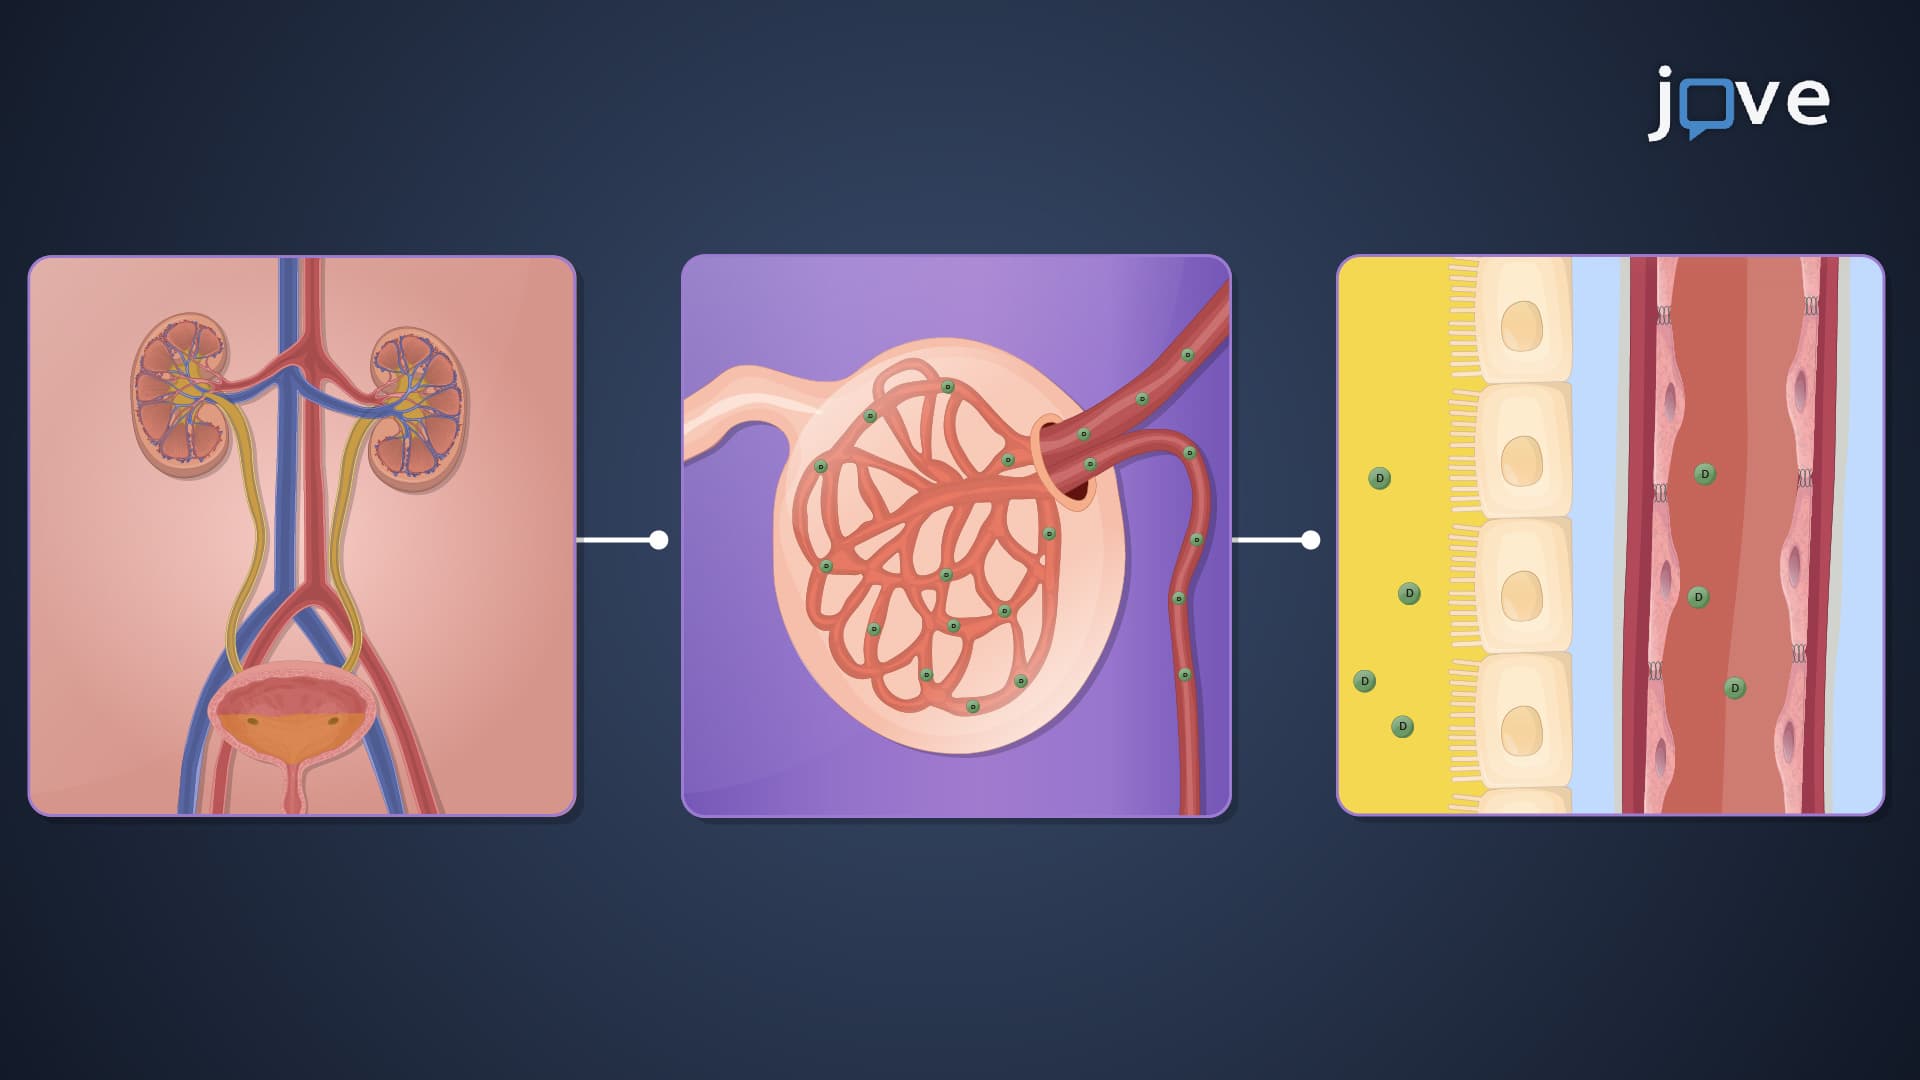
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Serum Studies: Renal Function Tests
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:06
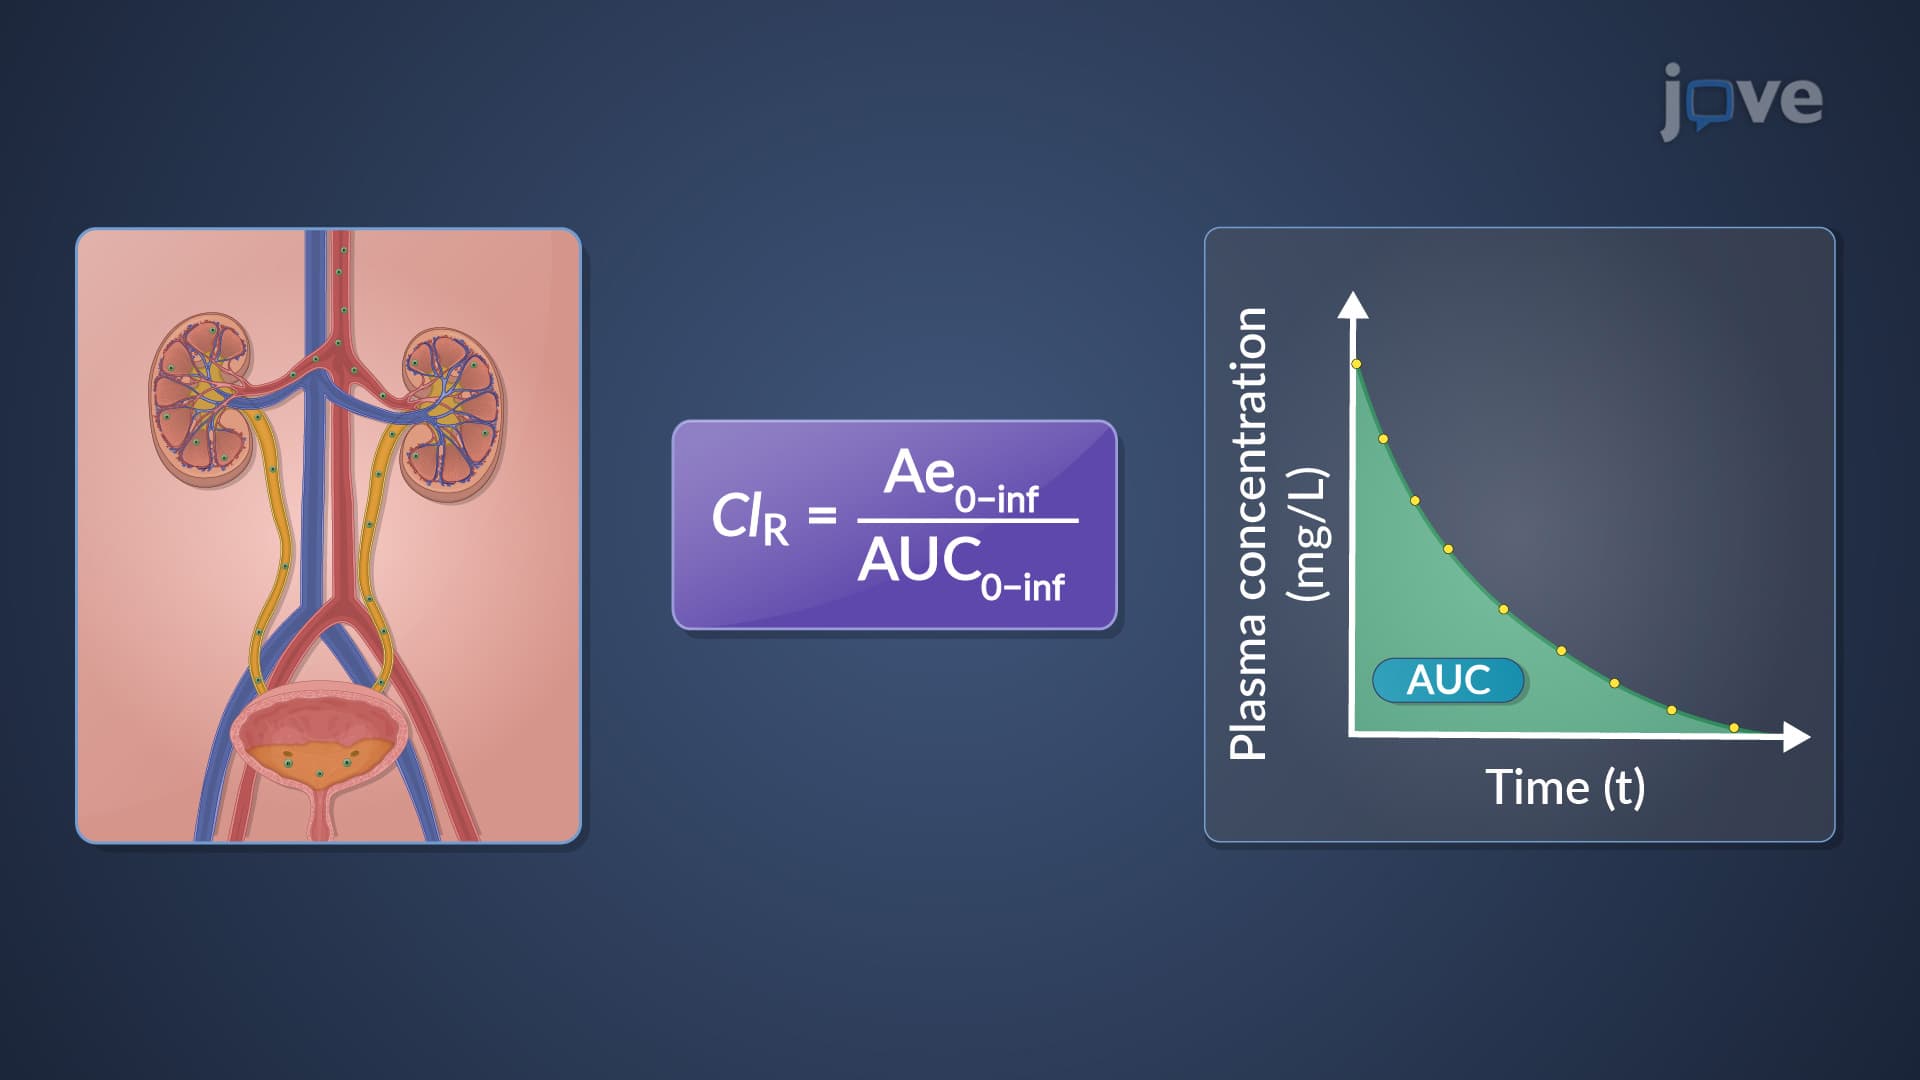
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...