Related Experiment Video
Updated: Aug 8, 2025

Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Two brothers with congenital bulbar urethral stricture: case report of a very rare condition
Seif Mokadem1, Ahmed Saadi1, Amine Hermi1
1Department of Urology, Charles Nicolle Hospital, University Tunis Manar, Faculty of Medicine Tunis, Tunis 1001, Tunisia.

Abstract:
Congenital urethral stricture is rare. It has been reported in only four sets of brothers. We report the fifth set of brothers. Cases of two brothers aged 23 and 18 years old diagnosed with low urinary tract symptoms are presented. We diagnosed an apparently congenital urethral stricture in both brothers. Internal urethrotomy was performed in both cases. Both are asymptomatic after 24 and 20 months of follow-up. Congenital urethral strictures are probably more frequent than we think. We suggest that a congenital origin should be considered if there is no history of infections or trauma.


Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:22
Ureters
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:16
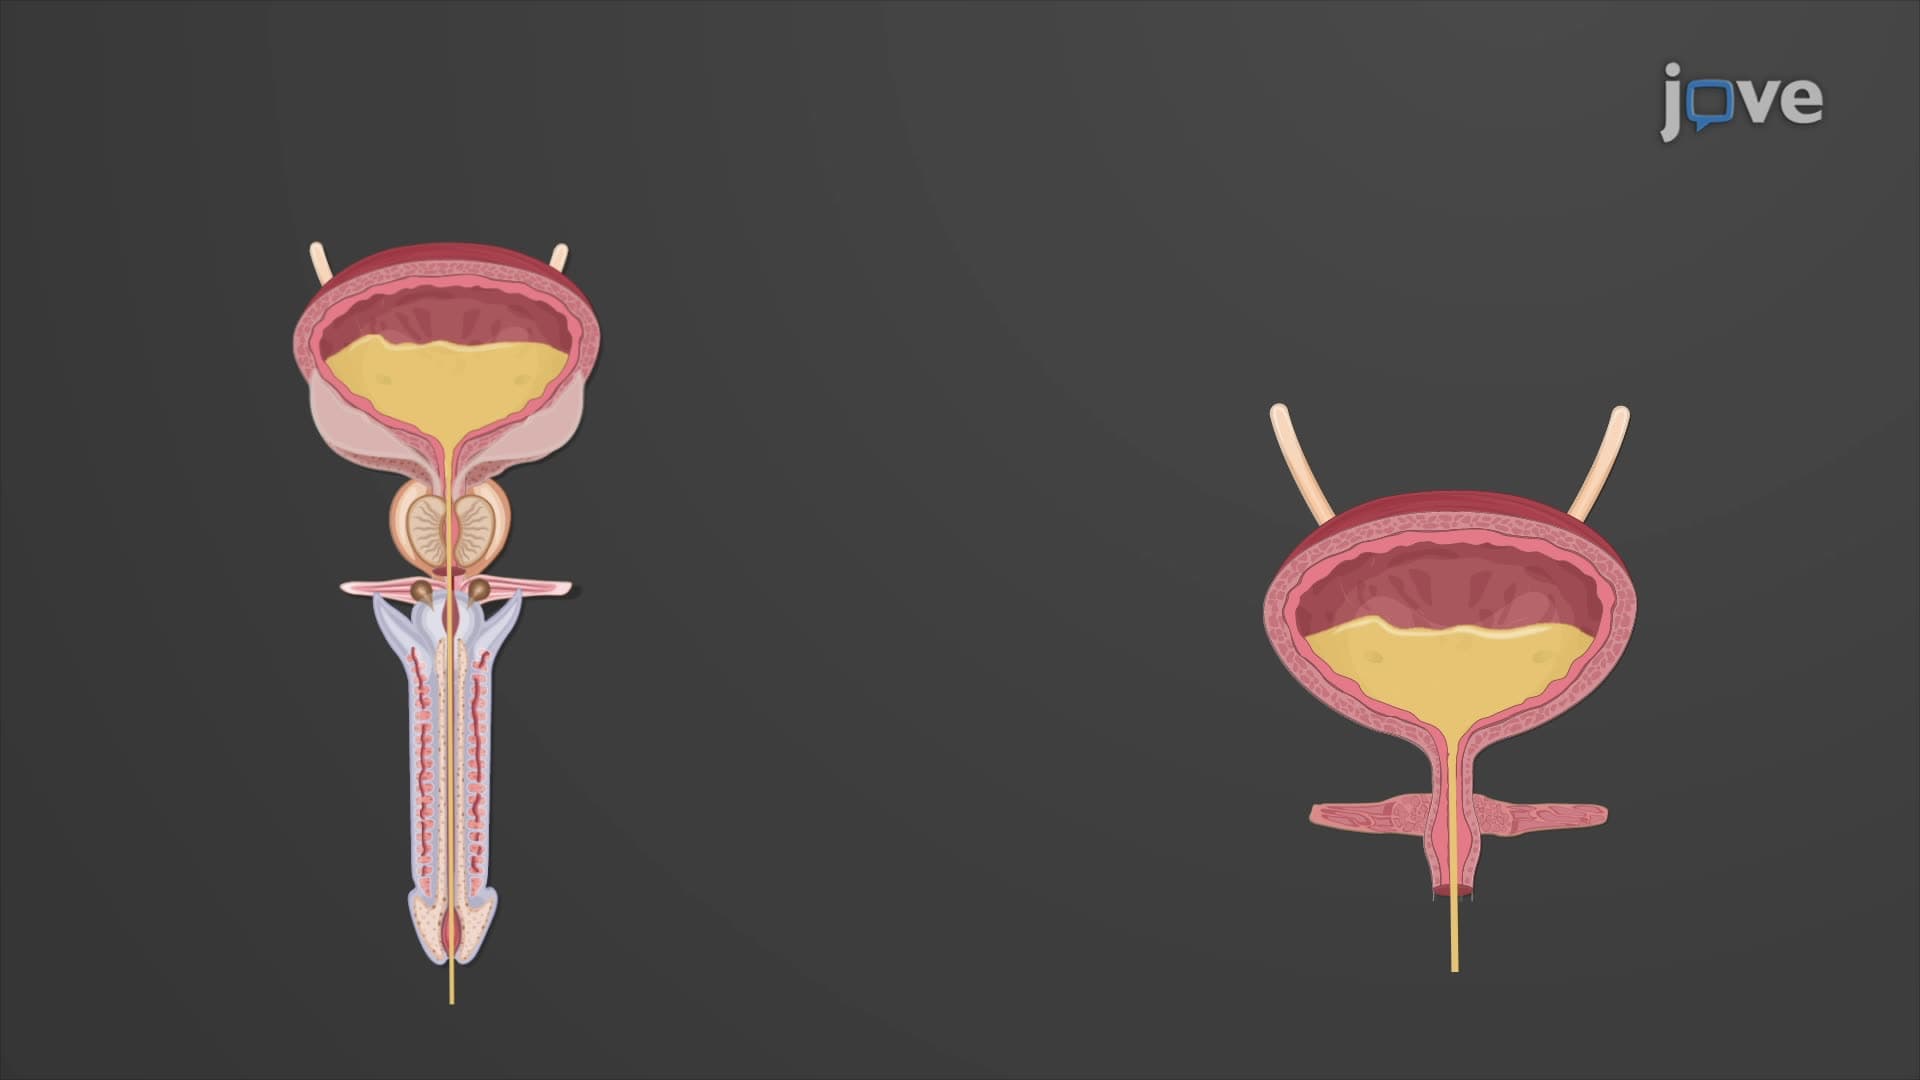
Urethra
The anatomy of the urethra differs between males and females. In females, the urethra is short, measuring about 3–4 cm in length, and opens anterior to the vaginal opening. In males, the urethra is longer and passes through the penis, serving dual purposes: expelling urine and ejaculating semen. The male...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations