Related Experiment Video
Updated: Aug 7, 2025

Insulin Injection and Hemolymph Extraction to Measure Insulin Sensitivity in Adult Drosophila melanogaster
Published on: June 30, 2011
Hybrid Closed-Loop with Faster Insulin Aspart Compared with Standard Insulin Aspart in Very Young Children with Type
Julia Ware1,2, Janet M Allen1, Charlotte K Boughton1,3
1Wellcome-MRC Institute of Metabolic Science-Metabolic Research Laboratories, University of Cambridge, Cambridge, United Kingdom.

Insights
Faster insulin aspart (Fiasp) with hybrid closed-loop (HCL) insulin delivery showed no significant glycemic outcome differences compared to standard insulin aspart in very young children with type 1 diabetes (T1D). This study evaluated Fiasp
Area of Science:
- Pediatric Endocrinology
- Diabetes Technology
- Metabolic Disorders
Background:
- Type 1 diabetes (T1D) management in very young children presents unique challenges.
- Hybrid closed-loop (HCL) insulin delivery systems offer advanced glycemic control options.
- Rapid-acting insulin analogs are crucial for effective mealtime glucose management.
Purpose of the Study:
- To evaluate the efficacy and safety of faster insulin aspart (Fiasp) within the CamAPS FX HCL system in children aged 2-6 years with T1D.
- To compare glycemic outcomes between Fiasp and standard insulin aspart (IAsp) when used with HCL technology.
- To assess the impact on time in target glucose range and incidence of hypoglycemia.
Main Methods:
- A double-blind, multicenter, randomized, crossover study design.
- 25 children with T1D (aged 2-6 years) participated, undergoing two 8-week treatment periods.
- Participants used the CamAPS FX HCL system with either Fiasp or IAsp, in random order.
Main Results:
- No significant difference in time in target glucose range (3.9-10.0 mmol/L) between Fiasp and IAsp (64% vs. 65%, P=0.71).
- No significant difference in time with glucose levels below 3.9 mmol/L was observed.
- No severe hypoglycemia or diabetic ketoacidosis events occurred post-randomization.
Conclusions:
- Faster insulin aspart (Fiasp) used with the CamAPS FX HCL system is not significantly different from standard insulin aspart (IAsp) in improving glycemic outcomes in very young children with T1D.
- The safety profile was comparable between the two insulin formulations within the HCL system.
- Further research may explore long-term effects and specific subgroups.
Abstract:
We evaluated the use of hybrid closed-loop (HCL) insulin delivery with faster insulin aspart (Fiasp) in very young children with type 1 diabetes (T1D). In a double-blind, multicenter, randomized, crossover study, children aged 2-6 years with T1D underwent two 8-week periods of HCL using CamAPS FX with Fiasp and standard insulin aspart (IAsp), in random order. Primary endpoint was between-treatment difference in time in target range 3.9-10.0 mmol/L. We randomized 25 participants: mean (±standard deviation) age 5.1 ± 1.3 years, baseline HbA1c 55 ± 9 mmol/mol. Time in range was not significantly different between interventions (64% ± 9% vs. 65% ± 9% for HCL with Fiasp vs. IAsp; mean difference -0.33% [95% confidence interval: -2.13 to 1.47; P = 0.71]). There was no significant difference in time with glucose <3.9 mmol/L. No post-randomization severe hypoglycemia or diabetic ketoacidosis events occurred. Use of Fiasp with CamAPS FX HCL demonstrated no significant difference in glycemic outcomes compared with IAsp in very young children with T1D. Clinical trials registration: NCT04759144.

Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:25
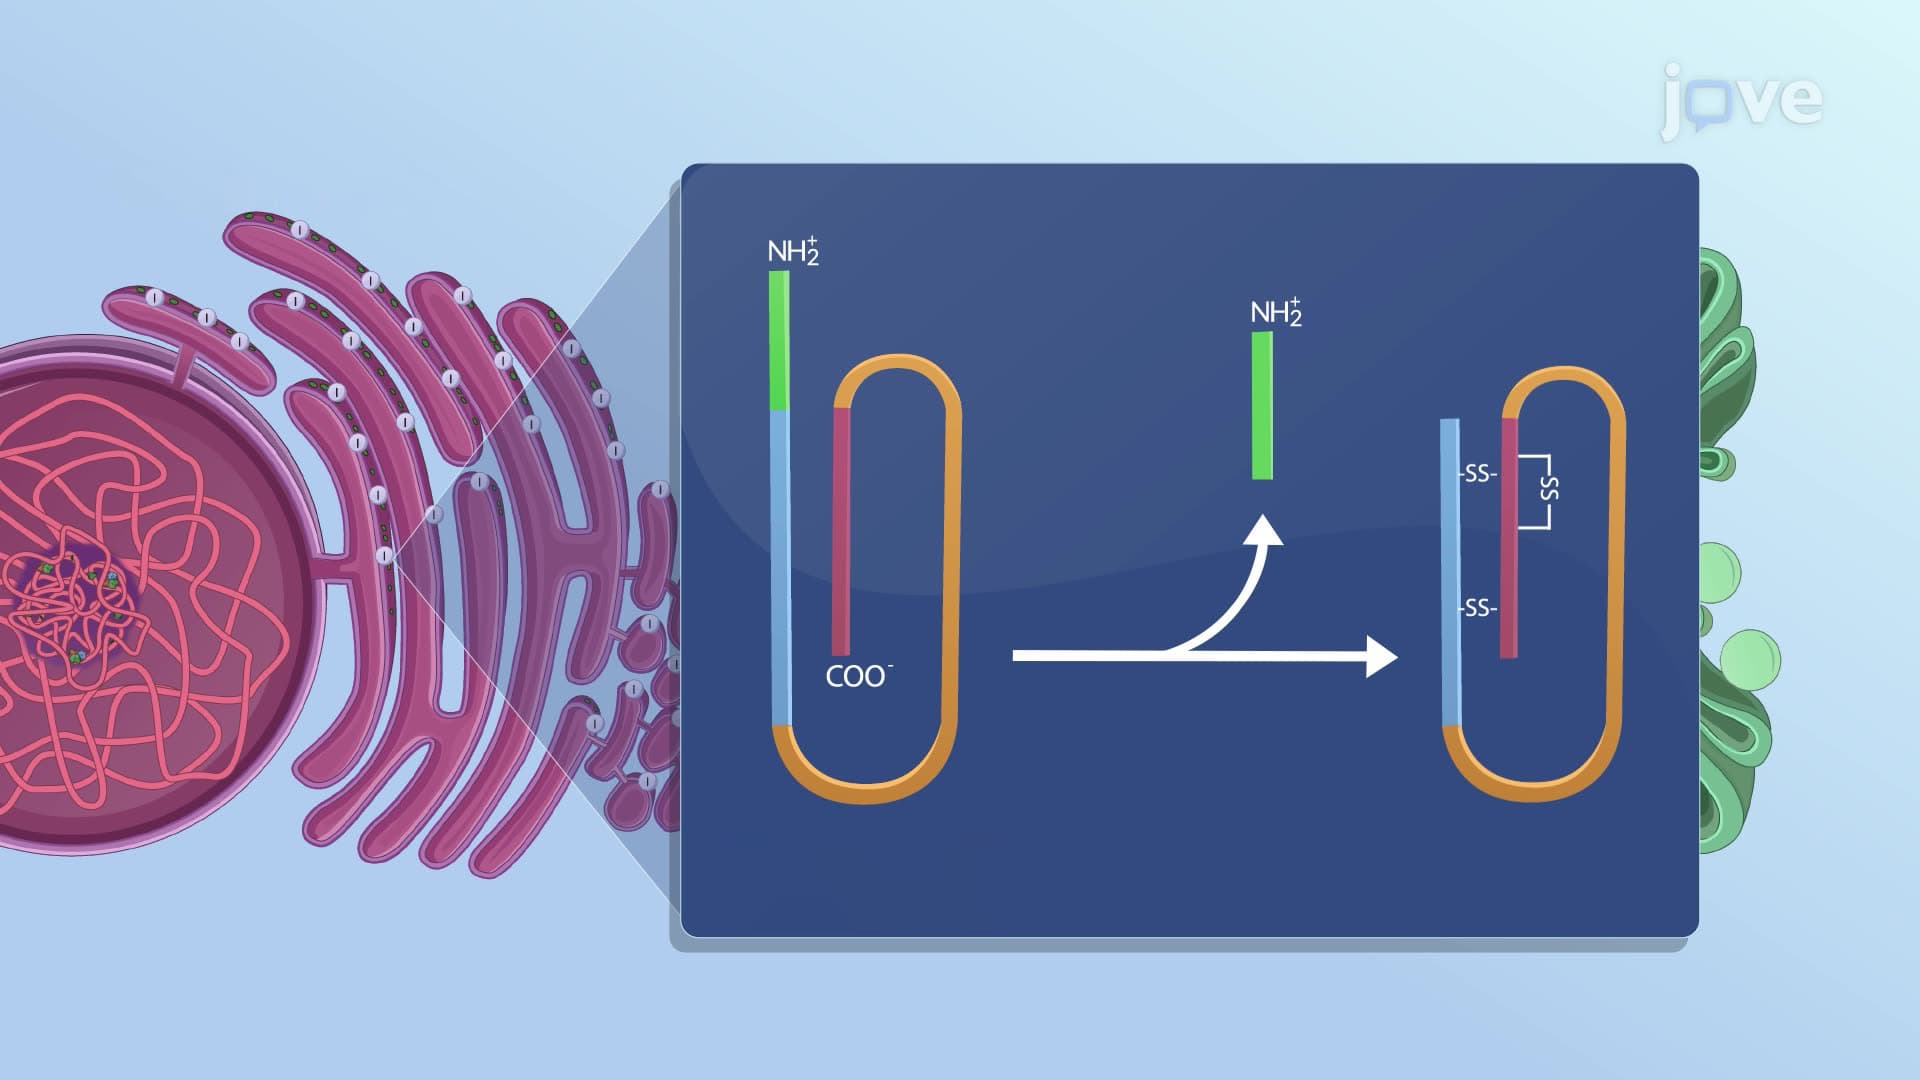
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:06
Oral Hypoglycemic Agents: Glinides
 01:05
Insulin Secretory Vesicles