Related Experiment Video
Updated: Aug 7, 2025
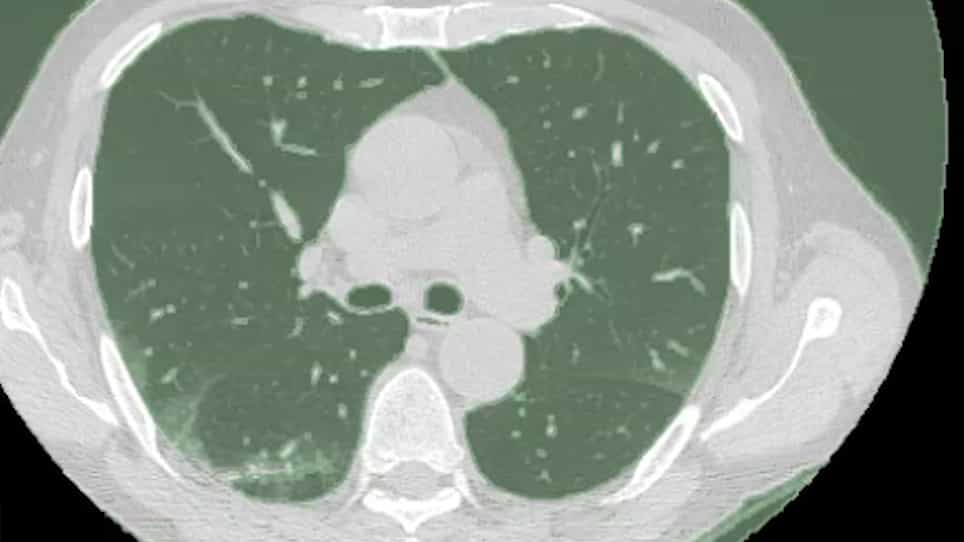

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
A prospective study of pulmonary outcomes and chest computed tomography in the first year after COVID-19
Tøri Vigeland Lerum1,2, Carin Meltzer3, Jezabel Riverio Rodriguez3
1Department of Pulmonary Medicine, Oslo University Hospital, Oslo, Norway.

Abstract:
COVID-19 primarily affects the respiratory system. We aimed to evaluate how pulmonary outcomes develop after COVID-19 by assessing participants from the first pandemic wave prospectively 3 and 12 months following hospital discharge. Pulmonary outcomes included self-reported dyspnoea assessed with the modified Medical Research Council dyspnoea scale, 6-min walk distance (6MWD), spirometry, diffusing capacity of the lung for carbon monoxide (D LCO), body plethysmography and chest computed tomography (CT). Chest CT was repeated at 12 months in participants with pathological findings at 3 months. The World Health Organization (WHO) ordinal scale for clinical improvement defined disease severity in the acute phase. Of 262 included COVID-19 patients, 245 (94%) and 222 (90%) participants attended the 3- and 12-month follow-up, respectively. Self-reported dyspnoea and 6MWD remained unchanged between the two time points, while D LCO and total lung capacity improved (0.28 mmol·min-1·kPa-1, 95% CI 0.12-0.44, and 0.13 L, 95% CI 0.02-0.24, respectively). The prevalence of fibrotic-like findings on chest CT at 3 and 12 months in those with follow-up chest CT was unaltered. Those with more severe disease had worse dyspnoea, D LCO and total lung capacity values than those with mild disease. There was an overall positive development of pulmonary outcomes from 3 to 12 months after hospital discharge. The discrepancy between the unaltered prevalence of self-reported dyspnoea and the improvement in pulmonary function underscores the complexity of dyspnoea as a prominent factor of long-COVID. The lack of increase in fibrotic-like findings from 3 to 12 months suggests that SARS-CoV-2 does not induce a progressive fibrotic process in the lungs.
More Related Videos
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids