Related Experiment Video
Updated: Aug 2, 2025


Author Spotlight: Investigating HR-Dependent Cardiac Function in Mouse Models Through a Novel Atrial-Pacing Approach
Published on: July 21, 2023
The Difference Between Cystatin C- and Creatinine-Based Estimated GFR in Heart Failure With Reduced Ejection
Alberto Pinsino1, Matthew R Carey2, Syed Husain3
1Department of Medicine, Division of Cardiology, Columbia University Irving Medical Center; Division of Critical Care Medicine, Montefiore Medical Center, Albert Einstein College of Medicine, Bronx, NY.

Insights
Discrepancies between cystatin C (cysC)- and serum creatinine (Scr)-estimated glomerular filtration rate (eGFR) in heart failure with reduced ejection fraction (HFrEF) patients are common. These differences are linked to worse clinical outcomes, reduced quality of life, and frailty.
Area of Science:
- Cardiology
- Nephrology
- Biomarkers
Background:
- Serum creatinine (Scr) is the traditional marker for estimated glomerular filtration rate (eGFR), but cystatin C (cysC) offers an alternative.
- Muscle mass and nutritional status can differentially affect eGFR calculations based on cysC (eGFRcysC) and Scr (eGFRScr).
- The clinical significance of discrepancies between eGFRcysC and eGFRScr in heart failure (HF) is not well understood.
Purpose of the Study:
- To investigate the clinical implications of the difference between eGFRcysC and eGFRScr in patients with HF and reduced ejection fraction (HFrEF).
- To assess the association of these eGFR discrepancies with clinical outcomes, health-related quality of life (HRQoL), and frailty.
Main Methods:
- A post-hoc analysis of 1,970 HFrEF patients from the PARADIGM-HF trial with available baseline cysC and Scr measurements.
- Intraindividual differences between eGFRcysC and eGFRScr (eGFRdiffcysC-Scr) were calculated.
- Clinical outcomes were analyzed using Fine-Gray and Cox proportional hazards models; HRQoL and frailty were assessed using logistic regression.
Main Results:
- A significant proportion of patients (13.0% >+10 mL/min/1.73m², 35.7% <-10 mL/min/1.73m²) exhibited discrepancies in eGFR.
- More negative eGFRdiffcysC-Scr values were associated with significantly worse outcomes, including cardiovascular mortality, all-cause mortality, and worsening kidney function.
- Decreased eGFRdiffcysC-Scr correlated with increased prevalence of poor HRQoL and frailty. Worsening HF showed a more pronounced decline in eGFRcysC than eGFRScr.
Conclusions:
- Discrepancies between eGFRcysC and eGFRScr are prevalent in HFrEF patients and predict adverse clinical outcomes.
- These eGFR differences are associated with poorer health-related quality of life and increased frailty.
- The decline in kidney function during worsening HF is more accurately captured by eGFRcysC than eGFRScr.
Rationale & Objective:
The clinical implications of the discrepancy between cystatin C (cysC)- and serum creatinine (Scr)-estimated glomerular filtration rate (eGFR) in patients with heart failure (HF) and reduced ejection fraction (HFrEF) are unknown.
Study Design:
Post-hoc analysis of randomized trial data.
Setting & Participants:
1,970 patients with HFrEF enrolled in PARADIGM-HF with available baseline cysC and Scr measurements.
Exposure:
Intraindividual differences between eGFR based on cysC (eGFRcysC) and Scr (eGFRScr; eGFRdiffcysC-Scr).
Outcomes:
Clinical outcomes included the PARADIGM-HF primary end point (composite of cardiovascular [CV] mortality or HF hospitalization), CV mortality, all-cause mortality, and worsening kidney function. We also examined poor health-related quality of life (HRQoL), frailty, and worsening HF (WHF), defined as HF hospitalization, emergency department visit, or outpatient intensification of therapy between baseline and 8-month follow-up.
Analytical Approach:
Fine-Gray subdistribution hazard models and Cox proportional hazards models were used to regress clinical outcomes on baseline eGFRdiffcysC-Scr. Logistic regression was used to investigate the association of baseline eGFRdiffcysC-Scr with poor HRQoL and frailty. Linear regression models were used to assess the association of WHF with eGFRcysC, eGFRScr, and eGFRdiffcysC-Scr at 8-month follow-up.
Results:
Baseline eGFRdiffcysC-Scr was higher than +10 and lower than-10mL/min/1.73m2 in 13.0% and 35.7% of patients, respectively. More negative values of eGFRdiffcysC-Scr were associated with worse outcomes ([sub]hazard ratio per standard deviation: PARADIGM-HF primary end point, 1.18; P=0.008; CV mortality, 1.34; P=0.001; all-cause mortality, 1.39; P<0.001; worsening kidney function, 1.31; P=0.05). For a 1-standard-deviation decrease in eGFRdiffcysC-Scr, the prevalences of poor HRQoL and frailty increased by 29% and 17%, respectively (P≤0.008). WHF was associated with a more pronounced decrease in eGFRcysC than in eGFRScr, resulting in a change in 8-month eGFRdiffcysC-Scr of-4.67mL/min/1.73m2 (P<0.001).
Limitations:
Lack of gold-standard assessment of kidney function.
Conclusions:
In patients with HFrEF, discrepancies between eGFRcysC and eGFRScr are common and are associated with clinical outcomes, HRQoL, and frailty. The decline in kidney function associated with WHF is more marked when assessed with eGFRcysC than with eGFRScr.
Plain-Language Summary:
Kidney function assessment traditionally relies on serum creatinine (Scr) to establish an estimated glomerular filtration rate (eGFR). However, this has been challenged with the introduction of an alternative marker, cystatin C (cysC). Muscle mass and nutritional status have differential effects on eGFR based on cysC (eGFRcysC) and Scr (eGFRScr). Among ambulatory patients with heart failure enrolled in PARADIGM-HF, we investigated the clinical significance of the difference between eGFRcysC and eGFRScr. More negative values (ie, eGFRScr>eGFRcysC) were associated with worse clinical outcomes (including mortality), poor quality of life, and frailty. In patients with progressive heart failure, which is characterized by muscle loss and poor nutritional status, the decline in kidney function was more pronounced when eGFR was estimated using cysC rather than Scr.


Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:02
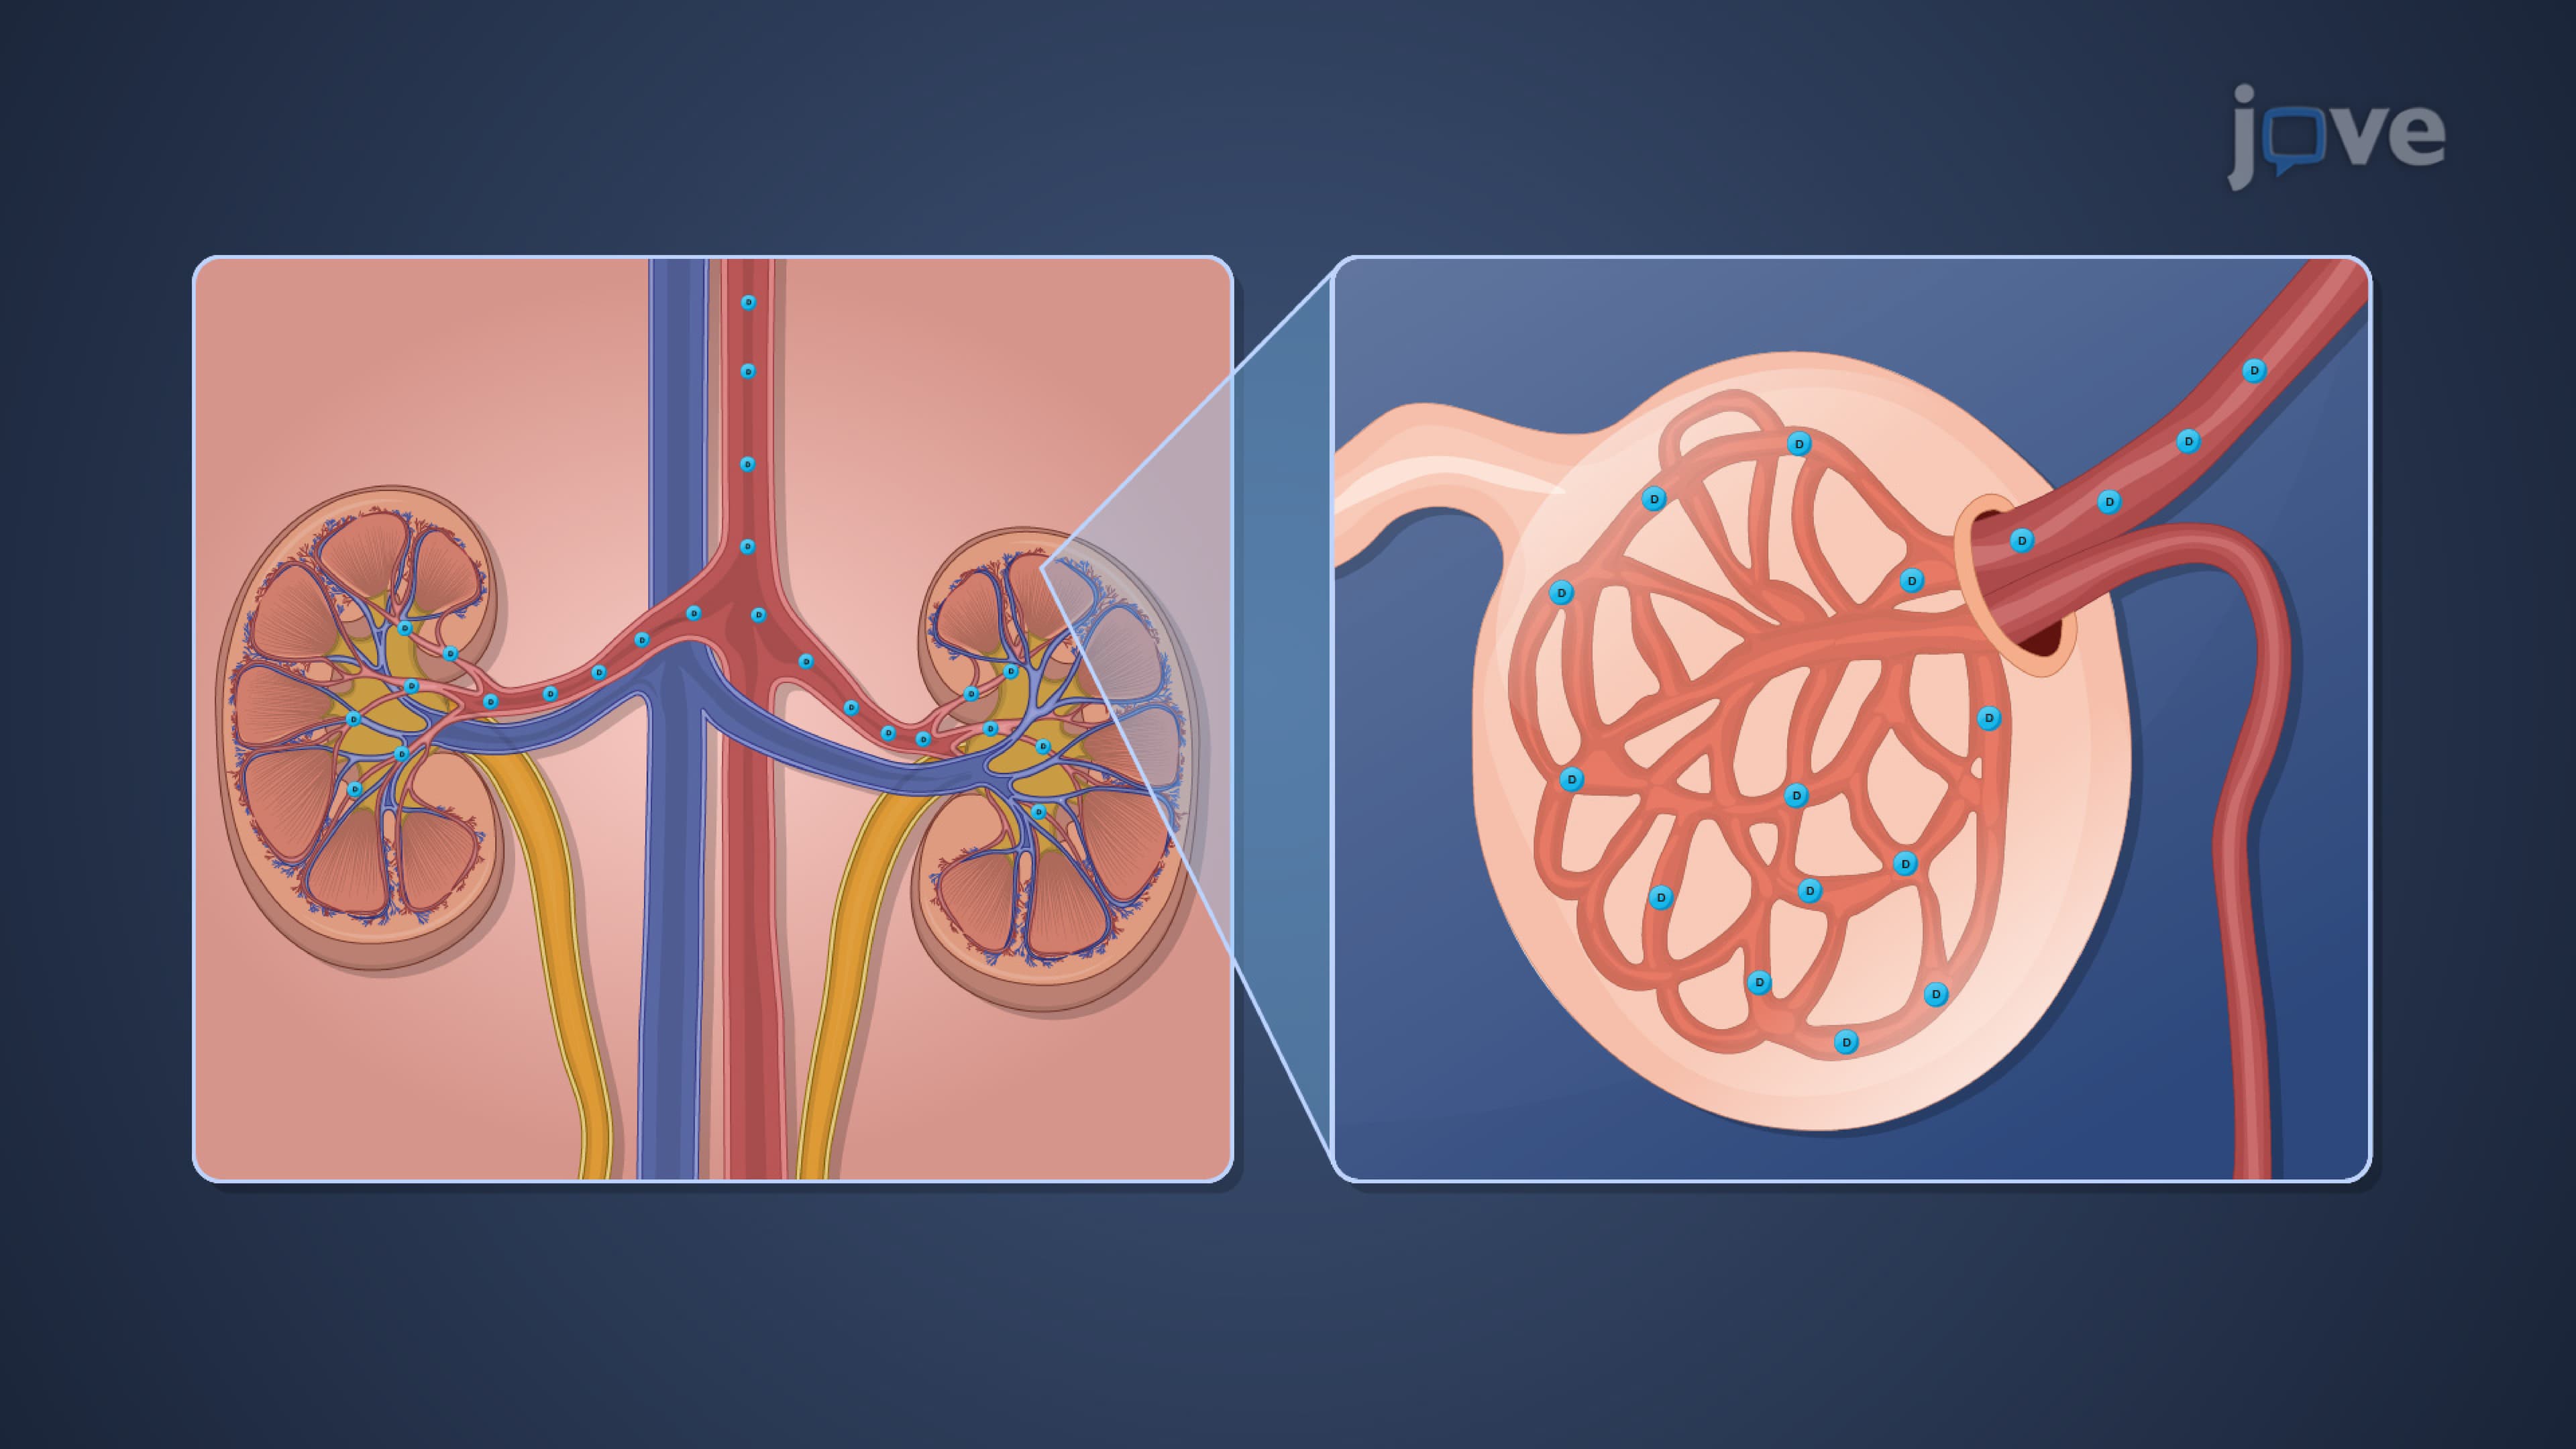
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:24
Serum Studies: Renal Function Tests
 01:17
Pathophysiology of Heart Failure