Related Experiment Video
Updated: Aug 1, 2025
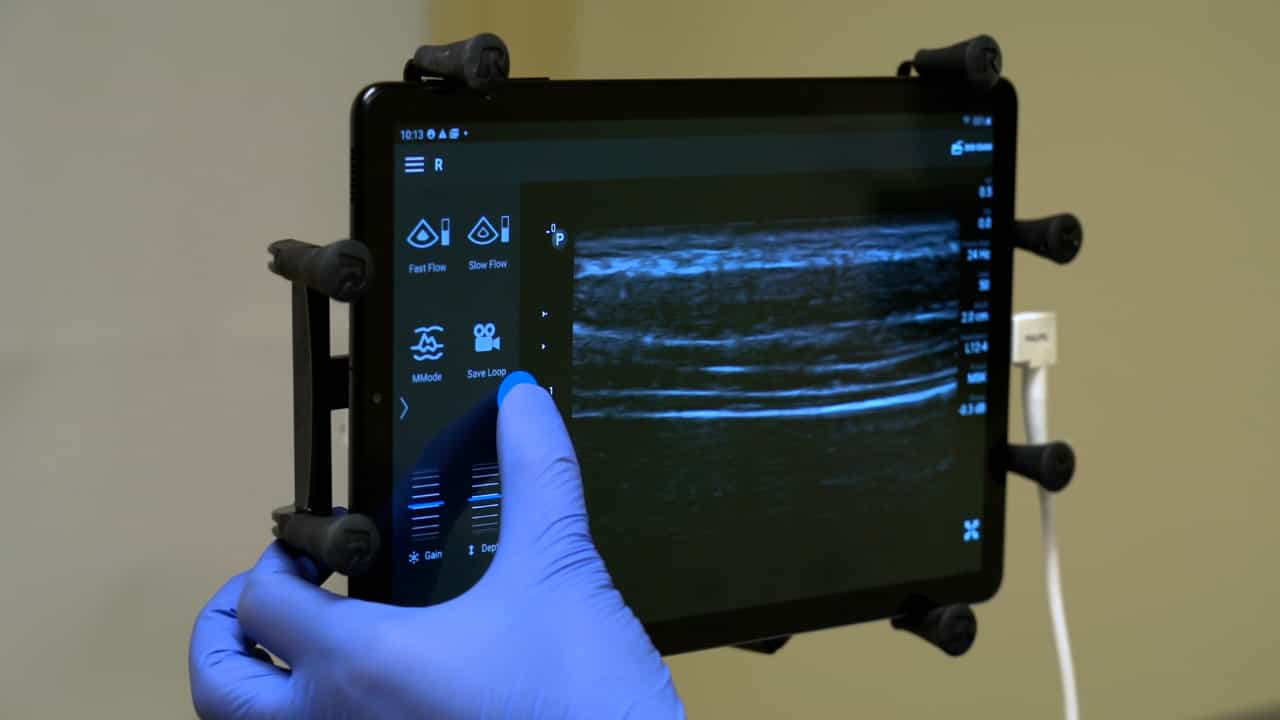

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
The Relationship Between Esophageal Pressure and Diaphragm Thickening Fraction in Spontaneously Breathing Sedated
Gregory R De Meyer1,2,3,4,5,6,7,8, Loïc Flamey1,3, Ine Adriaensens1
1Department of Anaesthesiology, Antwerp University Hospital, Edegem, Belgium.

Objectives:
Diaphragm ultrasound is a novel alternative to esophageal pressure measurements in the evaluation of diaphragm function and activity, but data about its reliability in a pediatric setting are lacking. We aimed to compare the esophageal pressure swing (∆P es , gold standard) with the diaphragmatic thickening fraction (DTF) as a measure of inspiratory effort in sedated children. Additionally, we studied the effect of positive end-expiratory pressure (PEEP) on the end-expiratory thickness of the diaphragm (DT ee ).
Design:
Prospective open-label non-randomized interventional physiological cohort study.
Setting:
Operating room in tertiary academic hospital.
Patients:
Children 28 days to 13 years old scheduled for elective surgery with general anesthesia, spontaneously breathing through a laryngeal mask airway, were eligible for inclusion. Exclusion criteria were disorders or previous surgery of the diaphragm, anticipated difficult airway or acute cardiopulmonary disease. All measurements were performed prior to surgery.
Interventions:
Patients were subjected to different levels of respiratory load, PEEP and anesthetic depth in a total of seven respiratory conditions.
Measurements And Main Results:
The esophageal pressure and diaphragm thickening fraction were simultaneously recorded for five breaths at each respiratory condition. The relation between ∆P es and DTF was studied in a mixed model. We analyzed 407 breaths in 13 patients. Both DTF ( p = 0.03) and ∆Pes ( p = 0.002) could detect respiratory activity, and ∆P es and DTF were associated across respiratory conditions ( p < 0.001; R2 = 31%). With increasing inspiratory load, ∆P es increased significantly, while DTF did not ( p = 0.08). Additionally, DT ee did not differ significantly between 10, 5, and 0 cm H 2 O PEEP ( p = 0.08).
Conclusions:
In spontaneously breathing sedated children and across different respiratory conditions, DTF could differentiate minimal or no inspiratory effort from substantial inspiratory effort and was associated with ∆P es . Increased efforts resulted in higher ∆P es but not larger DTF.
More Related Videos


Related Concept Videos
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:17
Pulmonary Cycle: Exhalation
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: