Related Experiment Video
Updated: Aug 1, 2025


The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Patient-, Clinician-, and Institution-level Variation in Inotrope Use for Cardiac Surgery: A Multicenter
Michael R Mathis1, Allison M Janda2, Sachin Kheterpal2
1Department of Anesthesiology, University of Michigan Medical School, Ann Arbor, Michigan; Department of Computational Bioinformatics, University of Michigan Medical School, Ann Arbor, Michigan.

Background:
Conflicting evidence exists regarding the risks and benefits of inotropic therapies during cardiac surgery, and the extent of variation in clinical practice remains understudied. Therefore, the authors sought to quantify patient-, anesthesiologist-, and hospital-related contributions to variation in inotrope use.
Methods:
In this observational study, nonemergent adult cardiac surgeries using cardiopulmonary bypass were reviewed across a multicenter cohort of academic and community hospitals from 2014 to 2019. Patients who were moribund, receiving mechanical circulatory support, or receiving preoperative or home inotropes were excluded. The primary outcome was an inotrope infusion (epinephrine, dobutamine, milrinone, dopamine) administered for greater than 60 consecutive min intraoperatively or ongoing upon transport from the operating room. Institution-, clinician-, and patient-level variance components were studied.
Results:
Among 51,085 cases across 611 attending anesthesiologists and 29 hospitals, 27,033 (52.9%) cases received at least one intraoperative inotrope, including 21,796 (42.7%) epinephrine, 6,360 (12.4%) milrinone, 2,000 (3.9%) dobutamine, and 602 (1.2%) dopamine (non-mutually exclusive). Variation in inotrope use was 22.6% attributable to the institution, 6.8% attributable to the primary attending anesthesiologist, and 70.6% attributable to the patient. The adjusted median odds ratio for the same patient receiving inotropes was 1.73 between 2 randomly selected clinicians and 3.55 between 2 randomly selected institutions. Factors most strongly associated with increased likelihood of inotrope use were institutional medical school affiliation (adjusted odds ratio, 6.2; 95% CI, 1.39 to 27.8), heart failure (adjusted odds ratio, 2.60; 95% CI, 2.46 to 2.76), pulmonary circulation disorder (adjusted odds ratio, 1.72; 95% CI, 1.58 to 1.87), loop diuretic home medication (adjusted odds ratio, 1.55; 95% CI, 1.42 to 1.69), Black race (adjusted odds ratio, 1.49; 95% CI, 1.32 to 1.68), and digoxin home medication (adjusted odds ratio, 1.48; 95% CI, 1.18 to 1.86).
Conclusions:
Variation in inotrope use during cardiac surgery is attributable to the institution and to the clinician, in addition to the patient. Variation across institutions and clinicians suggests a need for future quantitative and qualitative research to understand variation in inotrope use affecting outcomes and develop evidence-based, patient-centered inotrope therapies.


Related Concept Videos
 01:26
Heart Failure Drugs: Inotropic Agents
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:19
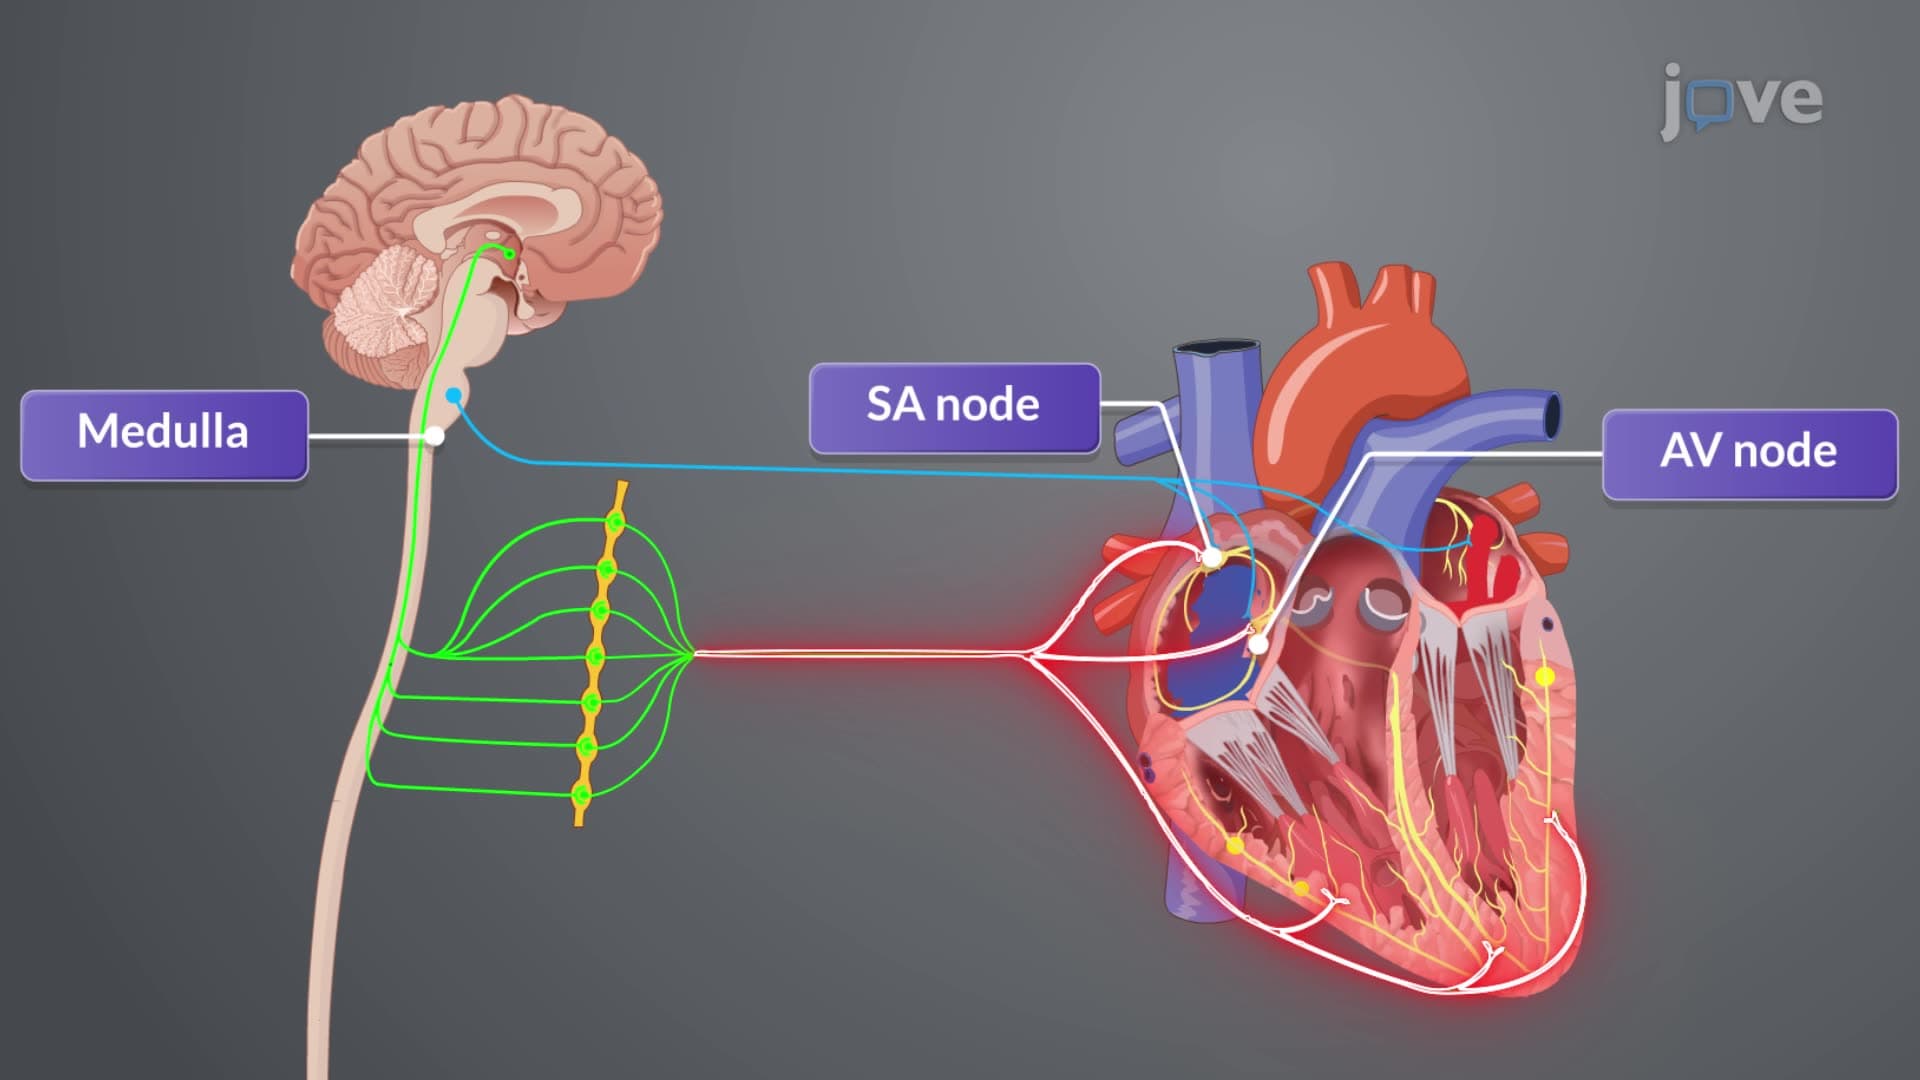
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:26
Cardiac Catheterization IV: Nursing Management