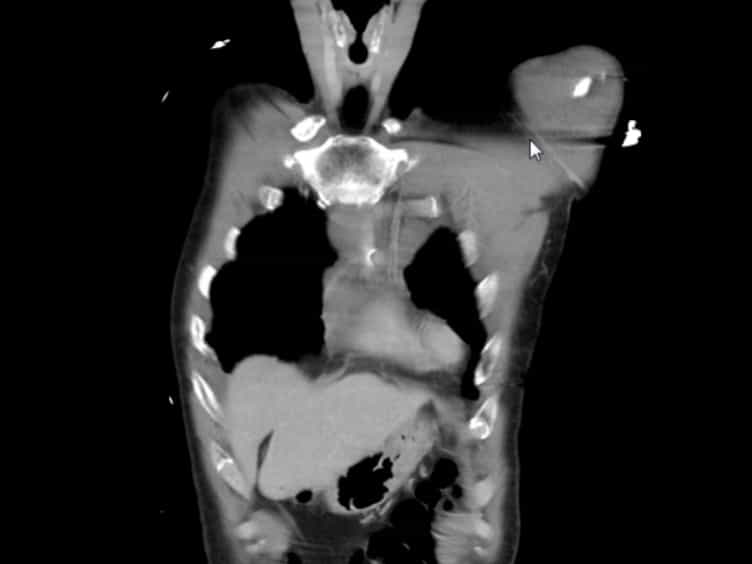
Surgical stabilization of rib fracture patients versus nonoperative controls treated by a multidisciplinary team in a
Frank Bauer1, Susan Haag1, Kaveh Najafi1
1Surgical and Critical Care, HonorHealth Scottsdale Osborn Medical Center, Scottsdale, AZ, 85251, USA.

Introduction:
Despite promising evidence, surgical stabilization of rib fractures (SSRF) is not ubiquitously offered in all trauma centers. Some centers struggle with patient selection while some struggle due to surgeon comfort with the technique. To address this issue, our trauma center developed a multidisciplinary SSRF approach between orthopedic and trauma surgery.
Methods:
This retrospective study compared 43 patients who underwent SSRF at a level 1 trauma center with 43 nonoperatively managed controls. Our study Indications were flail chest with >3 segments; non-flail with severe, bi-cortical displacement of >3 contiguous segments. Main outcome measures included mortality, ICU duration, hospital stay LOS, rates of ventilator-associated pneumonia (VAP) and ventilator days.
Results:
Results of SSRF included decreases in mortality (2% vs 16.3%; p = 0.03) and in ICU duration. Patients with SSRF had a significantly shorter duration in the ICU than the nonoperative group (8.72 vs 14 days; p = 0.013) but a similar hospital duration (LOS mean, 12.81 vs 15.2; p = 0.29). Less patients in the SSRF group developed VAP but the difference was not significant (2% vs 14%, ).
Discussion:
SSRF patient outcomes supported prior evidence. The tandem approach had benefits as surgeons were able to leverage skills and expertise, increase collaboration between services, and complete more difficult reconstructions. Our experience may serve as a model for trauma centers interested in starting a new program or enhancing current service offerings.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...