Related Experiment Video
Updated: Oct 19, 2026
Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Vertebral Body Tethering of Double Major Curvature via Mini-Open, Thoracoscopically-Assisted Thoracic and
Baron S Lonner1, Mark Kurapatti1, Sergei Dolgopolov2
1Department of Orthopedic Surgery, Mount Sinai Hospital, Icahn School of Medicine at Mount Sinai, New York, NY.

Background:
We describe key pearls and principles of a mini-open, thoracoscopically-assisted vertebral body tethering case for double-major scoliosis with 2 distinct anterior approaches: thoracic and thoracoabdominal.
Description:
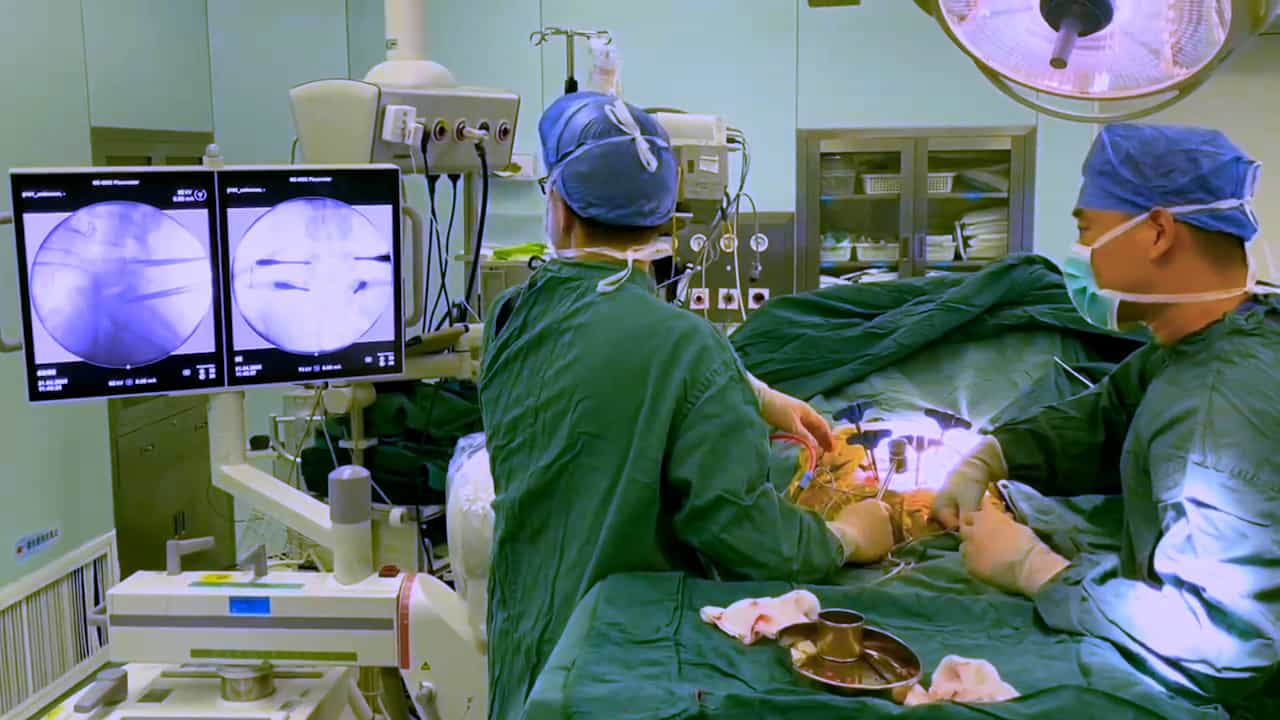
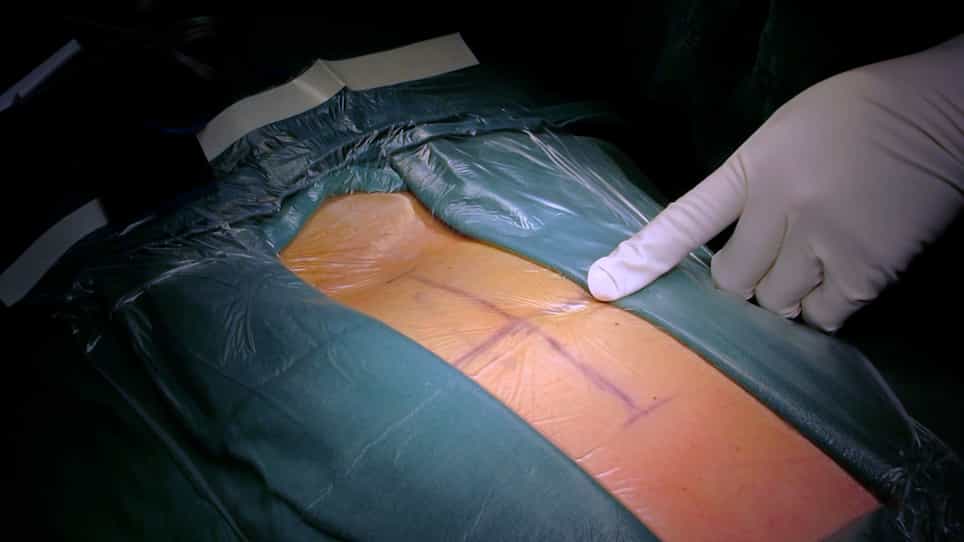
The thoracic curve is addressed through a mini-thoracotomy combined with thoracoscopic portals utilizing single-lung ventilation to provide clear visualization. Key steps include precise fluoroscopic marking of vertebral levels, muscle-sparing entry between the ribs, controlled pleural entry and mobilization, and careful management of segmental vessels. Vertebral body screws are placed under direct and fluoroscopic guidance with strict adherence to orthogonal trajectories and avoidance of disc violation. Tether placement proceeds segment-by-segment, maximizing correction at the apex while maintaining appropriate laxity distally to prevent overcorrection. Major tethering principles include maintaining colinear screw alignment to prevent tether kinking and utilizing bicortical fixation when anatomy permits. These principles ensure uniform force transmission and minimize stress concentrations within the tether construct, optimizing tether durability. The lumbar curve is accessed through a thoracoabdominal exposure that includes mobilization of the diaphragm with cuffed detachment and blunt retroperitoneal dissection to safely identify the iliopsoas muscle and sympathetic chain. Double-screw constructs are used at most accessible lumbar levels, with priority given to the apical region to enhance durability under higher mechanical loads. Screws are positioned posteriorly within the vertebral body to help maintain lumbar lordosis and are inserted with a controlled trajectory to achieve bicortical fixation while avoiding a posterior cortical breach and maintaining a safe distance from the spinal canal. Two tethers are applied (first posterior, then anterior) to distribute corrective forces and reduce peak tether strain, balancing correction with load-sharing. Adherence to these principles optimizes lordosis preservation, construct longevity, and safe modulation during growth.
Alternatives:
The primary alternative treatment is posterior spinal fusion (PSF), the current standard surgical treatment for adolescent idiopathic scoliosis1. PSF generally provides greater and more predictable curve correction, particularly for thoracic-major curves, but sacrifices motion across the fused spinal segments.
Rationale:
This surgical technique is appropriately applied in skeletally immature patients with flexible double-major adolescent idiopathic scoliosis who are undergoing vertebral body tethering through combined thoracic and thoracoabdominal anterior approaches1-7. A representative scenario is a patient with a right thoracic and a left lumbar curve demonstrating ≥50% correction of both curves on preoperative bending radiographs, indicating sufficient flexibility for growth modulation. Ideal candidates typically have Cobb angles between 40° and 65° and are skeletally immature (Risser 0 to 2, Sanders 3 to 4). The principles demonstrated are particularly relevant when treating double-curve deformities that require 2 distinct anterior exposures, wherein precise screw alignment, safe vessel and soft-tissue management, and differential tether tensioning are critical to predictable growth modulation. In the thoracic spine, this technique is useful when placing vertebral body screws through a mini-thoracotomy with thoracoscopic assistance, wherein colinear screw alignment and segmental tensioning are necessary to avoid tether kinking and maintain physiologic thoracic kyphosis. In the lumbar spine, thoracoabdominal exposure requires diaphragm mobilization and screws are posteriorly positioned; dual-screw constructs and staged posterior-then-anterior tethering help preserve lumbar lordosis and improve construct durability. These use cases emphasize scenarios in which precise fluoroscopic planning, harmonious screw trajectories, and controlled tether laxity are essential to avoid overcorrection, minimize mechanical stress on the tether, and achieve durable correction through guided spinal growth.
Expected Outcomes:
In appropriately selected adolescents with double-curve adolescent idiopathic scoliosis, bilateral vertebral body tethering can provide meaningful correction of both curves while preserving spinal motion1-3. Outcomes appear more favorable for thoracolumbar-major curves than thoracic-major curves, but patients should be counseled regarding risks of tether breakage, overcorrection, loss of correction, and potential revision or fusion. Long-term durability remains uncertain.
Important Tips:
Maintain optimal orthogonal fluoroscopic views throughout screw placement.Align screw tulips colinearly to avoid tether shear forces.Leave controlled laxity distally in patients with substantial remaining growth.Use bicortical fixation posteriorly in the lumbar spine for reliable fixation.Avoid placing screws too anteriorly or posteriorly, which increases the risk of a visceral or canal breach.Avoid overtensioning end segments, which increases the risk of overcorrection.Avoid grasping or damaging the tether with instruments.Avoid insufficient thoracotomy and/or portal placement, which can lead to poor exposure and suboptimal screw trajectory.
Acronyms And Abbreviations:
VBT = vertebral body tethering.