Related Experiment Video
Updated: Oct 19, 2026
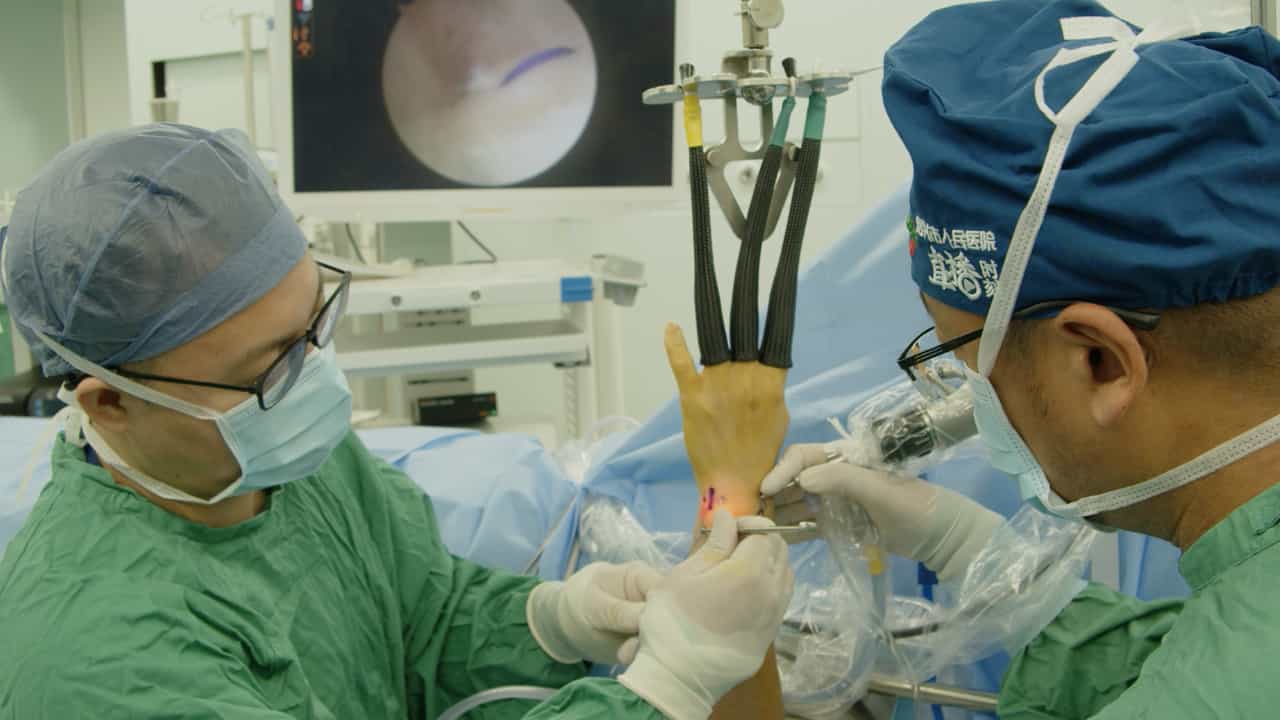
Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
All-Suture Fixation for Acute Turf Toe Injuries
Nicholas K Pappa1, Christopher Haritos1, Kyle S Ardavanis2
1Department of Orthopaedic Surgery, The Ohio State University Wexner Medical Center, Columbus, Ohio.

Background:
Turf toe is a hallux metatarsophalangeal joint (MTPJ) injury caused by hyperextension of the great toe with axial loading1,2. High-grade injuries may threaten return to sport and require surgery3,4. Here, we describe a capsular reconstruction of the great toe MTPJ with all-knotless suture anchors and suture tape augmentation for turf toe injuries, in isolation or in combination with a traumatic bunion, designed to reduce suture burden, minimize soft-tissue irritation, and facilitate recovery.
Description:
The procedure begins with the patient supine. A direct medial approach to the hallux MTPJ is performed. Both the medial base of the proximal phalanx and the medial eminence of the metatarsal head are drilled at isometric points, and augmentation with suture tape is then performed. Isometric drill holes are placed in the medial proximal phalanx base and metatarsal head for suture tape augmentation. A knotless suture anchor is placed approximately 3 mm proximal to the articular margin of the metatarsal head, repairing the medial capsule in a horizontal mattress fashion. An additional knotless anchor is placed at the plantar plate insertion, and the suture is passed through the tibial sesamoid sling and tensioned with the toe in 20° of plantar flexion. Suture tape is secured into the proximal phalanx with an interference screw, then passed through the deep capsule into the metatarsal head, followed by the placement of an additional interference screw into the metatarsal head. The anchor is inserted into the plantar-medial proximal phalanx at the flexor hallucis brevis insertion. The toe is flexed during tensioning, then adjusted per clinical examination and the sesamoid location beneath the metatarsal head. Knotless fixation permits incremental tensioning with intraoperative assessment of motion. Final tensioning is performed with the toe in neutral to correct deformity without overconstraint, preserving range of motion.
Alternatives:
Nonoperative alternatives include rest, ice, compression and elevation; anti-inflammatory drugs; activity modification; and brief immobilization5,6. Operative alternatives include primary capsuloligamentous complex repair with nonabsorbable sutures, plantar plate advancement with bone tunnels or suture anchors if primary repair is not feasible, and concomitant procedures such as sesamoidectomy and bunionectomy based on the injury pattern2,7,8.
Rationale:
This technique is intended for high-grade turf toe injuries with capsuloligamentous disruption, sesamoid complex insufficiency, and MTPJ instability. Nonoperative treatment may be appropriate in cases of low-grade injury; however, persistent pain, instability, or loss of push-off strength following nonoperative treatment would indicate a higher-grade injury. Compared with isolated repair or plantar plate advancement alone, this technique restores both static and dynamic stabilizers of the hallux MTPJ while addressing associated angular deformity. Suture tape augmentation resists recurrent hyperextension and valgus forces while allowing controlled physiologic motion. Knotless, low-profile suture anchors minimize bulk and hardware prominence in a region with limited soft-tissue coverage and bone stock. This construct offers a robust reconstruction option for athletes requiring predictable restoration of stability and reliable return to sport.
Expected Outcomes:
Operative treatment of high-grade turf toe injuries has been shown to result in reliable pain relief, restored stability, and high rates of return to sport8. Previous studies have suggested improved function and earlier return to play compared with prolonged nonoperative treatment in appropriate patients6,7. Knotless suture anchors reduce implant prominence and eliminate knot-related irritation, while the small insertional diameter of the suture anchors preserves bone stock in the metatarsal head and proximal phalanx. This construct provides immediate stability while allowing controlled motion, facilitating rehabilitation, and reducing postoperative stiffness. Athletes typically return to unrestricted activity within 6 to 9 months, aided by the suture tape augmentation allowing earlier movement through the range of motion. This augmentation reduces the need for long-term spica splinting and bracing and reduces the risk of recurrence.
Important Tips:
The small anchor diameter and use of suture tape allow easy access without hardware burden.○ Suture choice depends on surgeon preference regarding construct stiffness and on the tissue quality and risk of irritation. We believe that suture tape lays flatter and, if required, knots are smaller.Avoid suture twisting or kinking, which can prematurely lock anchors, compromising fixation.○ After the anchor is placed, we keep the suture tape secured out of the field as we prepare the capsule with absorbable suture. As we load the second anchor, we maintain tension on the tape to prevent twisting.Overtightening the MTPJ capsule may lead to altered biomechanics.
Acronyms And Abbreviations:
RICE = rest, ice, compression, elevationMRI = magnetic resonance imagingBID = twice daily.