Related Experiment Video
Updated: Jul 29, 2025
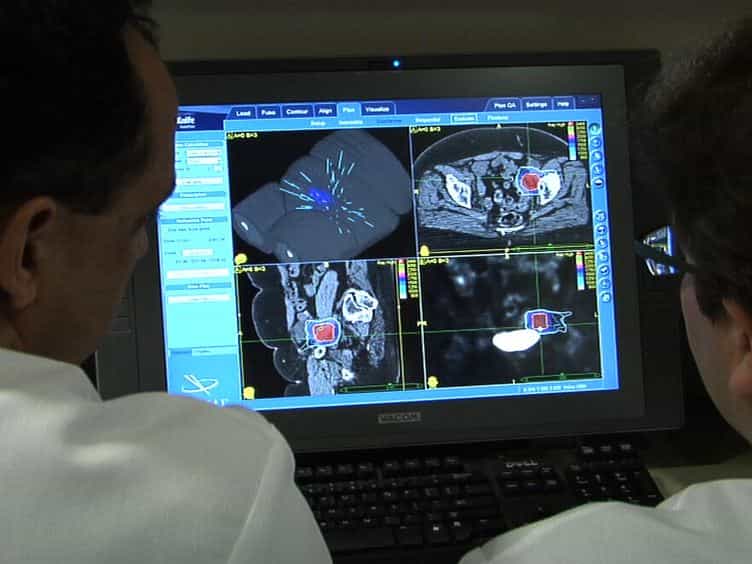
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Adaptive Positron Emission Tomography Radiation Therapy in Patients With Locally Advanced Vulvar Cancer: A
Rachel Shenker1, Carolyn Eckrich2, Rachel D'Anna3
1Departments of Radiation Oncology.

Purpose:
In this prospective trial, we aim to determine whether fluorodeoxyglucose positron emission tomography and computed tomography (PET/CT)-based adaptive radiation therapy (ART) improves dosimetry outcomes for patients treated with definitive radiation for locally advanced vulvar cancer.
Methods And Materials:
Patients were enrolled in 2 sequential institutional review board-approved prospective protocols for PET/CT ART from 2012 to 2020. Patients were planned with pretreatment PET/CT to 45 to 56 Gy in 1.8 Gy/fraction, followed by a boost to gross disease (nodal and/or primary) to a total of 64 to 66 Gy. Intratreatment PET/CT was obtained at 30 to 36 Gy, and all patients were replanned to the same dose goals with revised organ at risk (OAR), gross tumor volume, and planned target volume contours. Radiation therapy consisted of either intensity modulated radiation therapy or volumetric modulated arc therapy. Toxicity was graded by Common Terminology Criteria for Adverse Events, version 5.0. Local control, disease-free survival, overall survival, and time to toxicity were estimated using the Kaplan-Meier method. Dosimetry metrics for OARs were compared using the Wilcoxon signed rank test.
Results:
Twenty patients were eligible for analysis. Median follow-up among surviving patients was 5.5 years. Local control, disease-free survival, and overall survival at 2 years were 63%, 43%, and 68%, respectively. ART significantly reduced the following OAR doses: bladder, maximum dose (Dmax; median reduction [MR], 1.1 Gy; interquartile range [IQR], 0.48-2.3 Gy; P < .001) and D2cc (MR, 1.5 Gy; IQR, 0.51-2.1 Gy; P < .001); bowel, Dmax (MR, 1.0 Gy; IQR, 0.11-2.9 Gy; P < .001), D2cc (MR, 0.39 Gy; IQR, 0.023-1.7 Gy; P < .001), and D15cc (MR, 0.19 Gy; IQR, 0.026-0.47 Gy; P = .002); and rectal, mean dose (MR, 0.66 Gy; IQR, 0.17-1.7 Gy; P = .006) and D2cc (MR, 0.46 Gy; IQR, 0.17-0.80 Gy; P = .006). No patients experienced any grade ≥3 acute toxicities. There were no reported late grade ≥2 vaginal toxicities. Lymphedema at 2 years was 17% (95% confidence interval, 0%-34%).
Conclusions:
Doses to bladder, bowel, and rectum were significantly improved with ART, though the median magnitudes were modest. Which patients benefit most from adaptive treatment is a matter for future investigation.
More Related Videos
 08:34
Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
