Related Experiment Video
Updated: Jul 28, 2025


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
His-Purkinje system pacing versus biventricular pacing in clinical efficacy: a systematic review and meta-analysis
Ya Wang1, Fangchao Liu1, Mengyao Liu1
1Department of Epidemiology, Fuwai Hospital, State Key Laboratory of Cardiovascular Disease, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, No. 167 Beilishi Road, Beijing, 100037, China.

Background:
His-Purkinje system pacing (HPSP), including his-bundle pacing (HBP) and left bundle branch area pacing (LBBaP), imitates the natural conduction of the heart as an alternative to biventricular pacing (BVP) in cardiac resynchronization therapy (CRT). However, the feasibility and efficacy of HPSP were currently only evidenced by studies with a limited sample size, so this study aimed to provide a comprehensive assessment through a systematic review and meta-analysis.
Methods:
In order to compare the clinical outcomes associated with HPSP and BVP in patients for CRT, PubMed, EMBASE, Cochrane Library and Web of Science database were searched from inception to April 10, 2023. Clinical outcomes of interest including QRS duration (QRSd), left ventricular (LV) function and New York Heart Association (NYHA) functional classification, pacing threshold, echocardiographic and clinical response, hospitalization rate of HF and all-cause mortality were also extracted and summarized for meta-analysis.
Results:
A total of 13 studies (ten observational studies and three randomized studies) involving 1,121 patients were finally included. The patients were followed up for 6-27 months. Compared with BVP, CRT patients treated by HPSP presented shorter QRSd [mean difference (MD): -26.23 ms, 95% confidence interval (CI): -34.54 to -17.92, P < 0.001, I2 = 91%], greater LV functional improvement with increased left ventricular ejection fraction (LVEF) (MD: 6.01, 95% CI: 4.81 to 7.22, P < 0.001, I2 = 0%), decreased left ventricular end-diastolic dimension (LVEDD) (MD: -2.91, 95% CI: -4.86 to -0.95, P = 0.004, I2 = 35%), and more improved NYHA functional classification (MD: -0.45, 95% CI: -0.67 to -0.23, P < 0.001, I2 = 70%). In addition, HPSP was more likely to have higher echocardiographic [odds ratio (OR): 2.76, 95% CI: 1.74 to 4.39, P < 0.001, I2 = 0%], clinical (OR: 2.10, 95% CI: 1.16 to 3.80, P = 0.01, I2 = 0%) and super clinical (OR: 3.17, 95% CI: 2.09 to 4.79, P < 0.001, I2 = 0%) responses than BVP, and a lower hospitalization rate of HF (OR: 0.34, 95% CI: 0.22 to 0.51, P < 0.001, I2 = 0%), while presented no difference (OR: 0.68, 95% CI: 0.44 to 1.06, P = 0.09, I2 = 0%) in all-cause mortality compared with BVP. With threshold change taking into account, BVP was less stable than LBBaP (MD: -0.12 V, 95% CI: -0.22 to -0.03, P = 0.01, I2 = 57%), but had no difference with HBP (MD: 0.11 V, 95% CI: -0.09 to 0.31, P = 0.28, I2 = 0%).
Conclusion:
The present findings suggested that HPSP was associated with greater improvement of cardiac function in patients with indication for CRT and was a potential alternative to BVP to achieve physiological pacing through native his-purkinje system.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 07:49
Author Spotlight: Investigating HR-Dependent Cardiac Function in Mouse Models Through a Novel Atrial-Pacing Approach
Published on: July 21, 2023
Related Concept Videos
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:19
Conduction System of the Heart
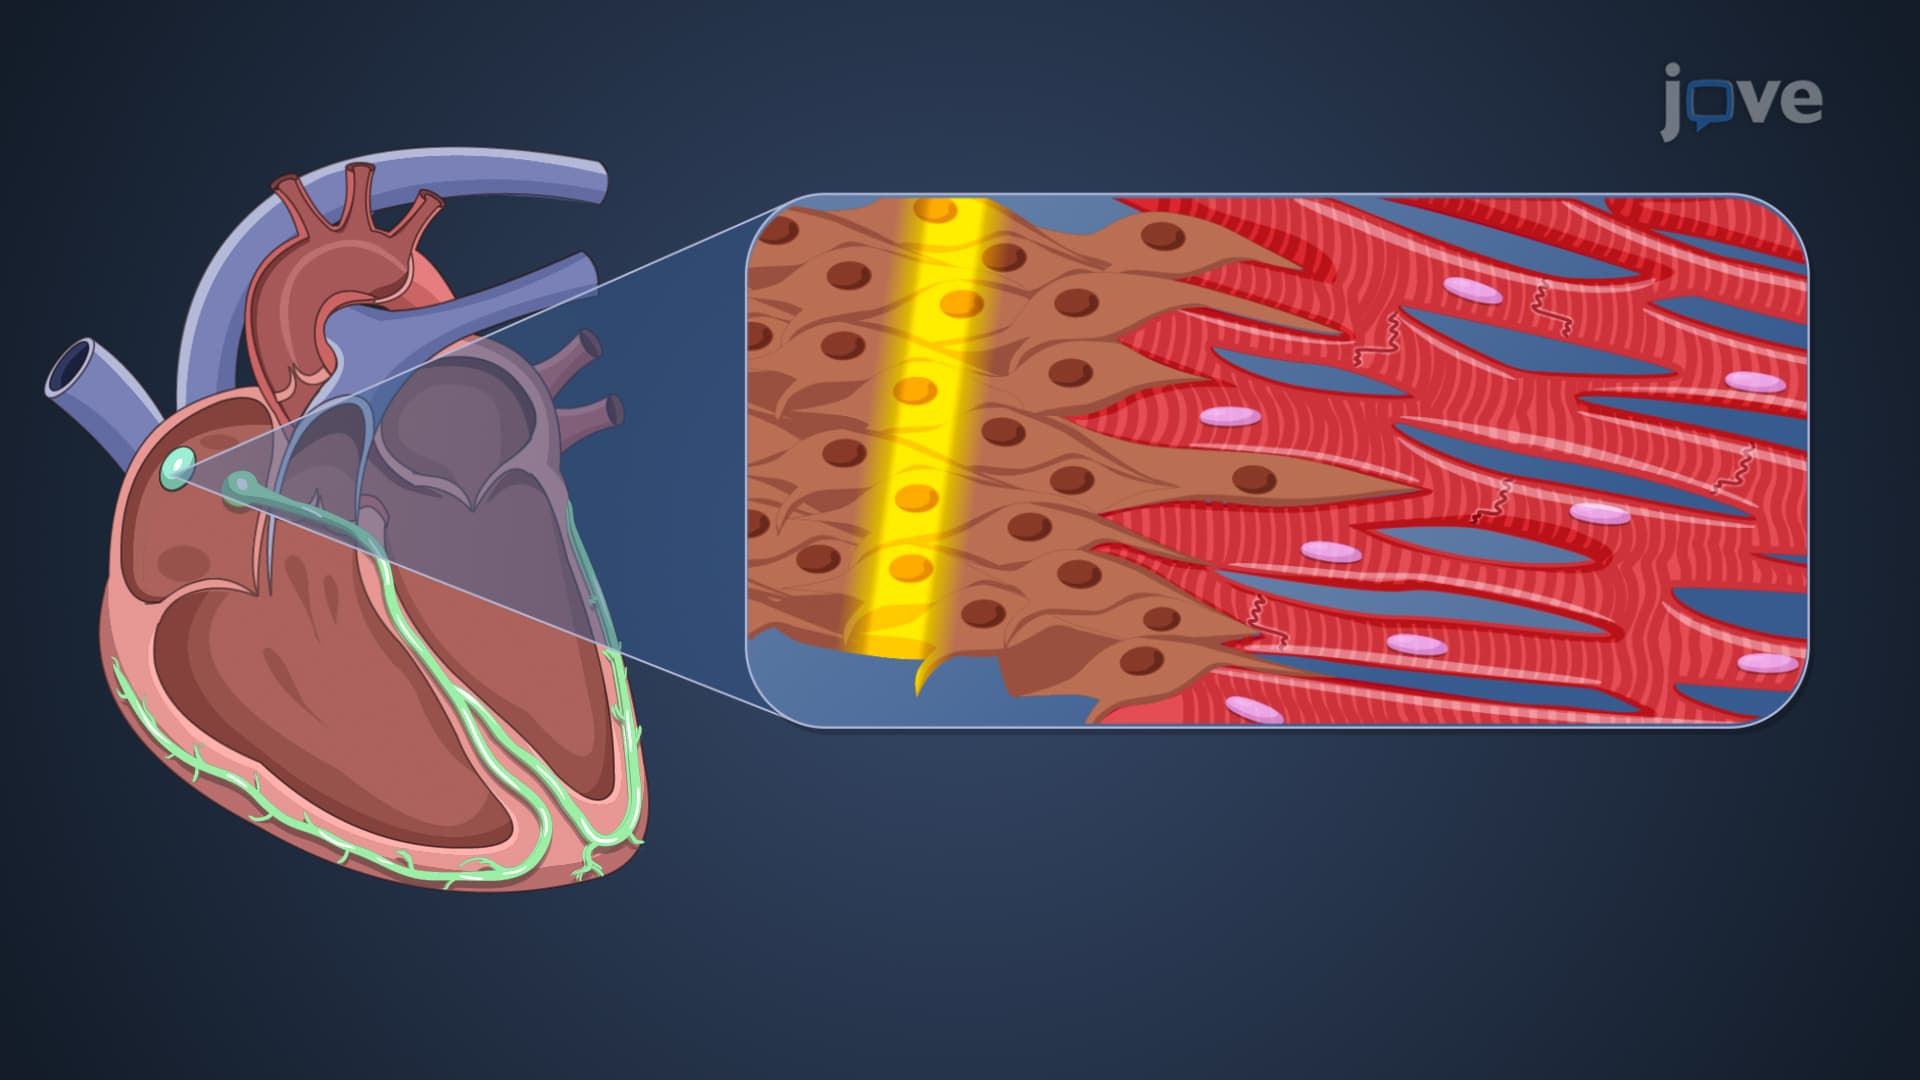
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:29
Heart Failure II: Pathophysiology