Related Experiment Video
Updated: Jul 24, 2026


PET and MRI Guided Irradiation of a Glioblastoma Rat Model Using a Micro-irradiator
Published on: December 28, 2017
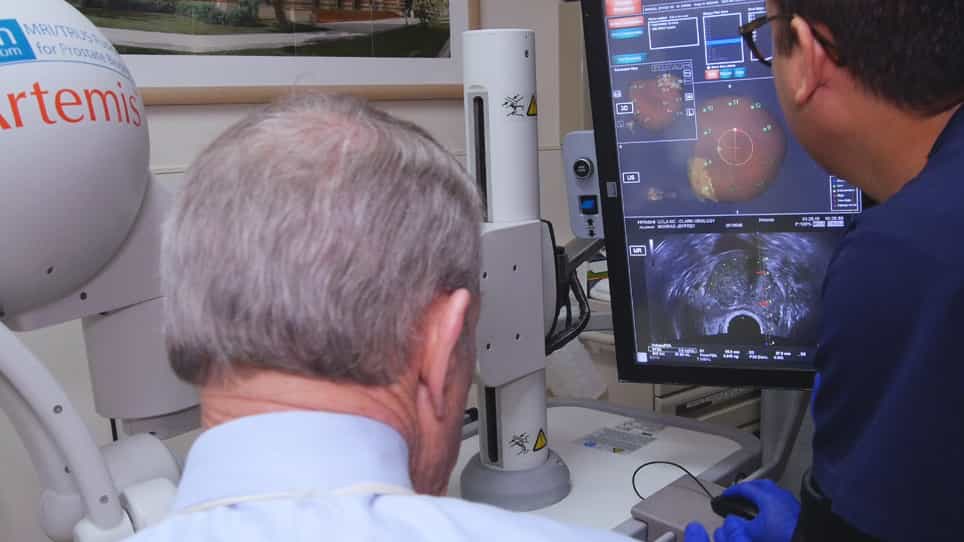
Institutional Learning Curve Associated with Implementation of a Magnetic Resonance/Transrectal Ultrasound Fusion
Matthew Truong1, Eric Weinberg2, Gary Hollenberg2
1Department of Urology, University of Rochester School of Medicine and Dentistry, Rochester, New York.

Introduction:
We assessed the institutional learning curve associated with adopting fusion biopsy using PI-RADS™ (Prostate Imaging-Reporting and Data System) Version 2 (v2) to detect clinically significant prostate cancer, defined as Gleason 7 or greater in men with prior negative biopsies, and identified patient and technical factors that predict success in detecting clinically significant prostate cancer.
Methods:
A total of 113 consecutive patients with at least 1 prior negative biopsy and multiparametric magnetic resonance imaging examination of the prostate with a PI-RADS 3 or greater index lesion underwent fusion biopsy at a single academic center previously naïve to fusion biopsy technology. Outcomes include detection rates for Gleason 6 cancer, clinically significant prostate cancer and any cancer. Multiple logistic regression with model selection was used to select covariates having significant effects on the outcome.
Results:
Prostate cancer was identified in 52% of patients with prior negative prostate biopsies. Among the patients diagnosed with prostate cancer 80% had clinically significant cancer. The clinically significant prostate cancer detection rates using fusion biopsy when a PI-RADS 3, 4 or 5 index lesion was present on multiparametric magnetic resonance imaging were 6%, 46% and 66%, respectively. PI-RADS v2 score had a predictive accuracy (AUC) of 0.79 for clinically significant prostate cancer detection. Institutional experience over time, magnetic resonance imaging estimated prostate volume and PI-RADS v2 score were independent predictors of clinically significant prostate cancer using fusion biopsy.
Conclusions:
Since fusion biopsy is a highly technique driven process, development of internal quality measures to assess the institutional learning curve and the quality of PI-RADS v2 scoring is critical with the adoption of this technology.