Related Experiment Video
Updated: Jul 26, 2025


In Vitro and In Vivo Assessment of T, B and Myeloid Cells Suppressive Activity and Humoral Responses from Transplant Recipients
Published on: August 12, 2017
Cellular Immunobiology and Molecular Mechanisms in Alloimmunity-Pathways of Immunosuppression
Eva Schrezenmeier1,2, Thomas Dörner3,4, Fabian Halleck1
1Department of Nephrology and Medical Intensive Care, Charité - Universitätsmedizin Berlin, corporate member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Berlin, Germany.

Current maintenance immunosuppression commonly comprises a synergistic combination of tacrolimus as calcineurin inhibitor (CNI), mycophenolic acid, and glucocorticoids. Therapy is often individualized by steroid withdrawal or addition of belatacept or inhibitors of the mechanistic target of rapamycin. This review provides a comprehensive overview of their mode of action, focusing on the cellular immune system. The main pharmacological action of CNIs is suppression of the interleukin-2 pathway that leads to inhibition of T cell activation. Mycophenolic acid inhibits the purine pathway and subsequently diminishes T and B cell proliferation but also exerts a variety of effects on almost all immune cells, including inhibition of plasma cell activity. Glucocorticoids exert complex regulation via genomic and nongenomic mechanisms, acting mainly by downregulating proinflammatory cytokine signatures and cell signaling. Belatacept is potent in inhibiting B/T cell interaction, preventing formation of antibodies; however, it lacks the potency of CNIs in preventing T cell-mediated rejections. Mechanistic target of rapamycin inhibitors have strong antiproliferative activity on all cell types interfering with multiple metabolic pathways, partly explaining poor tolerability, whereas their superior effector T cell function might explain their benefits in the case of viral infections. Over the past decades, clinical and experimental studies provided a good overview on the underlying mechanisms of immunosuppressants. However, more data are needed to delineate the interaction between innate and adaptive immunity to better achieve tolerance and control of rejection. A better and more comprehensive understanding of the mechanistic reasons for failure of immunosuppressants, including individual risk/benefit assessments, may permit improved patient stratification.
Current maintenance immunosuppression commonly comprises a synergistic combination of tacrolimus as calcineurin inhibitor (CNI), mycophenolic acid, and glucocorticoids. Therapy is often individualized by steroid withdrawal or addition of belatacept or inhibitors of the mechanistic target of rapamycin. This review provides a comprehensive overview of their mode of action, focusing on the cellular immune system. The main pharmacological action of CNIs is suppression of the interleukin-2 pathway that leads to inhibition of T cell activation. Mycophenolic acid inhibits the purine pathway and subsequently diminishes T and B cell proliferation but also exerts a variety of effects on almost all immune cells, including inhibition of plasma cell activity. Glucocorticoids exert complex regulation via genomic and nongenomic mechanisms, acting mainly by downregulating proinflammatory cytokine signatures and cell signaling. Belatacept is potent in inhibiting B/T cell interaction, preventing formation of antibodies; however, it lacks the potency of CNIs in preventing T cell-mediated rejections. Mechanistic target of rapamycin inhibitors have strong antiproliferative activity on all cell types interfering with multiple metabolic pathways, partly explaining poor tolerability, whereas their superior effector T cell function might explain their benefits in the case of viral infections. Over the past decades, clinical and experimental studies provided a good overview on the underlying mechanisms of immunosuppressants. However, more data are needed to delineate the interaction between innate and adaptive immunity to better achieve tolerance and control of rejection. A better and more comprehensive understanding of the mechanistic reasons for failure of immunosuppressants, including individual risk/benefit assessments, may permit improved patient stratification.
More Related Videos
 11:55
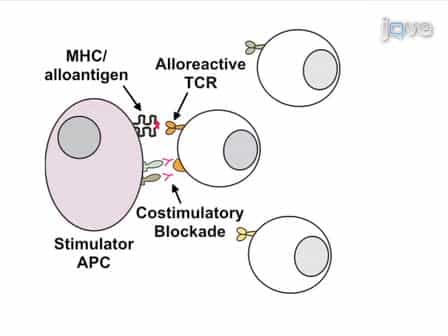
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
 05:10
Investigating the Immunological Mechanisms Underlying Organ Transplant Rejection
Published on: August 20, 2007
Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:27
Cytotoxic T Cells-mediated Immune Response
Immunological surveillance is the ability of immune cells to monitor and eliminate infected cells with intracellular pathogens, neoplastically transformed cells, and cells with non-self antigens. Cytotoxic T cells and NK...
 01:01
Regulation of Hematopoietic Stem Cells
 01:22
T Cell Activation and Clonal Selection
Naive T cells that have not yet encountered an antigen express two primary CD...
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:20
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...