Related Experiment Video
Updated: Jul 24, 2026


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Residency Experience With Physical Examination- and Ultrasound-Indicated Cerclage: A Single Center Retrospective
Burk Schaible1, Darcy Langhals1, Lesli Taylor2
1Department of Obstetrics and Gynecology, West Virginia University-Charleston Division, Charleston Area Medical Center, Charleston, WV.

Background: Cervical insufficiency, the dilation of the cervix in the absence of contractions or labor, can cause second-trimester pregnancy loss or preterm birth. Cervical cerclage is a common treatment for cervical insufficiency and has 3 indications for placement: history, physical examination, and ultrasound. The purpose of this study was to compare pregnancy and birth outcomes for physical examination- and ultrasound-indicated cerclage. Methods: We conducted a retrospective observational descriptive review of second-trimester obstetric patients with transcervical cerclage performed by residents at a single tertiary care medical center from January 1, 2006, to January 1, 2020. We present data on all patients and compare outcomes between the 2 study groups: patients who received physical examination-indicated cerclage vs those who received ultrasound-indicated cerclage. Results: Cervical cerclage was placed on 43 patients at a mean gestational age of 20.4 ± 2.4 weeks (range, 14 to 25 weeks) and with a mean cervical length of 1.53 ± 0.5 cm (range, 0.4 to 2.5 cm). With a latency period of 11.8 ± 5.7 weeks, mean gestational age at delivery was 32.1 ± 6.2 weeks. Fetal/neonatal survival rates were comparable: 80% (16/20) for the physical examination group compared to 82.6% (19/23) for the ultrasound group. No differences were found between groups for gestational age at delivery-31.5 ± 6.8 in the physical examination group vs 32.6 ± 5.8 in the ultrasound group (P=0.581)-or for preterm birth <37 weeks-65.0% (13/20) in the physical examination group vs 65.2% (15/23) in the ultrasound group (P=1.000). Rates of maternal morbidity and neonatal intensive care unit morbidity were similar between the groups. No cases of immediate operative complications or maternal deaths occurred. Conclusion: Pregnancy outcomes for physical examination- and ultrasound-indicated cerclage placed by residents at a tertiary academic medical center were similar. Fetal/neonatal survival and preterm birth rates were favorable for physical examination-indicated cerclage when compared to other published studies.
Background: Cervical insufficiency, the dilation of the cervix in the absence of contractions or labor, can cause second-trimester pregnancy loss or preterm birth. Cervical cerclage is a common treatment for cervical insufficiency and has 3 indications for placement: history, physical examination, and ultrasound. The purpose of this study was to compare pregnancy and birth outcomes for physical examination- and ultrasound-indicated cerclage. Methods: We conducted a retrospective observational descriptive review of second-trimester obstetric patients with transcervical cerclage performed by residents at a single tertiary care medical center from January 1, 2006, to January 1, 2020. We present data on all patients and compare outcomes between the 2 study groups: patients who received physical examination-indicated cerclage vs those who received ultrasound-indicated cerclage. Results: Cervical cerclage was placed on 43 patients at a mean gestational age of 20.4 ± 2.4 weeks (range, 14 to 25 weeks) and with a mean cervical length of 1.53 ± 0.5 cm (range, 0.4 to 2.5 cm). With a latency period of 11.8 ± 5.7 weeks, mean gestational age at delivery was 32.1 ± 6.2 weeks. Fetal/neonatal survival rates were comparable: 80% (16/20) for the physical examination group compared to 82.6% (19/23) for the ultrasound group. No differences were found between groups for gestational age at delivery-31.5 ± 6.8 in the physical examination group vs 32.6 ± 5.8 in the ultrasound group (P=0.581)-or for preterm birth <37 weeks-65.0% (13/20) in the physical examination group vs 65.2% (15/23) in the ultrasound group (P=1.000). Rates of maternal morbidity and neonatal intensive care unit morbidity were similar between the groups. No cases of immediate operative complications or maternal deaths occurred. Conclusion: Pregnancy outcomes for physical examination- and ultrasound-indicated cerclage placed by residents at a tertiary academic medical center were similar. Fetal/neonatal survival and preterm birth rates were favorable for physical examination-indicated cerclage when compared to other published studies.


Related Concept Videos
 01:17
Ultrasonography
During an ultrasonography procedure, a handheld device called a...
 01:25
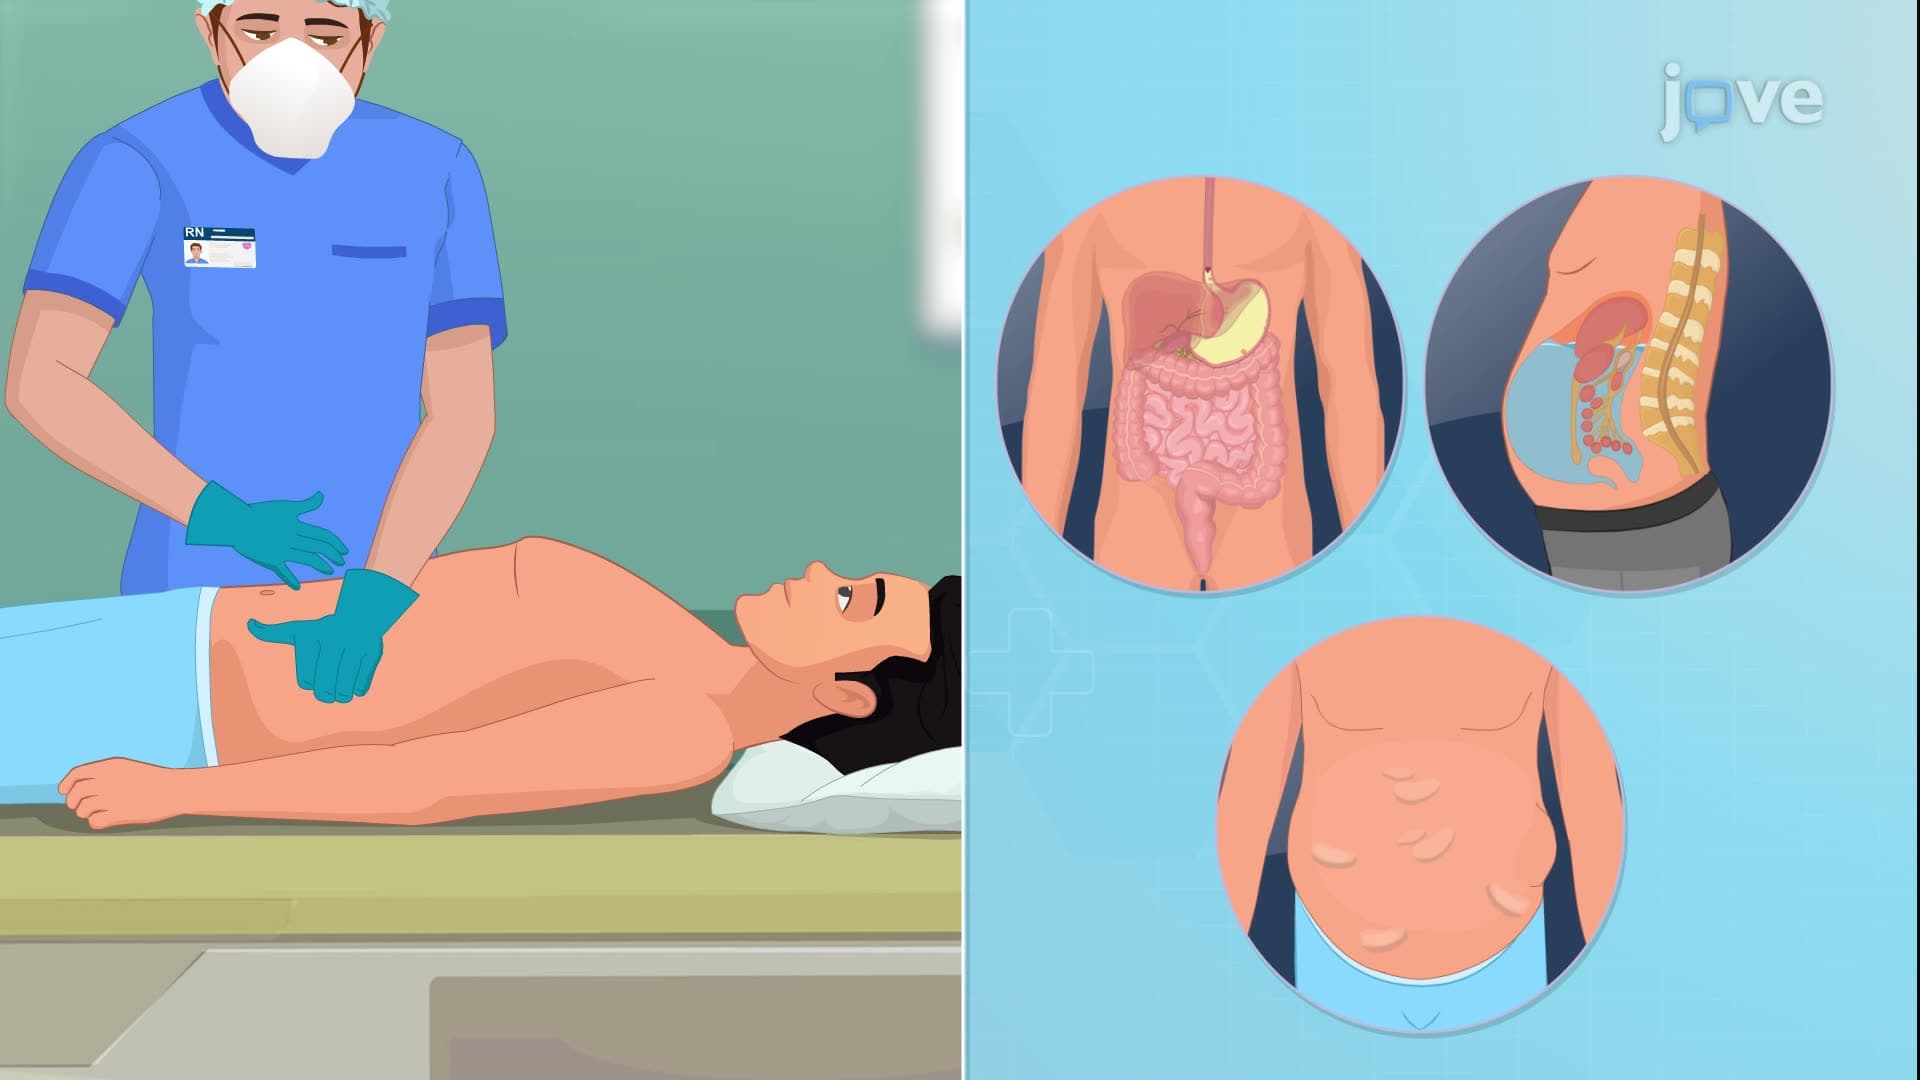
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:18
Assessment of the Abdomen II: Percussion
Percussion
Percussion is an essential...
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:20
Ultrasound I: Abdominal Ultrasonography
Abdominal ultrasonography, commonly known as abdominal ultrasound, is a vital, non-invasive medical imaging technique widely used in healthcare.
Procedure:
This diagnostic tool allows the clinician to visually inspect internal structures within the abdomen, including vital organs such as the liver, gallbladder, pancreas, kidneys, and spleen.
The abdominal ultrasound process begins with applying a special gel to the patient's skin over the abdomen. This gel enhances the...
 01:24
Imaging Studies II: Ultrasonography