Related Experiment Video
Updated: Jul 26, 2025
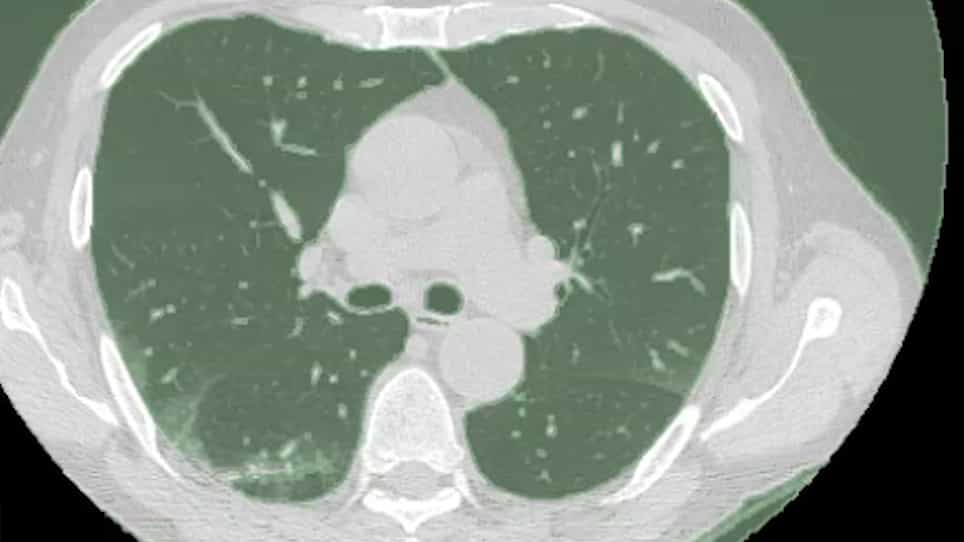

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Validation of the qSOFA and CRB-65 in SARS-CoV-2-infected community-acquired pneumonia
Tina Richter1, Falko Tesch2, Jochen Schmitt2
1Division of Pulmonology, Medical Department I, University Hospital Carl Gustav Carus, Technische Universität Dresden, Dresden, Germany.

Rationale:
Prognostic accuracy of the quick sequential organ failure assessment (qSOFA) and CRB-65 (confusion, respiratory rate, blood pressure and age (≥65 years)) risk scores have not been widely evaluated in patients with SARS-CoV-2-positive compared to SARS-CoV-2-negative community-acquired pneumonia (CAP). The aim of the present study was to validate the qSOFA(-65) and CRB-65 scores in a large cohort of SARS-CoV-2-positive and SARS-CoV-2-negative CAP patients.
Methods:
We included all cases with CAP hospitalised in 2020 from the German nationwide mandatory quality assurance programme and compared cases with SARS-CoV-2 infection to cases without. We excluded cases with unclear SARS-CoV-2 infection state, transferred to another hospital or on mechanical ventilation during admission. Predefined outcomes were hospital mortality and need for mechanical ventilation.
Results:
Among 68 594 SARS-CoV-2-positive patients, hospital mortality (22.7%) and mechanical ventilation (14.9%) were significantly higher when compared to 167 880 SARS-CoV-2-negative patients (15.7% and 9.2%, respectively). All CRB-65 and qSOFA criteria were associated with both outcomes, and age dominated mortality prediction in SARS-CoV-2 (risk ratio >9). Scores including the age criterion had higher area under the curve (AUCs) for mortality in SARS-CoV-2-positive patients (e.g. CRB-65 AUC 0.76) compared to SARS-CoV-2 negative patients (AUC 0.68), and negative predictive value was highest for qSOFA-65=0 (98.2%). Sensitivity for mechanical ventilation prediction was poor with all scores (AUCs 0.59-0.62), and negative predictive values were insufficient (qSOFA-65=0 missed 1490 out of 10 198 patients (∼15%) with mechanical ventilation). Results were similar when excluding frail and palliative patients.
Conclusions:
Hospital mortality and mechanical ventilation rates were higher in SARS-CoV-2-positive than SARS-CoV-2-negative CAP. For SARS-CoV-2-positive CAP, the CRB-65 and qSOFA-65 scores showed adequate prediction of mortality but not of mechanical ventilation.
More Related Videos


Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:20
Sputum Studies II: Culture and Sensitivity
Sputum culture and sensitivity is a medical procedure used to diagnose bacterial infections in the respiratory tract and select the most appropriate antibiotics for treatment. This process involves analyzing sputum samples of thick and opaque secretions produced in the lungs and airways. These samples are collected from patients and then sent to the laboratory for analysis.
The test can identify various pathogens responsible for respiratory infections, including Streptococcus,...
 01:29
Pneumonia II: Pathophysiology
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: