Related Experiment Video
Updated: Jul 25, 2025


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Challenges in Management of Concomitant Primary Aldosteronism and Pheochromocytoma
David Veríssimo1, Joana Vinhais1, Catarina Rodrigues Ivo1
1Endocrinology Service, Armed Forces Hospital, Lisboa, Portugal.

Abstract:
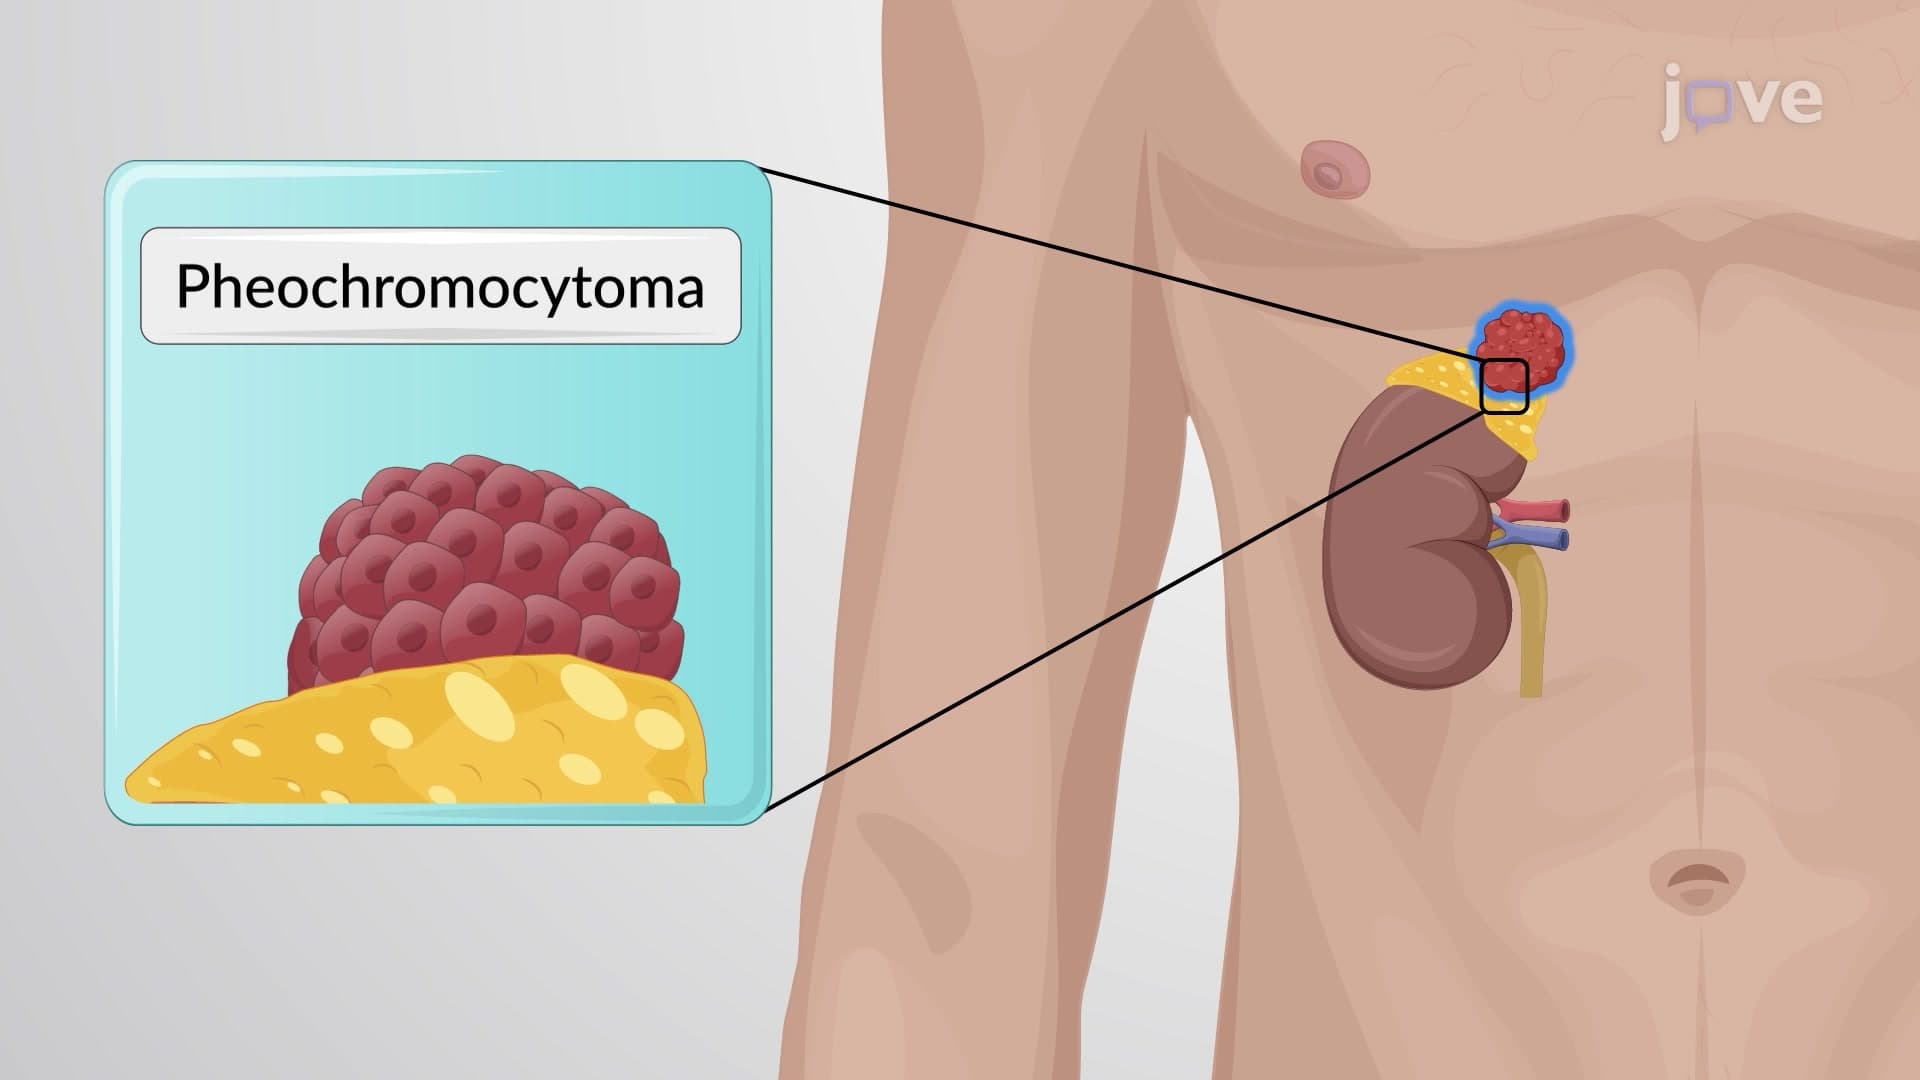
BACKGROUND Primary aldosteronism and pheochromocytoma are endocrine causes of secondary arterial hypertension. The association of primary aldosteronism and pheochromocytoma is rare and the involved mechanisms are poorly understood. Either there is a coexistence of both diseases or the pheochromocytoma stimulates the production of aldosterone. Since management approaches may differ significantly, it is important to properly diagnose the 2 conditions. We describe concomitant pheochromocytoma and primary aldosteronism in a patient with resistant hypertension, which demanded a challenging and individualized approach. CASE REPORT A 64-year-old man was sent for observation in our department for type 2 diabetes and resistant hypertension. Laboratory work-up suggested a primary aldosteronism and a pheochromocytoma. The abdominal CT (before and after intravenous contrast, with portal and delayed phase acquisitions) revealed an indeterminate right adrenal lesion and 3 nodules in the left adrenal gland: 1 indeterminate and 2 compatible with adenomas. A 18F-FDOPA PET-CT showed increased uptake in the right adrenal gland. The patient underwent a right adrenalectomy and a pheochromocytoma was confirmed. An improvement in glycemic control was observed after surgery but the patient remained hypertensive. A captopril test confirmed the persistence of primary aldosteronism, and he was started on eplerenone, achieving blood pressure control. CONCLUSIONS This case highlights the challenges in diagnosing and treating the simultaneous occurrence of pheochromocytoma and primary aldosteronism. Our main goal was surgical removal of the pheochromocytoma due to the risk of an adrenergic crisis.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:30
Heart Failure V: Medical Management
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers