Related Experiment Video
Updated: Jul 25, 2025
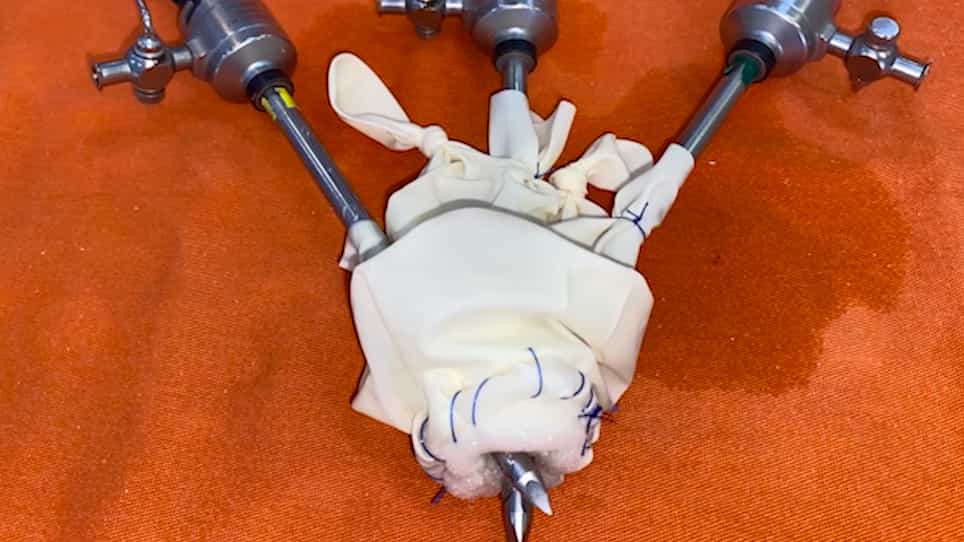
Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Improvement Effect of Upper Mediastinal Lymphadenectomy During Minimally Invasive Esophagectomy on the Prognosis in
Taro Oshikiri1, Hironobu Goto1, Takashi Kato1
1From the Divisions of Gastrointestinal Surgery (Oshikiri, Goto, Kato, Hasegawa, Kanaji, Yamashita, Kakeji), Department of Surgery, Graduate School of Medicine, Kobe University, Hyogo, Japan.

Background:
The effect of lymphadenectomy around the recurrent laryngeal nerve (RLN) in open esophagectomy has been demonstrated with the efficacy index (EI). However, it remains unclear whether this effect exists for minimally invasive esophagectomy (MIE) in the prone position. The purpose of this study was to clarify whether the upper mediastinal lymphadenectomy contributed to improved prognosis in patients with esophageal squamous cell carcinoma.
Study Design:
This study included 339 patients with esophageal squamous cell carcinoma treated with MIE in the prone position at Kobe University or Hyogo Cancer Center, Japan, from 2010 to 2015. EIs for each station, correlations between metastatic lymph nodes around the left RLN and RLN palsy, and survival of patients with and without upper mediastinal lymphadenectomy were investigated.
Results:
Among 297 patients treated with upper mediastinal lymphadenectomy, Clavien- Dindo grade ≥ II left RLN palsy occurred in 59 patients (20%). Overall, EIs for the right RLN (7.4) and left RLN (6.6) were higher than EIs for other stations. For patients with upper-third or middle-third tumors, the trend was stronger. Left RLN palsy was more likely in patients with metastatic lymph nodes around the left RLN than in those without (44% vs 15%, p < 0.0001). After propensity score-matching, 42 patients were included in each group with and without upper mediastinal lymphadenectomy. In survival analyses, the 5-year overall survival rates were 55% vs 35% and cause-specific survival rates were 61% vs 43% for the patients with and without upper mediastinal lymphadenectomy respectively. Significant differences were confirmed in survival curves (overall survival: p = 0.03; cause-specific survival: p = 0.04, respectively).
Conclusions:
Upper mediastinal lymphadenectomy contributes to improved prognosis with high EIs in MIE in the prone position.