Related Experiment Video
Updated: Jul 25, 2025


Author Spotlight: Advancing Human Ovarian Repair and Cancer Studies with Surface Epithelium Organoids
Published on: August 16, 2024
Ovarian Leydig Cell Tumor and Ovarian Hyperthecosis in a Postmenopausal Woman: A Case Report and Literature Review
Diana Bužinskienė1,2, Rūta Marčiukaitytė1, Evelina Šidlovska3
1Faculty of Medicine, Vilnius University, LT-03101 Vilnius, Lithuania.

Abstract:
Ovarian Leydig cell tumor is a rare type of ovarian steroid cell neoplasms, presenting in only 0.1% of all ovarian tumor cases, and is generally androgen-secreting and unilateral. Although they are often malignant non-spreading tumors, which have excellent prognosis, benign ovarian Leydig cell tumors with low-risk malignancy can be also detected. Ovarian hyperthecosis is a rare non-neoplastic disorder, in most cases bilateral. Ovarian tumors and ovarian hyperthecosis are one of the main causes of hyperandrogenism in postmenopausal women, a condition strongly associated with both hormonal and metabolic changes. Here, we report a 65-year-old patient with complaints of excessive body hairiness and alopecia. The laboratory investigation showed increased levels of serum testosterone and dehydroepiandrosterone sulfate (DHEA-S). Imaging, including transvaginal ultrasound and pelvic MRI revealed the presence of two masses in the ovaries. The patient underwent a laparoscopic bilateral salpingo-oophorectomy due to the ovarian tumors unknown etiology, and histopathological examination revealed a unilateral benign left ovarian Leydig cell tumor with bilateral ovarian stromal hyperplasia and ovarian hyperthecosis. Making differential diagnosis between ovarian tumors and ovarian hyperthecosis is difficult. Bilateral salpingo-oophorectomy is the treatment of choice in postmenopausal women with benign Leydig cell ovarian tumor, as well as ovarian hyperthecosis, as it offers both a cure and diagnostic confirmation.


Related Concept Videos
 02:07
Oogenesis
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:27
Ovarian Cycle
 01:26
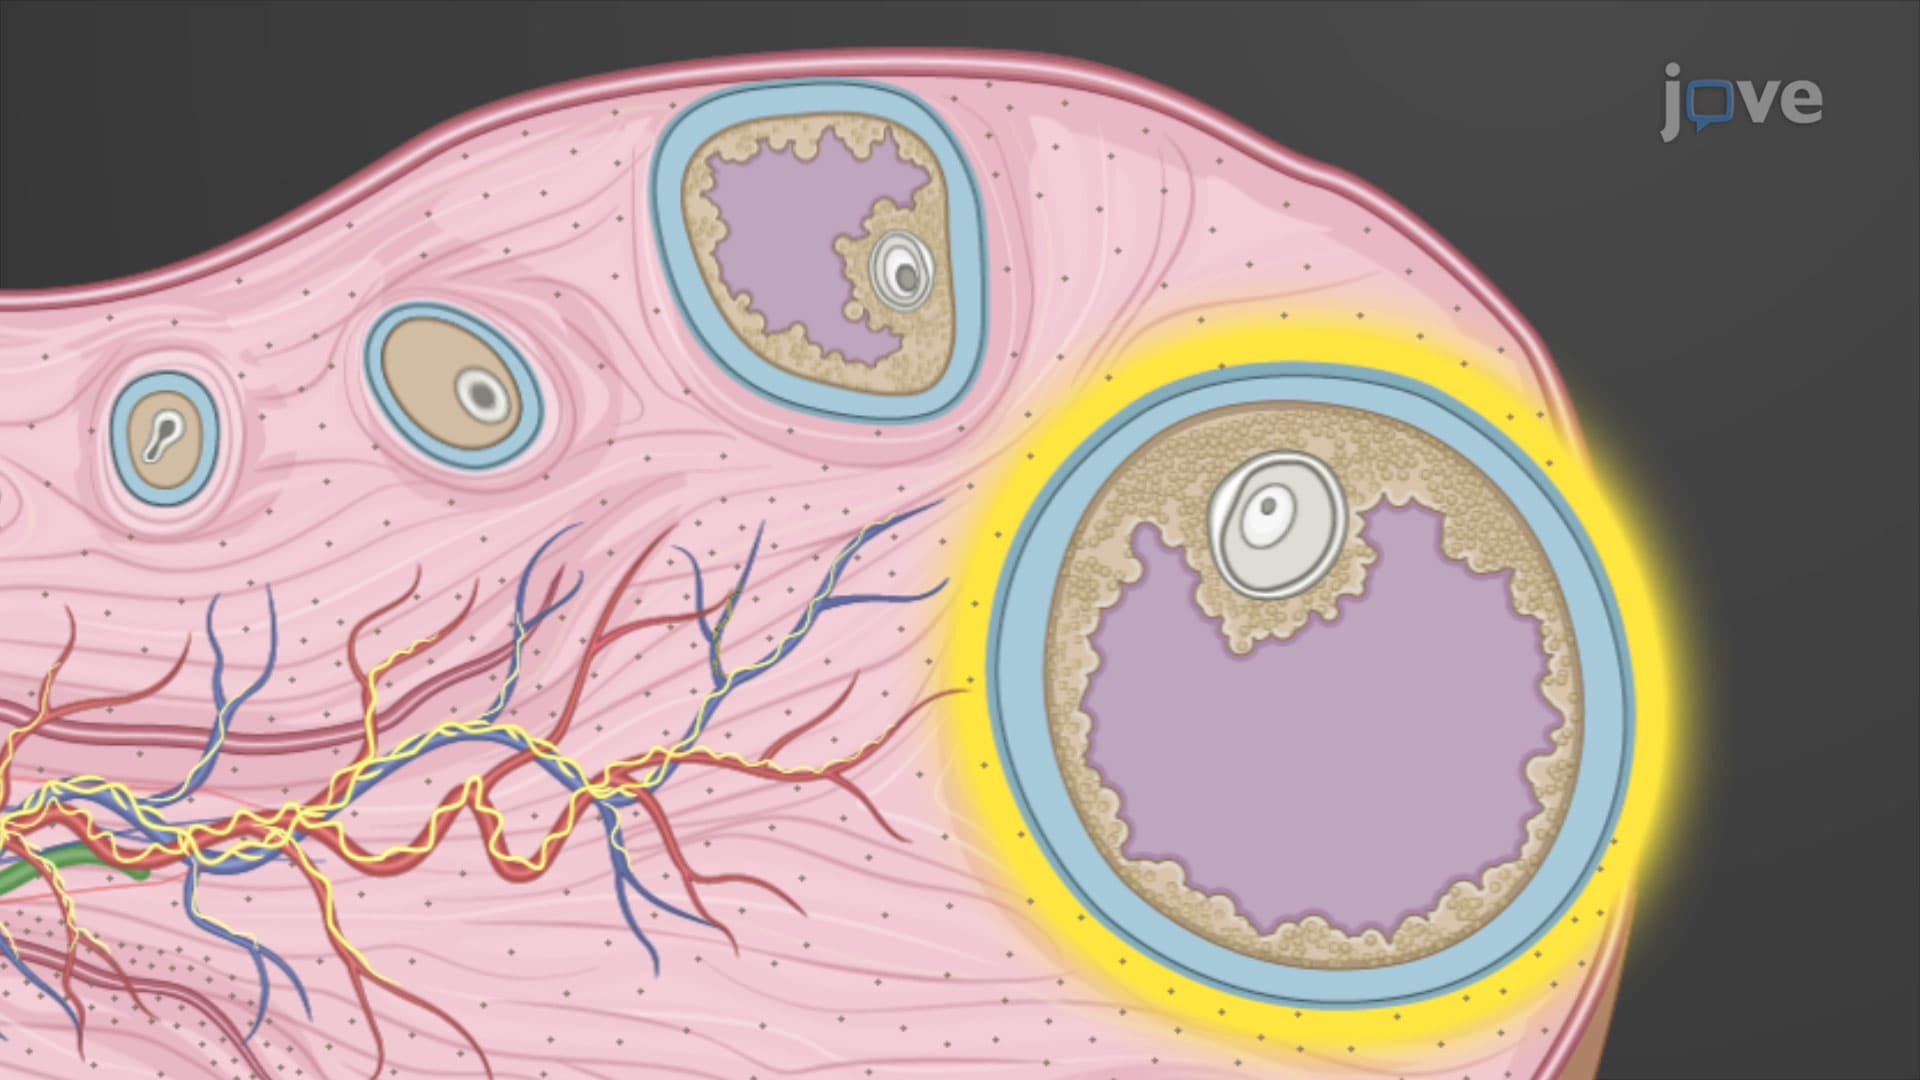
Ovaries
On the ovarian surface, a layer of...