Related Experiment Video
Updated: Jul 25, 2025
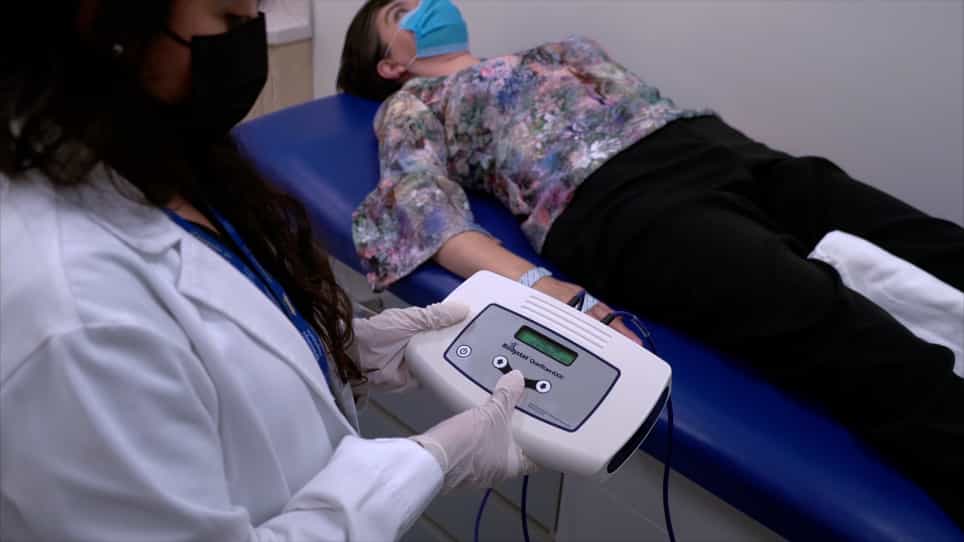

Evaluation of Fluid Overload by Bioelectrical Impedance Vectorial Analysis
Published on: August 17, 2022
Physicians' Clinical Behavior During Fluid Evaluation Encounters
Muhammad K Hayat Syed1, Kathryn Pendleton2, John Park3
1Pulmonary and Critical Care Medicine, Baylor College of Medicine, Houston, TX.

Abstract:
We sought to identify factors affecting physicians' cognition and clinical behavior when evaluating patients that may need fluid therapy.
Background:
Proponents of dynamic fluid responsiveness testing advocate measuring cardiac output or stroke volume after a maneuver to prove that further fluids will increase cardiac output. However, surveys suggest that fluid therapy in clinical practice is often given without prior responsiveness testing.
Design:
Thematic analysis of face-to-face structured interviews.
Setting:
ICUs and medical-surgical wards in acute care hospitals.
Subjects:
Intensivists and hospitalist physicians.
Interventions:
None.
Measurements And Main Results:
We conducted 43 interviews with experienced physicians in 19 hospitals. Hospitalized patients with hypotension, tachycardia, oliguria, or elevated serum lactate are commonly seen by physicians who weigh the risks and benefits of more fluid therapy. Encounters are often with unfamiliar patients and evaluation and decisions are completed quickly without involving other physicians. Dynamic testing for fluid responsiveness is used much less often than static methods and fluid boluses are often ordered with no testing at all. This approach is rationalized by factors that discourage dynamic testing: unavailability of equipment, time to obtain test results, or lack of expertise in obtaining valid data. Two mental calculations are particularly influential: physicians' estimate of the base rate of fluid responsiveness (determined by physical examination, chart review, and previous responses to fluid boluses) and physicians' perception of patient harm if 500 or 1,000 mL fluid boluses are ordered. When the perception of harm is low, physicians use heuristics that rationalize skipping dynamic testing.
Limitations:
Geographic limitation to hospitals in Minnesota, United States.
Conclusions:
If dynamic responsiveness testing is to be used more often in routine clinical practice, physicians must be more convinced of the benefits of dynamic testing, that they can obtain valid results quickly and believe that even small fluid boluses harm their patients.
More Related Videos

Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:30
Heart Failure VII: Nursing Interventions
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:17
Flow Sheet
Here's a closer look at the examples of flowsheets commonly used by nurses:
Graphic Sheet Documentation:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...