Related Experiment Video
Updated: Jul 23, 2025


Cardiac Stress Test Induced by Dobutamine and Monitored by Cardiac Catheterization in Mice
Published on: February 10, 2013
Diagnostic and prognostic value of cardiac stress testing before major noncardiac surgery-A cohort study
Matthew A Pappas1, Andrew D Auerbach2, Michael W Kattan3
1Center for Value-based Care Research, Cleveland Clinic, Cleveland, OH, United States of America; Department of Hospital Medicine, Cleveland Clinic, Cleveland, OH, United States of America; Outcomes Research Consortium, Cleveland, OH, United States of America.

Insights
Preoperative stress testing offers minimal benefit for diagnosing obstructive coronary artery disease (CAD) or predicting perioperative events in patients undergoing noncardiac surgery. Existing data and hemoglobin levels better predict adverse outcomes than stress tests.
Area of Science:
- Cardiology
- Perioperative Medicine
- Diagnostic Accuracy
Background:
- Preoperative risk assessment is crucial for patients undergoing noncardiac surgery.
- The role of stress testing in diagnosing coronary artery disease (CAD) and predicting perioperative events requires clarification.
Purpose of the Study:
- To evaluate the diagnostic and prognostic value of preoperative stress testing.
- To determine if stress test results improve predictions of mortality or myocardial infarction (MI) in patients undergoing noncardiac surgery.
Main Methods:
- Retrospective cohort study of 136,935 patient visits (2008-2018).
- Assessed diagnostic information using the Begg and Greenes method with angiography as the gold standard.
- Evaluated prognostic information by comparing logistic regression models with and without stress test results for predicting 90-day mortality and perioperative MI.
Main Results:
- Stress testing identified new CAD diagnoses in only 4.0% of patients and had limited impact on decisions for angiography.
- Stress test results did not improve predictions of perioperative MI or 90-day mortality.
- Model reweighting and inclusion of hemoglobin levels enhanced outcome prediction.
Conclusions:
- Preoperative cardiac stress testing does not significantly improve predictions of perioperative mortality or MI for noncardiac surgery.
- Few patients have a pretest probability of CAD where stress testing is beneficial for selecting angiography.
- Optimizing existing patient data offers a more effective approach to predicting perioperative adverse events.
Objective:
To assess the incremental contribution of preoperative stress test results toward a diagnosis of obstructive coronary artery disease (CAD), prediction of mortality, or prediction of perioperative myocardial infarction in patients considering noncardiac, nonophthalmologic surgery.
Design, Setting, Participants:
A retrospective cohort study of visits to a preoperative risk assessment and optimization clinic in a large health system between 2008 and 2018.
Measurements:
To assess diagnostic information of preoperative stress testing, we used the Begg and Greenes method to calculate test characteristics adjusted for referral bias, with a gold standard of angiography. To assess prognostic information, we first created multiply-imputed logistic regression models to predict 90-day mortality and perioperative myocardial infarction (MI), starting with two tools commonly used to assess perioperative cardiac risk, Revised Cardiac Risk Index (RCRI) and Myocardial Infarction or Cardiac Arrest (MICA). We then added stress test results and compared the discrimination for models with and without stress test results.
Main Results:
Among 136,935 visits by patients without an existing diagnosis of CAD, the decision to obtain preoperative stress testing identified around 4.0% of likely new diagnoses. Stress testing increased the likelihood of CAD (likelihood ratio: 1.31), but for over 99% of patients, stress testing should not change a decision on whether to proceed to angiography. In 117,445 visits with subsequent noncardiac surgery, stress test results failed to improve predictions of either perioperative MI or 90-day mortality. Reweighting the models and adding hemoglobin improved the prediction of both outcomes.
Conclusions:
Cardiac stress testing before noncardiac, nonophthalmologic surgery does not improve predictions of either perioperative mortality or myocardial infarction. Very few patients considering noncardiac, nonophthalmologic surgery have a pretest probability of CAD in a range where stress testing could usefully select patients for angiography. Better use of existing patient data could improve predictions of perioperative adverse events without additional patient testing.
More Related Videos
 12:12
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Related Concept Videos
 01:26
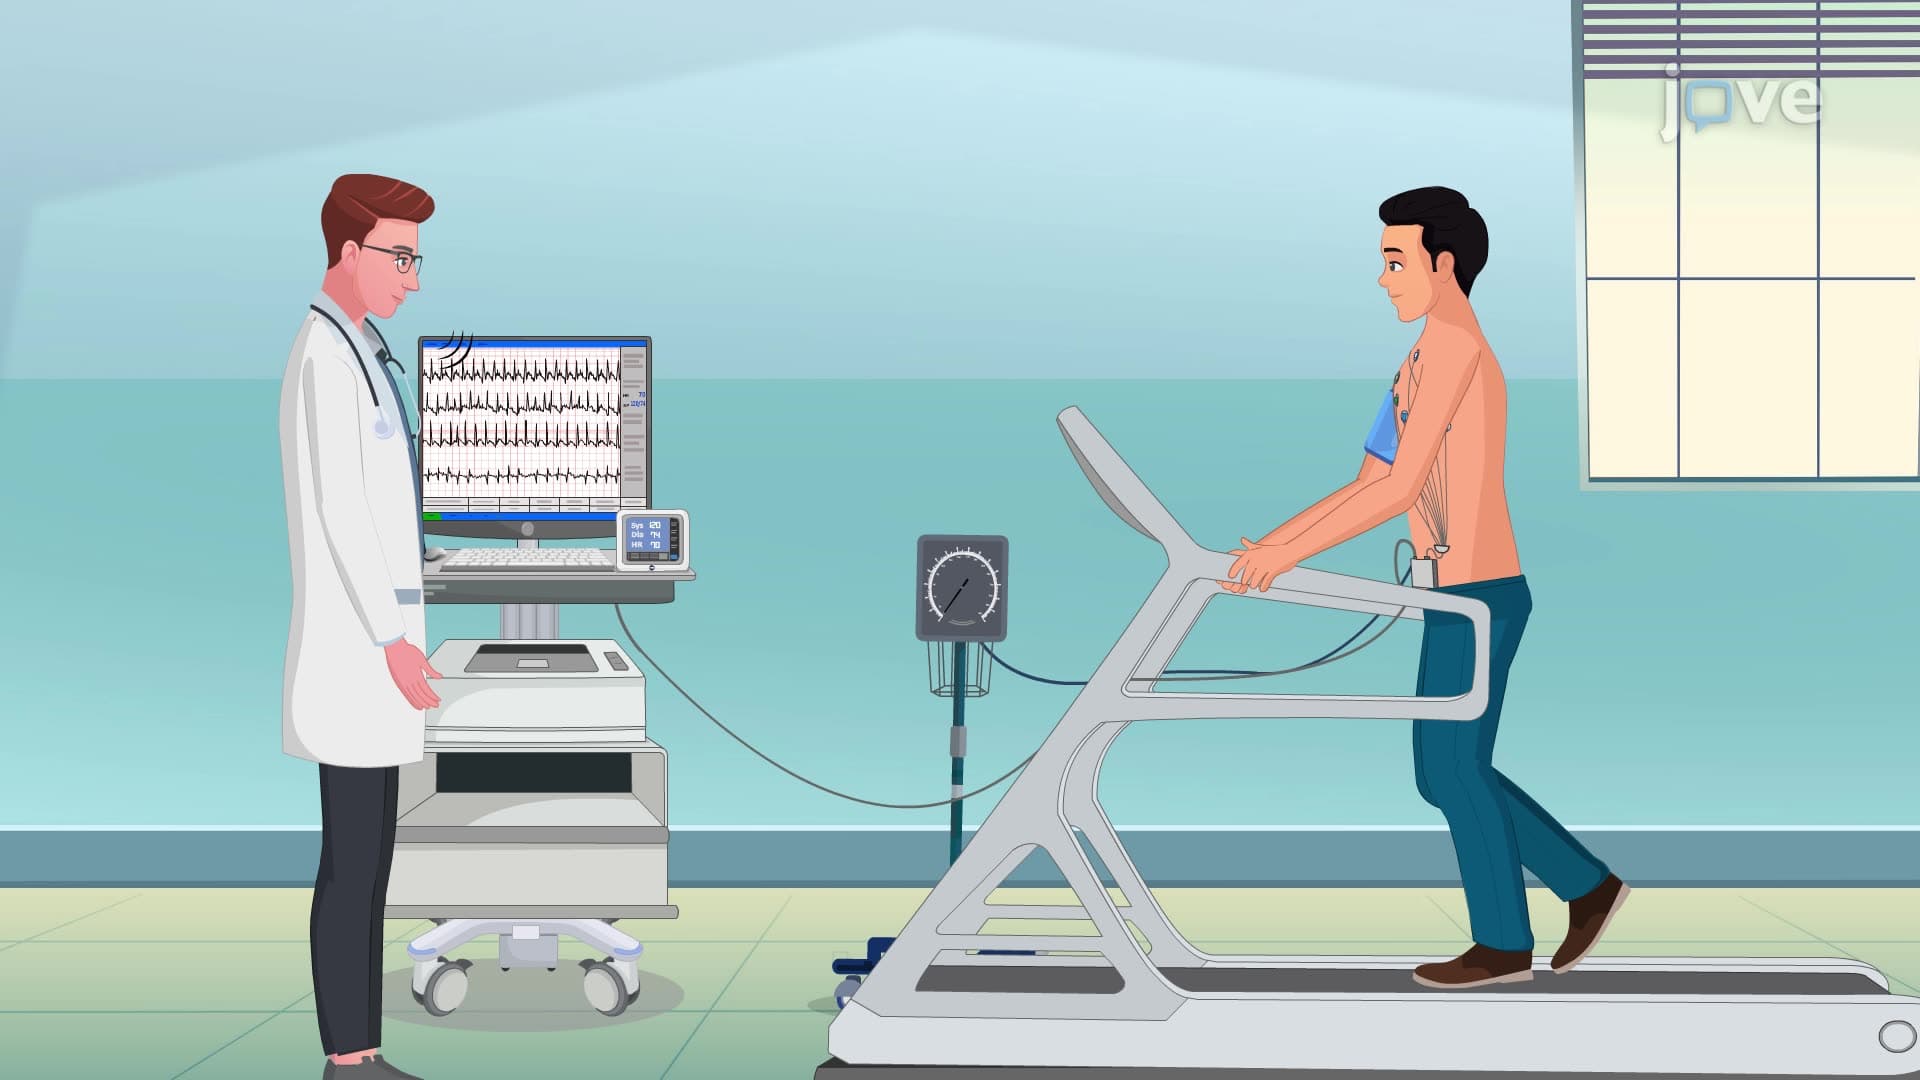
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:30
Dysrhythmias V: Evaluating Dysrhythmias