Related Experiment Video
Updated: Jul 23, 2025
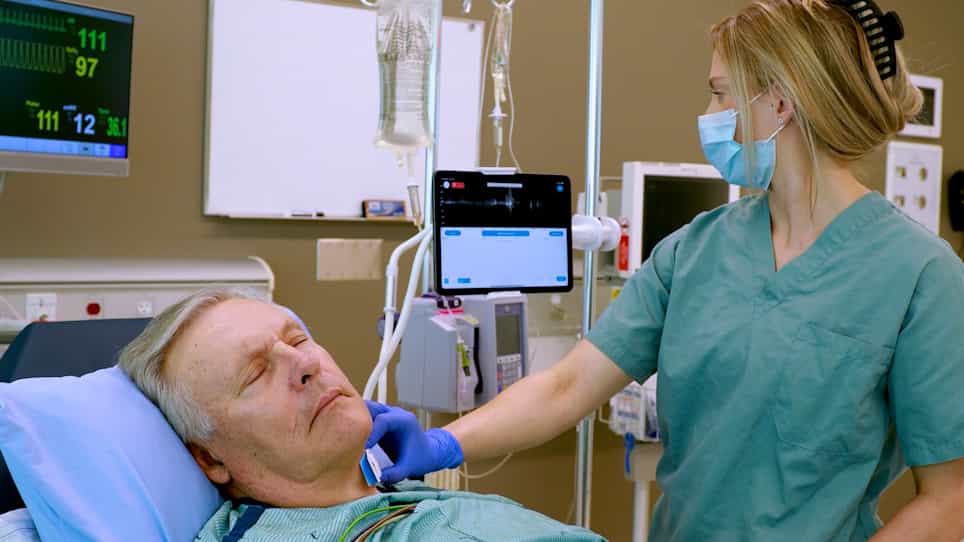

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Performance of Tools and Measures to Predict Fluid Responsiveness in Pediatric Shock and Critical Illness: A
Sarah B Walker1,2, Jessica M Winters3, Jacob M Schauer2
1Department of Pediatrics, Northwestern University Feinberg School of Medicine, Chicago, IL.

Insights
Predicting fluid responsiveness in children shows poor overall performance. Pediatric intensive care unit (PICU) settings decrease accuracy, while shock states improve it, suggesting targeted research is needed.
Area of Science:
- Pediatric critical care medicine
- Clinical physiology
- Evidence-based medicine
Background:
- Fluid responsiveness is crucial for managing critically ill children.
- Predictive tools for fluid responsiveness are widely used but their performance varies.
- Understanding factors influencing predictive tool accuracy is essential for optimizing patient care.
Approach:
- A systematic review and meta-analysis of studies published up to May 2022.
- Included studies reported physiological responses to IV fluid administration in pediatric patients (<18 years).
- Analyzed Area Under the Receiver Operating Characteristic Curve (AUROC) for descriptive and meta-analysis.
Key Points:
- Overall predictive performance of fluid responsiveness tools in children was poor (AUROC, 0.66).
- Pediatric intensive care unit (PICU) settings were associated with decreased predictive performance.
- Shock states were associated with increased predictive performance of fluid responsiveness tools.
Conclusions:
- Further research should focus on assessing predictive tool performance during shock resuscitation.
- Future studies need to differentiate predictive tools from reference tests, especially with ultrasound.
- Research should prioritize reducing time in shock states over solely increasing preload.
Objectives:
In this systematic review and meta-analysis we asked: Do predictors of fluid responsiveness in children perform comparably: 1) in the PICU as in non-PICU settings? 2) in shock states compared with nonshock states? Additionally, 3) is there an association between preload responsiveness and clinical response?
Data Sources:
Ovid Medline, PubMed, and Embase databases were searched from inception through May 2022.
Study Selection:
Included studies reported physiological response to IV fluid administration in humans less than 18 years. Only studies reporting an area under the receiver operating characteristic curve (AUROC) were included for descriptive analysis. Only studies for which a se could be estimated were included for meta-analysis.
Data Extraction:
Title, abstract, full text screening, and extraction were completed by two authors (S.B.W., J.M.W.). Variables extracted included predictors ("tools") and outcome measures ("reference tests") of fluid responsiveness, demographic, and clinical variables.
Data Synthesis:
We identified 62 articles containing 204 AUROCs for 55 tools, primarily describing mechanically ventilated children in an operating room or PICU. Meta-analysis across all tools showed poor predictive performance (AUROC, 0.66; 95% CI, 0.63-0.69), although individual performance varied greatly (range, 0.49-0.87). After controlling for PICU setting and shock state, PICU setting was associated with decreased predictive performance (coefficient, -0.56; p = 0.0007), while shock state was associated with increased performance (0.54; p = 0.0006). Effect of PICU setting and shock state on each tool was not statistically significant but analysis was limited by sample size. The association between preload responsiveness and clinical response was rarely studied but results did not suggest an association. Ultrasound measurements were prone to inherent test review and incorporation biases.
Conclusions:
We suggest three opportunities for further research in fluid responsiveness in children: 1) assessing predictive performance of tools during resuscitation in shock states; 2) separating predictive tool from reference test when using ultrasound techniques; and 3) targeting decreasing time in a shock state, rather than just increase in preload.


Related Concept Videos
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...