Related Experiment Video
Updated: Jul 21, 2025

The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Superior Gluteal Nerve Anatomy and Its Injuries: Aiming for a More Secure Surgical Approach of the Pelvic Region
André R Pinho1,2, Maria J Leite2, João Lixa2
1Unit of Anatomy, Department of Biomedicine, Faculty of Medicine, University of Porto, Alameda Professor Hernâni Monteiro, 4200-319 Porto, Portugal.

Abstract:
Because most of the recognized causes of superior gluteal nerve (SGN) injury are iatrogenic, detailed knowledge of the anatomy of the SGN is crucial to prevent its injury associated with surgical procedures. This study aims to describe the precise location of SGN or its branches at the greater sciatic foramen, measure the distances of these neural structures to palpable bony landmarks, and evaluate the possible correlation between these parameters and pelvis size. Twenty human cadaveric hemipelvises were studied. After dissection to expose the SGN or its branches at the greater sciatic foramen, the distances from these neural structures to the greater trochanter (GT), to the anterior superior iliac spine (ASIS), to the posterior superior iliac spine (PSIS), to the ischial tuberosity (IT), and to the greater sciatic notch apex were measured. We found that at the greater sciatic foramen, the SGN emerges as a common trunk in 75% of hemipelvises, and already divided in its superior and inferior branches in 25% of hemipelvises. When the SGN exits the pelvis as a common trunk, it does so, in most cases, in contact with the bone at the apex of the greater sciatic notch or superior to the level of the apex. The median distance from the SGN at the greater sciatic notch to the PSIS, ASIS, GT and IT is 7.6 cm, 10.9 cm, 7.5 cm and 10.8 cm, respectively. We found a positive correlation between some of the analyzed parameters and the size of the pelvis. The anatomical data of this study may serve as pivotal guides during orthopedic pelvic surgery, contributing to minimize SNG iatrogenic lesions with significant implications in the patient's quality of life.

Related Concept Videos
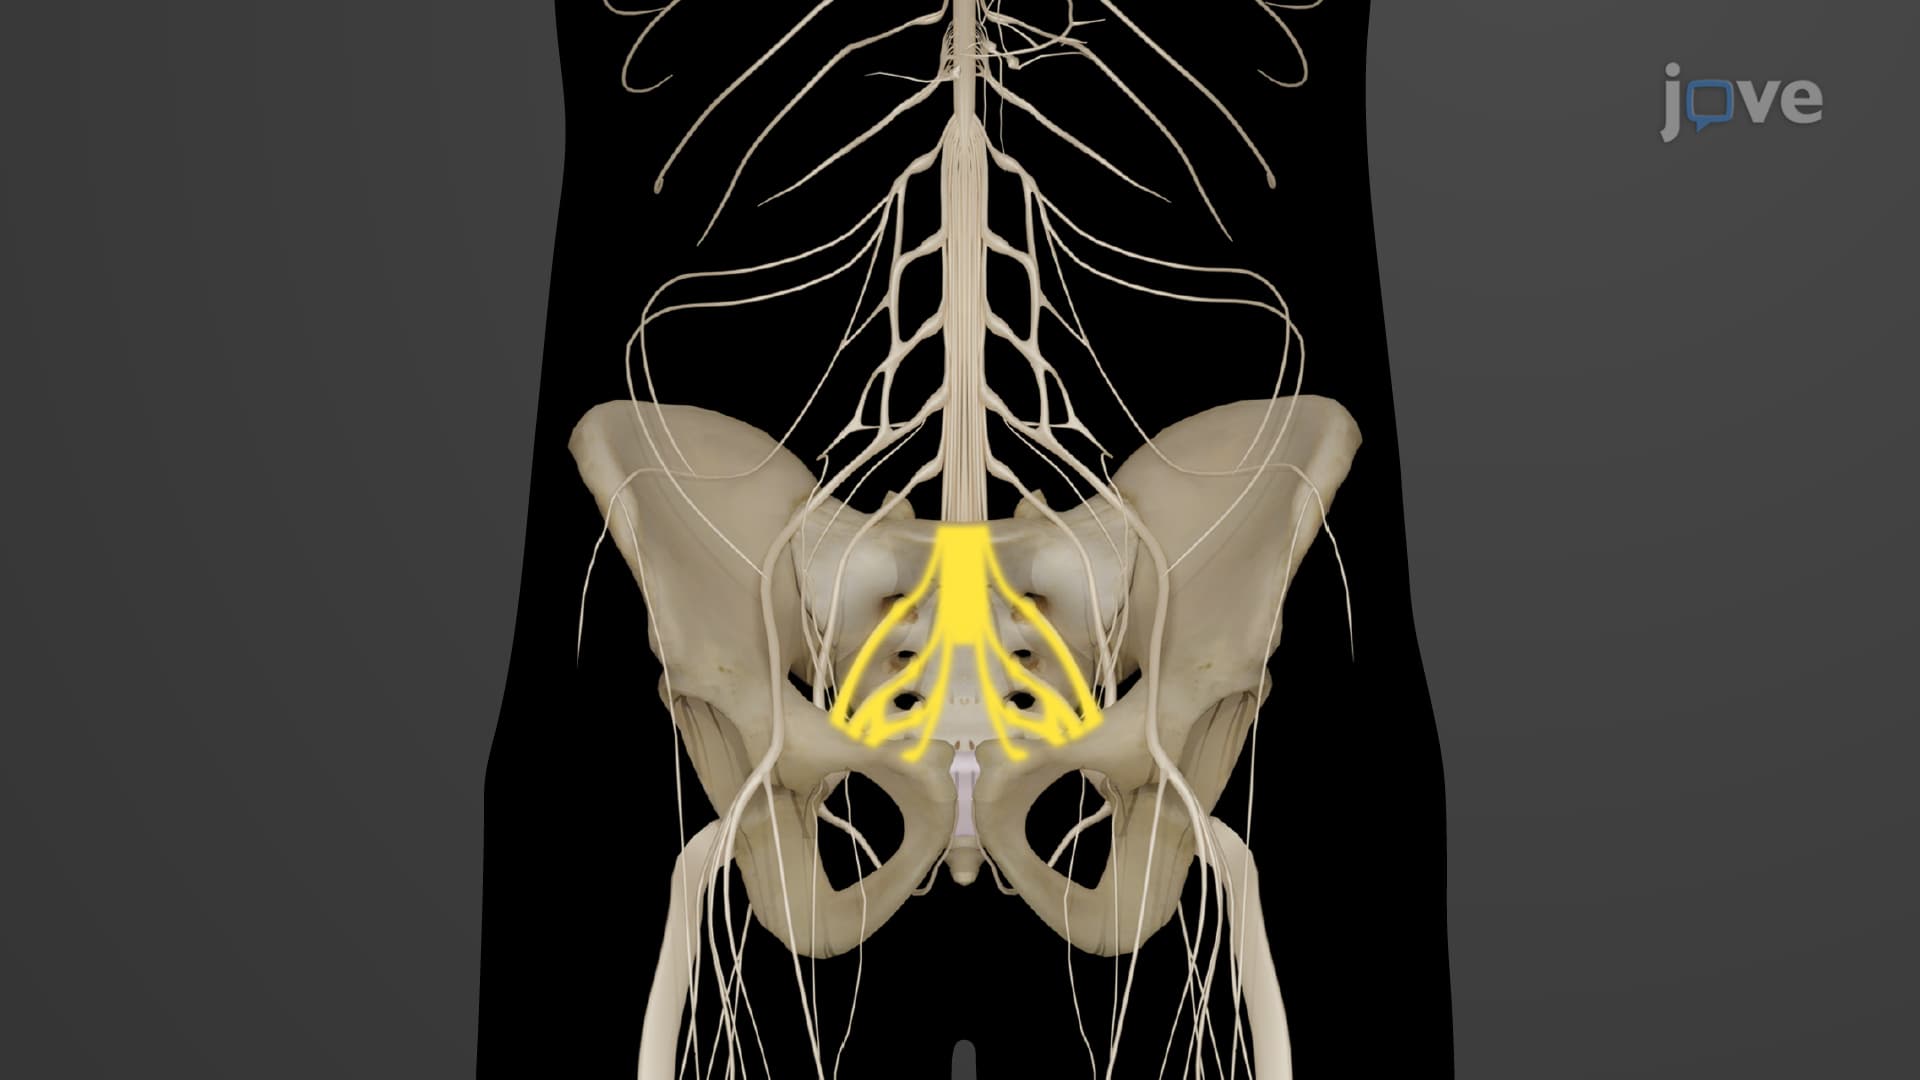 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
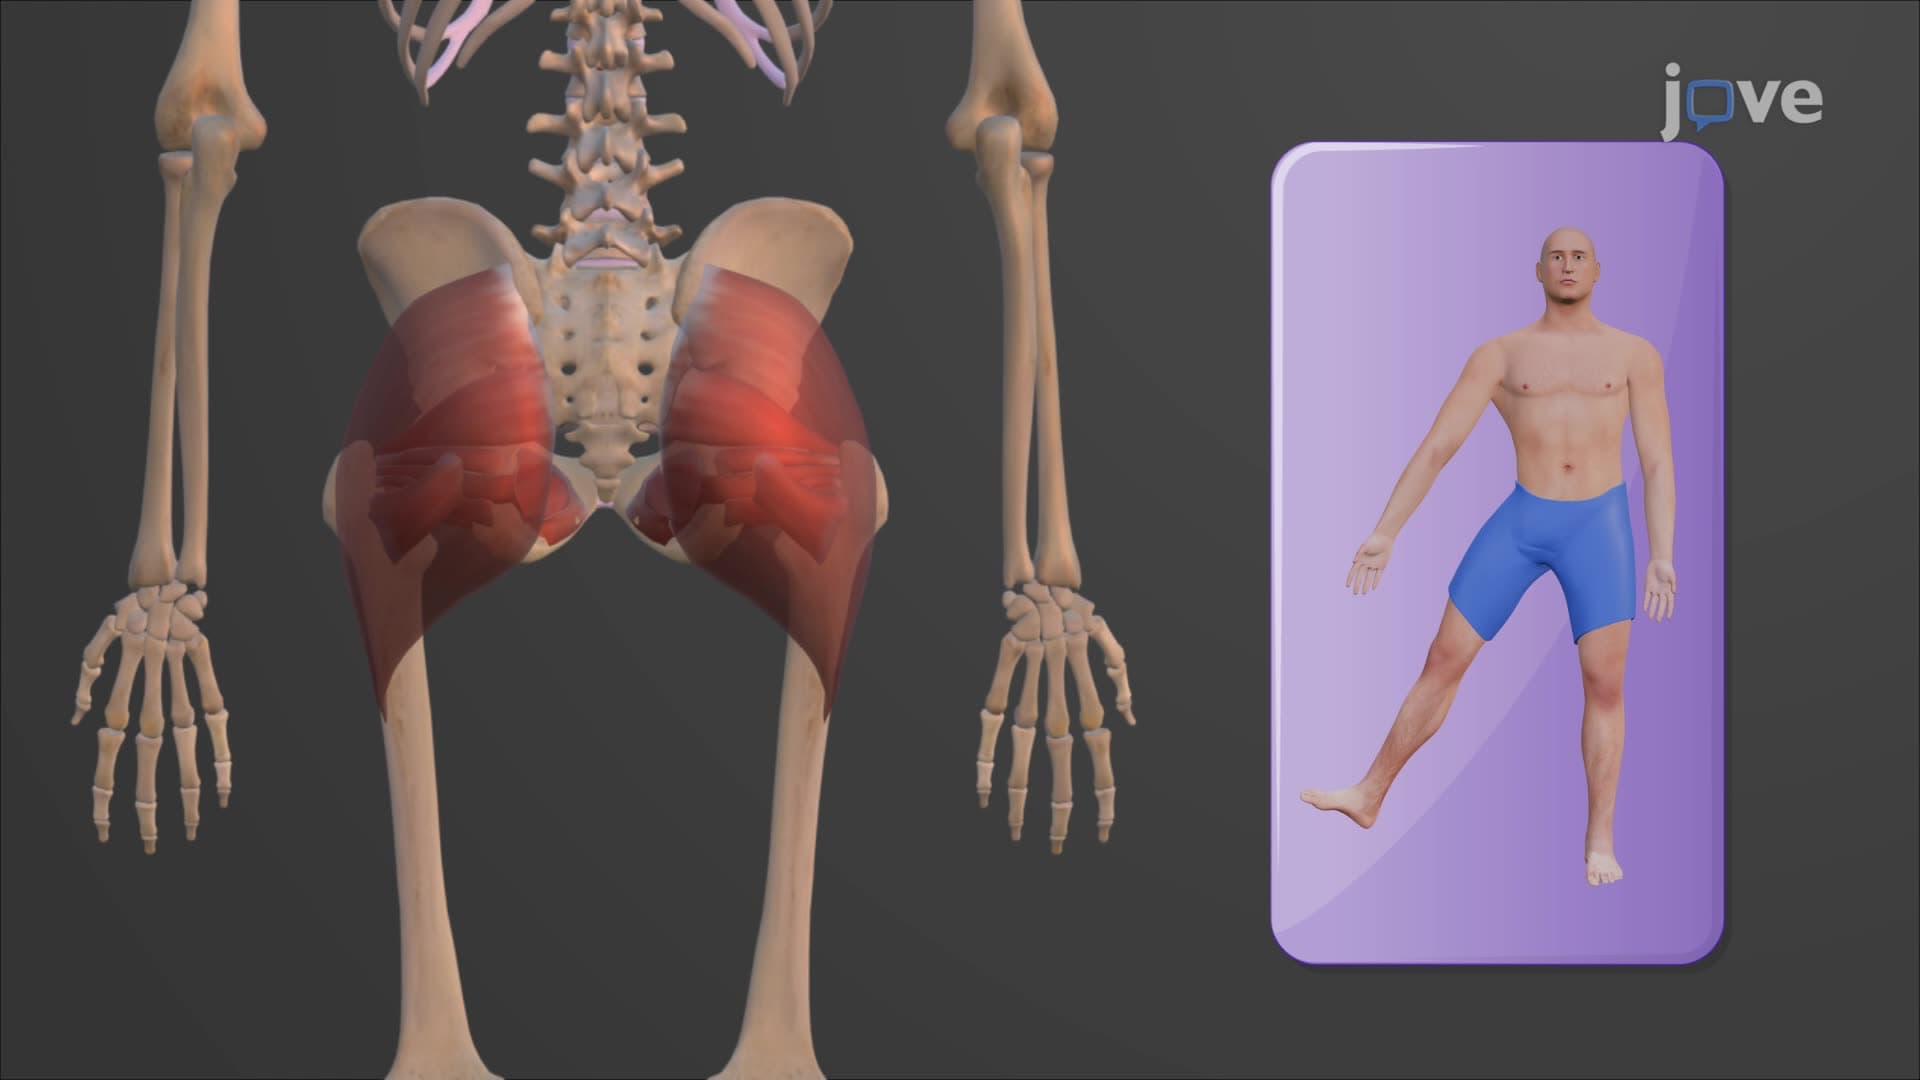 01:20
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar...
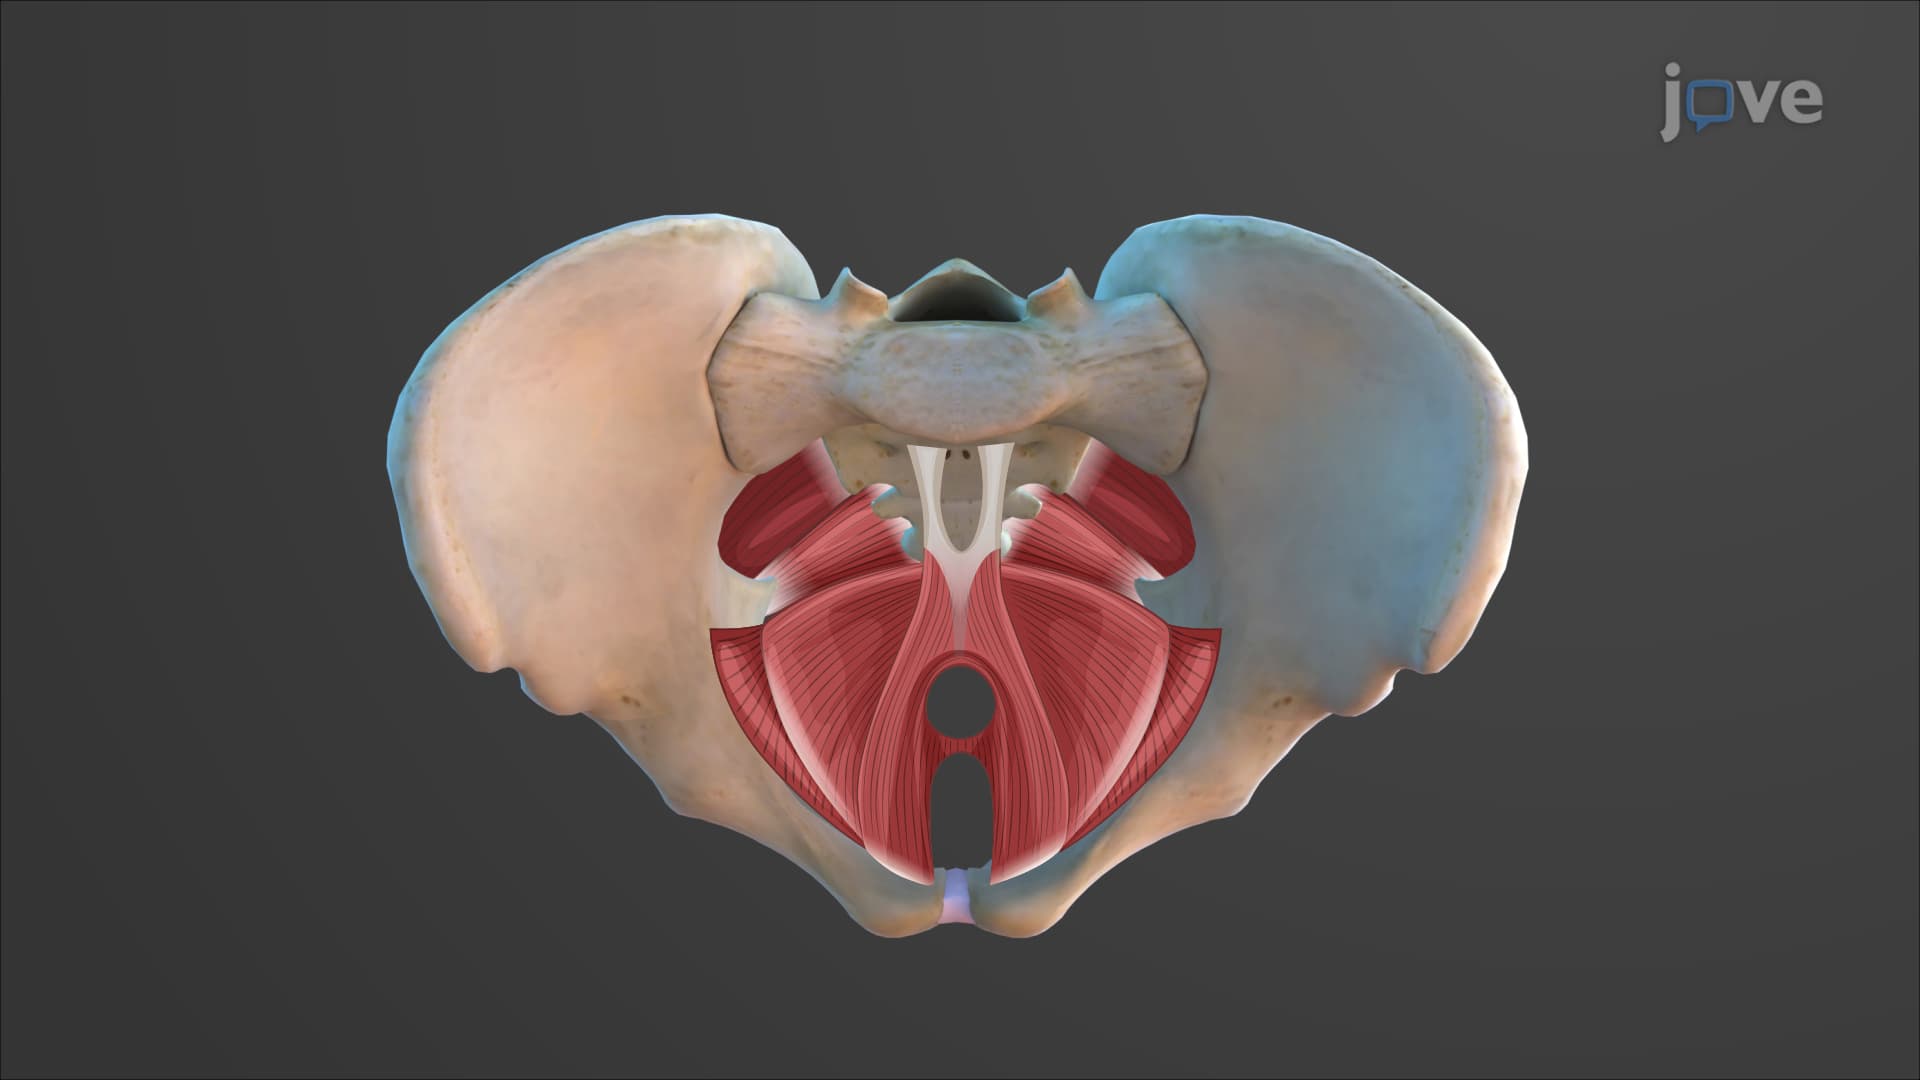 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:20
Arteries of Lower Limbs