Related Experiment Video
Updated: May 7, 2026


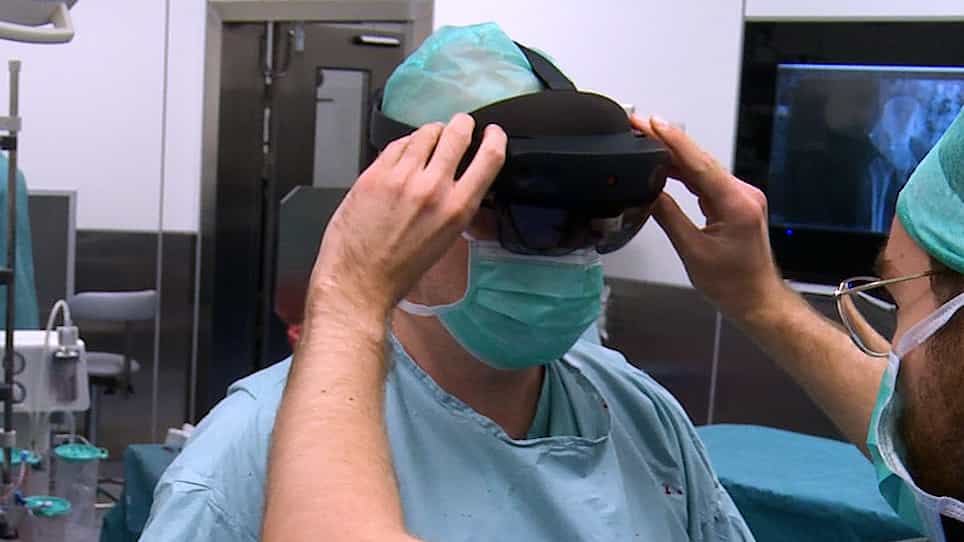
Three-Dimensional Preoperative Virtual Planning in Derotational Proximal Femoral Osteotomy
Published on: February 17, 2023
Variability in preoperative planning software for shoulder arthroplasty
Ana R Senra1,2, Diogo Tomaz1,2, Diogo S Gomes3,4
1Unidade Local de Saúde São João, Porto, Portugal.

Background:
Three-dimensional preoperative planning is increasingly used in shoulder arthroplasty to optimize implant selection and component positioning. Planning platforms rely on either automated best-fit sphere algorithms or manual landmark-based methods to characterize glenoid morphology, potentially introducing variability. This study aimed to compare 5 commercially available planning platforms and to determine whether differences in analytical algorithms explain intersoftware variability.
Methods:
Thirty-three patients were included. Preoperative computed tomography scans were analyzed using Blueprint system (Stryker, Kalamazoo, MI, USA), Equinoxe Planning App (Exactech, Gainesville, FL, USA), Signature ONE Surgical Planning System (Zimmer Biomet, Warsaw, IN, USA), MyShoulder system (Medacta, Castel San Pietro, Switzerland), and LimaCorporate Pre-Op Planning Software (LimaCorporate/Enovis, San Daniele del Friuli, Udine, Italy). Glenoid version, inclination, and humeral head subluxation were assessed. Data analysis included a group evaluation for each variable and pairwise comparisons between software. A comparative analysis between automated and manual assessment methods was performed.
Results:
Significant differences were found between platforms for version (P < .001), inclination (P = .015), and subluxation (P = .032). Agreement was high for subluxation (intraclass correlation coefficient [ICC] = 0.826), moderate to high for version (ICC = 0.749), and low for inclination (ICC = 0.267). Pairwise agreement ranged from 45.5 to 97% for version (highest between Blueprint and LimaCorporate), 30.3-90.9% for inclination, and 60.6-75.8% for subluxation (lowest between Blueprint and LimaCorporate).
Conclusion:
Significant variability exists between preoperative planning software, particularly for inclination. Automated software demonstrated the highest concordance for version but the lowest concordance for subluxation. These results suggest that, even with similar analytical algorithms, uniformity between software is lacking, potentially impacting surgical planning. Methodological standardization is essential to improve reliability and reproducibility of shoulder arthroplasty planning. Surgeons should consider this variability when planning shoulder arthroplasty and interpreting studies with different planning platforms.