Related Experiment Video
Updated: Jul 19, 2025


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Economic analysis of surgical outcome monitoring using control charts: the SHEWHART cluster randomised trial
Sarah Skinner1,2, Léa Pascal3,2, Stéphanie Polazzi3,2
1Research on Healthcare Performance (RESHAPE), INSERM U1290, Université Claude Bernard Lyon 1, Lyon, France sarah.skinner@univ-lyon1.fr.

Importance:
Surgical complications represent a considerable proportion of hospital expenses. Therefore, interventions that improve surgical outcomes could reduce healthcare costs.
Objective:
Evaluate the effects of implementing surgical outcome monitoring using control charts to reduce hospital bed-days within 30 days following surgery, and hospital costs reimbursed for this care by the insurer.
Design:
National, parallel, cluster-randomised SHEWHART trial using a difference-in-difference approach.
Setting:
40 surgical departments from distinct hospitals across France.
Participants:
155 362 patients over the age of 18 years, who underwent hernia repair, cholecystectomy, appendectomy, bariatric, colorectal, hepatopancreatic or oesophageal and gastric surgery were included in analyses.
Intervention:
After the baseline assessment period (2014-2015), hospitals were randomly allocated to the intervention or control groups. In 2017-2018, the 20 hospitals assigned to the intervention were provided quarterly with control charts for monitoring their surgical outcomes (inpatient death, intensive care stay, reoperation and severe complications). At each site, pairs, consisting of one surgeon and a collaborator (surgeon, anaesthesiologist or nurse), were trained to conduct control chart team meetings, display posters in operating rooms, maintain logbooks and design improvement plans.
Main Outcomes:
Number of hospital bed-days per patient within 30 days following surgery, including the index stay and any acute care readmissions related to the occurrence of major adverse events, and hospital costs reimbursed for this care per patient by the insurer.
Results:
Postintervention, hospital bed-days per patient within 30 days following surgery decreased at an adjusted ratio of rate ratio (RRR) of 0.97 (95% CI 0.95 to 0.98; p<0.001), corresponding to a 3.3% reduction (95% CI 2.1% to 4.6%) for intervention hospitals versus control hospitals. Hospital costs reimbursed for this care per patient by the insurer significantly decreased at an adjusted ratio of cost ratio (RCR) of 0.99 (95% CI 0.98 to 1.00; p=0.01), corresponding to a 1.3% decrease (95% CI 0.0% to 2.6%). The consumption of a total of 8910 hospital bed-days (95% CI 5611 to 12 634 bed-days) and €2 615 524 (95% CI €32 366 to €5 405 528) was avoided in the intervention hospitals postintervention.
Conclusions:
Using control charts paired with indicator feedback to surgical teams was associated with significant reductions in hospital bed-days within 30 days following surgery, and hospital costs reimbursed for this care by the insurer.
Trial Registration Number:
NCT02569450.

Related Concept Videos
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:15
Introduction to Statistical Process Control
 00:58
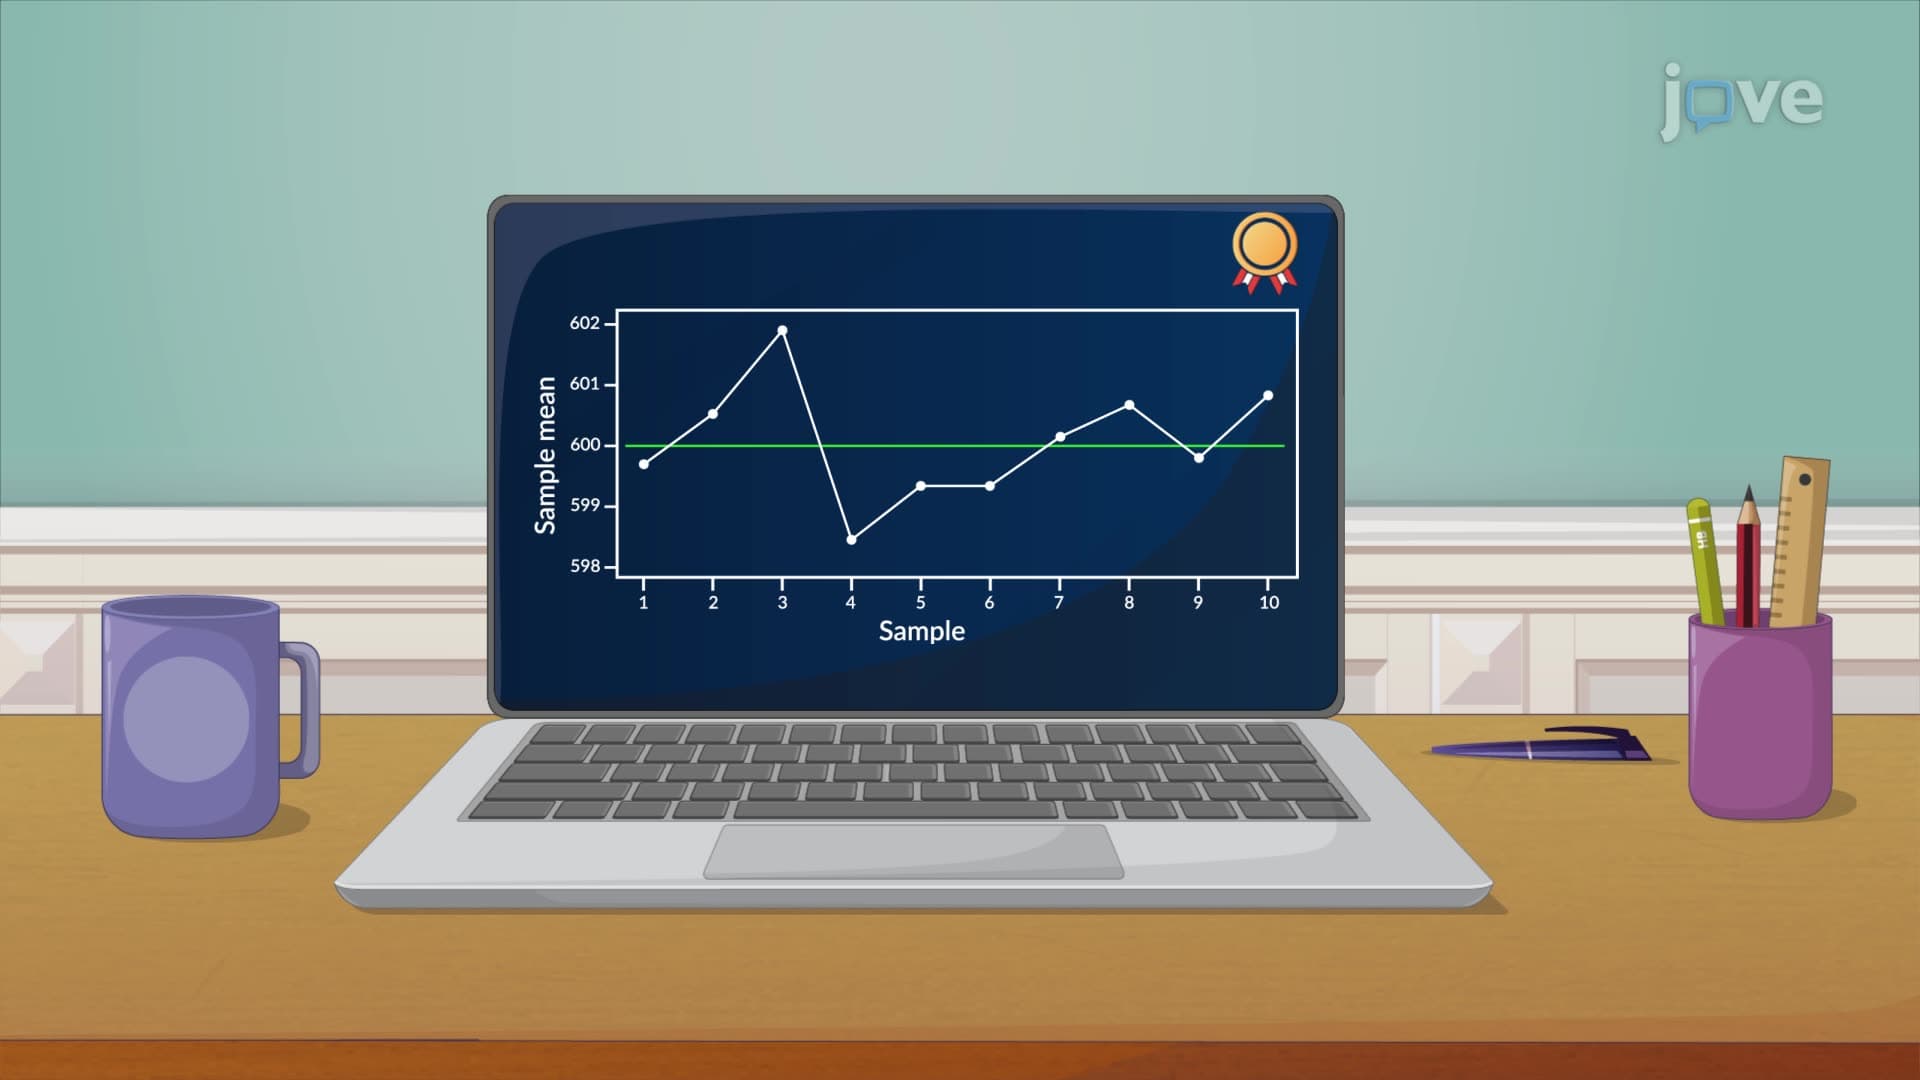
The X̄ Chart
The x̄ chart, often known as the individual control chart, is a crucial tool in statistical process control. It is designed to monitor process behavior and performance over time and is widely used in various industries to ensure that processes are operating at their optimum capacity and within specified limits.
A x̄ chart is constructed by plotting individual measurements of a quality...
 01:21
Cancer Survival Analysis
 01:25
Interpreting Run Charts