Related Experiment Video
Updated: Jul 18, 2025


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Predictors of successful outcome after adrenalectomy for unilateral primary aldosteronism
Ahmed Saadi1, Mohamed Ali Bedoui1, Selim Zaghbib1
1Department of Urology, University of Medicine of Tunis, Charles Nicolle Hospital, Tunis, Tunisia.

Introduction:
Unilateral primary aldosteronism (UPA) is the most frequent surgically curable form of endocrine hypertension. Adrenalectomy is the cornerstone of treatment for UPA, but outcomes after surgery are variable. The cause of resistant hypertension after surgery is still a matter of debate. Our aim was to investigate cure rates after surgery and to evaluate preoperative factors that might influence the surgical outcome.
Methods:
Between 2000 and 2021, the charts of 71 Tunisian patients who underwent laparoscopic adrenalectomy for UPA were retrospectively reviewed. Preoperative medical records were collected and follow-up data (1-158 months) were registered. Antihypertensive medication doses were calculated using defined daily doses (DDD) and postoperative outcomes were assessed using the Primary Aldosteronism Surgical Outcome (PASO) criterion.
Results:
Of 91 enrolled patients, 71 (59% women, mean age 46 years, median length of follow-up 21 months) were suitable for evaluation. Thirty-four patients (48%) had complete clinical success according to the PASO criteria. The most relevant factors associated with complete clinical success on univariate analysis were: absence of diabetes (p= 0.007), low body mass index (BMI) (p= 0.001), lower preoperative DDD (p= 0.01), preoperatively controlled blood pressure (p= 0.024), higher plasma aldosterone to renin ratio (ARR) (p= 0.001), adenoma subtyping (p <0.001) and aldosteronoma resolution score (ARS) (p= 0.002). Multivariate regression analysis showed that the major predictors of complete clinical success were absence of diabetes (OR: 5.205), a BMI < 30 (OR: 4.930), a plasma ARR > 332 (OR: 4.554) and an ARS ≥ 3 (OR: 2.056).
Conclusion:
Complete and partial clinical response rates were achieved in respectively 48 and 43% of cases. The main predictors of complete resolution of hypertension were absence of diabetes, low BMI, high plasma ARR and high ARS. Taking these factors into account may help identify patients at risk of persistent postoperative hypertension who may require long-term surveillance and medication.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:31
Hormones of the Adrenal Glands
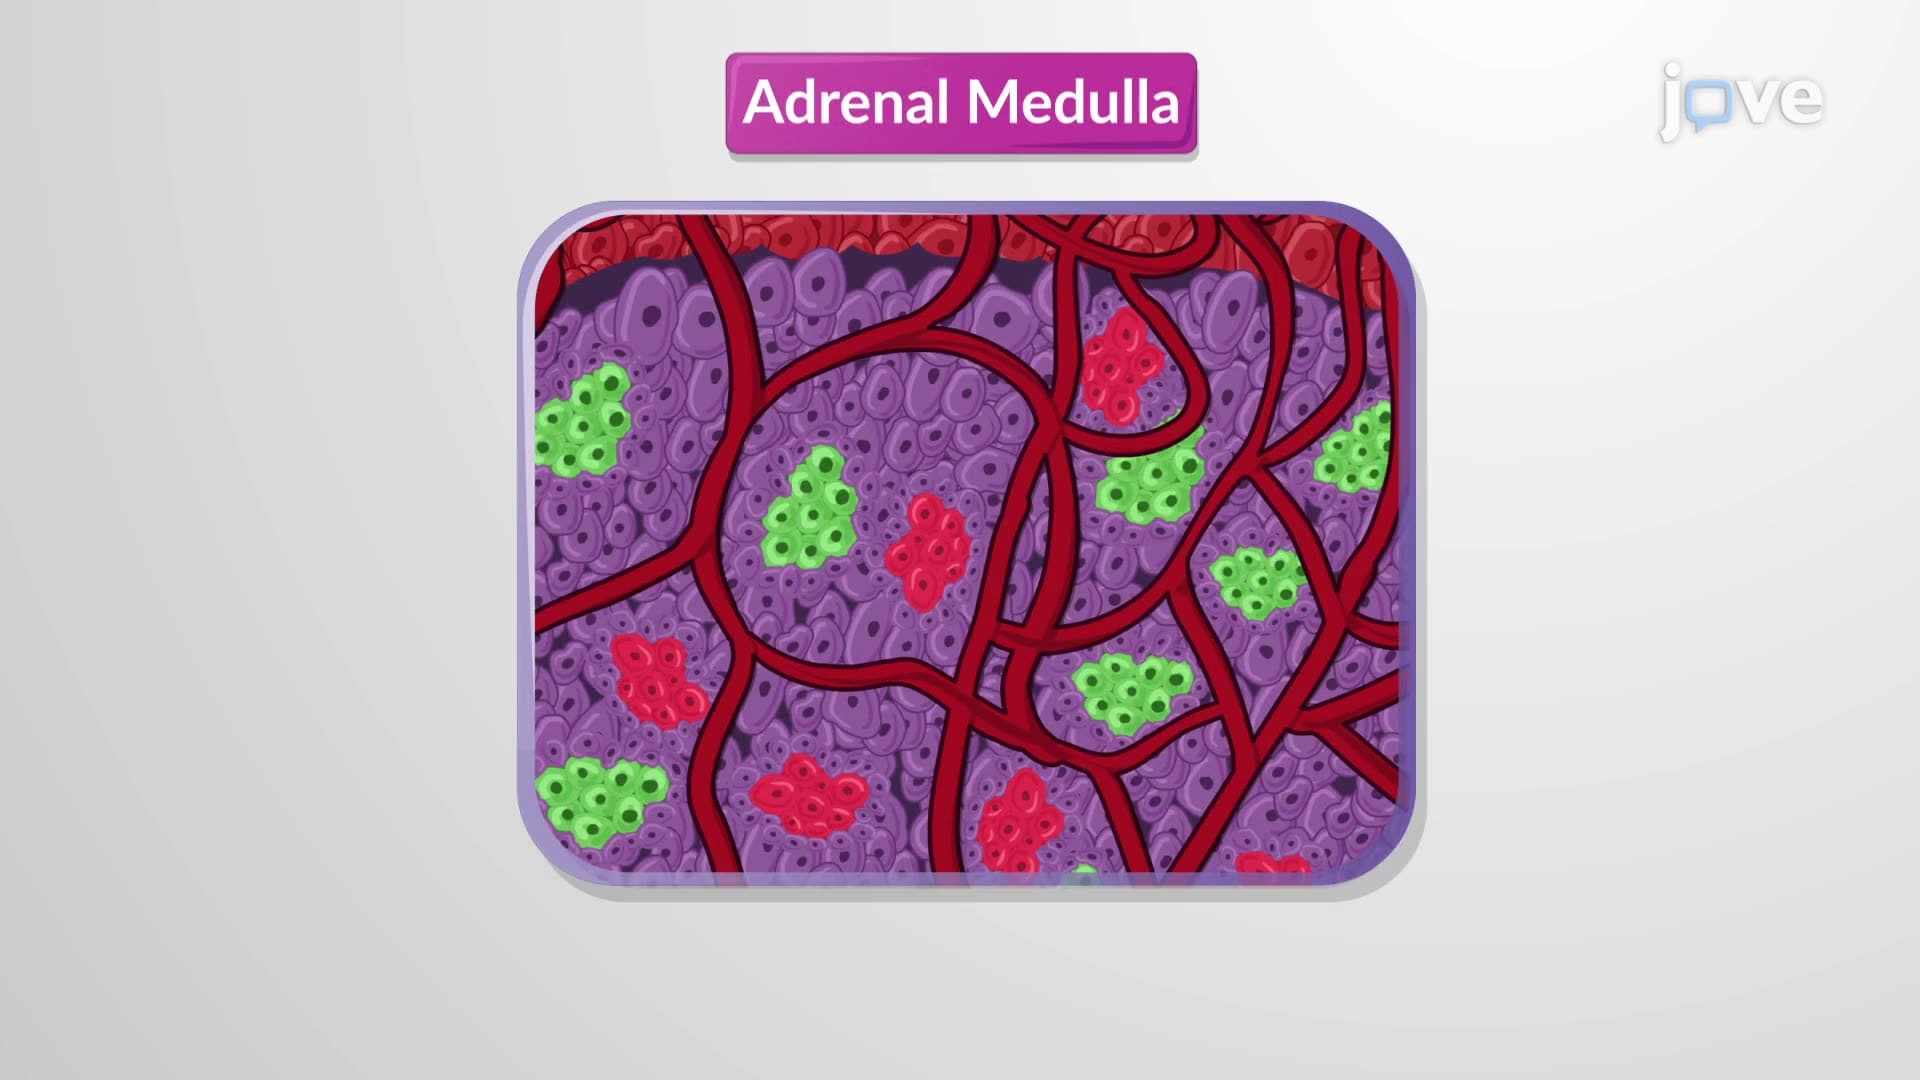
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...
 01:16
Kidney Transplant III: Nursing Management
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:26
Kidney Transplant II: Surgical Procedure