Related Experiment Video
Updated: Jul 17, 2025
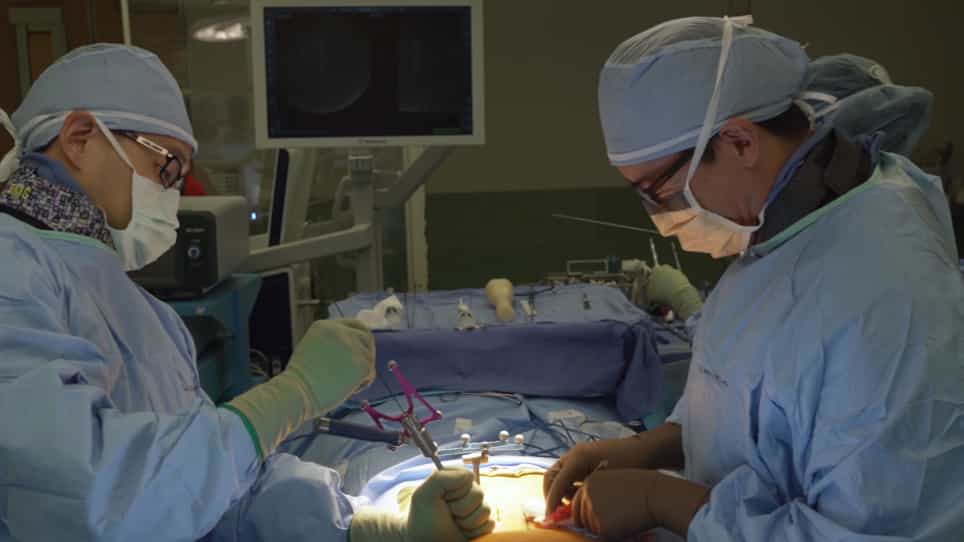

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Influence of resident involvement on fluoroscopy time and ionizing radiation exposure in fluoroscopy-guided spinal
Béatrice Soucy1, Dillon Lee2, Amélie Moreau-Bourbonnais3
1Department of Physical Medicine and Rehabilitation, Centre Hospitalier de l'Université de Montréal, Montréal, Québec, Canada.

Background:
Fluoroscopic guidance has become the standard for a variety of medical procedures. Mastering these techniques requires practice, which may entail additional radiation for patients and providers. Despite their widespread use, the literature examining factors influencing radiation exposure in fluoroscopically guided pain procedures is scarce.
Objective:
To evaluate the influence of resident involvement on radiation exposure during fluoroscopy-guided spinal interventions.
Design:
Single-center, observational study.
Setting:
Outpatient physiatry clinic in a teaching hospital.
Patients:
All patients who received cervical or lumbar facet block(s) (FBs), transforaminal epidural steroid injection(s) (TFESIs) without digital subtraction, or a caudal epidural (CE) during the study period were included.
Interventions:
Resident involvement in the procedures: absent, observing, or participating.
Main Outcome Measures:
Machine-indicated fluoroscopy time (seconds) and radiation dose (milligrays [mGy]).
Results:
Two hundred ninety six procedures were included: 188 FBs (58 cervical, 130 lumbar), 48 CEs, and 60 TFESIs. For lumbar FBs, fluoroscopy time and radiation dose increased significantly when residents performed them (meantime = 24.5 s, confidence interval [CI] = 20.4-28.7; meandose = 3.53 mGy, CI = 2.57-4.49) compared to when they observed (meantime = 9.9 s, CI = 8.1-11.7; meandose = 1.28 mGy, CI = 0.98-1.59) (mean difference: time = 14.63 s, CI = 9.31-19.94; dose = 2.25 mGy, CI = 1.17-3.33) and were absent during the procedure (meantime = 12.9 s, CI = 11.1-14.6; meandose = 1.65 mGy, CI = 1.40-1.89) (mean difference: time = 11.67 s, CI = 7.35-15.98; dose = 1.88 mGy, CI = 1.01-2.76). In the case of TFESIs, time, but not dose, increased significantly when residents observed (meantime = 39.1 s, CI = 30.7-47.6; meandose = 6.73 mGy, CI = 3.39-10.07) compared to when they were absent (meantime = 27.1 s, CI = 22.4-31.8; meandose = 4.41 mGy, CI = 3.06-5.76 (mean difference: time = 11.99 s, CI = 1.37-22.61; dose = 2.32 mGy, CI = -1.20-5.84). Finally, resident involvement did not significantly affect the outcomes for CEs (ptime = .032, pdose = .74) and cervical FBs (ptime = .64, pdose = .68).
Conclusion:
Resident participation affected lumbar FBs the most, with an increase in both fluoroscopy time and radiation dose.


Related Concept Videos
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:13
Radiological Investigation III: Pulmonary Angiogram and PET Scan
Pulmonary Angiogram
A Pulmonary Angiogram is an invasive procedure involving injecting a contrast medium through a catheter threaded into the pulmonary artery or the right side of the heart to visualize the pulmonary vasculature. Computed Tomography (CT) scans have mainly replaced this...