Related Experiment Video
Updated: Jul 17, 2025
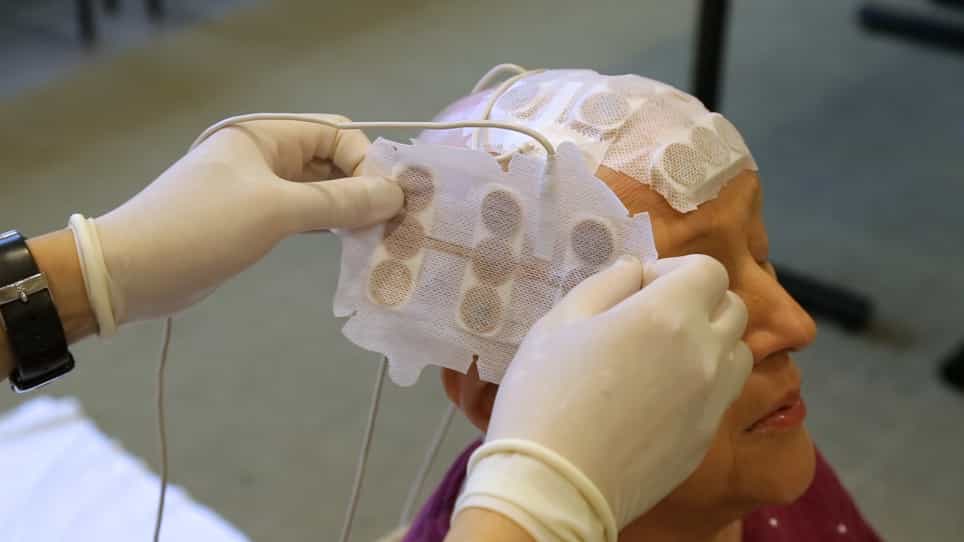
The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Effectiveness and Safety of Different Postoperative Adjuvant Regimens in Patients with Low-Grade Gliomas: A Network
Su Dongpo1, Liu Xiaozhuo2, Li Xin2
1Department of Neurosurgery, North China University of Science and Technology Affiliated Hospital, Tangshan, China; School of Clinical Medicine, Ningxia Medical University, Yinchuan, China.

Objective:
This study aimed to investigate the effectiveness and safety of various adjuvant regimens in patients with low-grade gliomas and to further explore the optimal adjuvant treatment for patients with low-grade gliomas and the differences in the efficacy of each treatment regimens in different tumor types.
Methods:
A comprehensive search of the PubMed, Cochrane Library, Ovid, Embase, and Web of Science databases was conducted to screen randomized and nonrandomized controlled trials related to adjuvant therapy in patients with low-grade gliomas. The Cochrane quality assessment method and the Newcastle-Ottawa Scale were used to assess the quality of the included randomized and nonrandomized controlled trials, respectively. The data from previous studies were extracted using Excel and GetData Graph Digitizer 2.26 software, and network meta-analysis was performed using RevMan 5.3 and Stata 16.0 statistical software.
Results:
The specific ranking of 5-year progression-free survival (5-year PFS) for each treatment regimen from the best to the worst in patients with low-grade gliomas was surgery (S) combined with procarbazine, lomustine, and vincristine (S + PCV); surgery combined with standard radiotherapy and PCV multidrug chemotherapy (S + RT + PCV); surgery combined with standard radiotherapy and temozolomide monotherapy (S + RT + TMZ); surgery combined with enhanced radiotherapy (S + H-RT); surgery combined with standard radiotherapy (S + RT); surgery combined with TMZ (S + TMZ); and S. The 5-year overall survival (OS) ranking was S + RT + TMZ, S + RT + PCV, surgery combined with enhanced radiotherapy and TMZ monotherapy (S + H-RT + TMZ), S + H-RT, S + RT, and S. The 2-year progression-free survival ranking was S + RT + TMZ, S + PCV, S + RT, S + RT + PCV, S + TMZ, S + H-RT, and S. The 2-year overall survival ranking was S + RT + TMZ, S + H-RT + TMZ, S + RT, S + RT + PCV, S + H-RT, and S. The incidence of adverse events (≥3) was ranked from highest to lowest as follows: S + RT + PCV, S + RT + TMZ, S + PCV, S + H-RT, S + TMZ, and S + RT. In the isocitrate dehydrogenase 1/2 mutation nonchromosome 1p and 19q chromosome whole arm codeletion (IDHmt/noncoder) group, the S + RT + PCV and S + H-RT regimens had better 5-year PFS and 5-year OS. In the isocitrate dehydrogenase 1/2 mutation and chromosome 1p and 19q chromosome whole arm codeletion (IDHmt/coder) group, the 5-year PFS of each treatment regimen ranked from the best to the worst was S + RT + TMZ, S + RT + PCV, S + H-RT, S + RT, S + TMZ, and S. The order of 5-year OS from the best to the worst was S + H-RT, S + RT + TMZ, S + RT + PCV, S + RT, and S. In the isocitrate dehydrogenase 1/2 wild-type (IDHwt) group, the S + H-RT and S + TMZ regimens had better 5-year PFS.
Conclusions:
This study revealed that both the S + RT + TMZ and S + RT + PCV regimens might be effective therapies for treating patients with low-grade gliomas. Among these, the S + RT + TMZ regimen seemed to be safer but might lead to tumor deterioration. In the IDHmt/coder type, the S + RT + TMZ scheme might have a significant advantage. In the IDHmt/noncoder type, the S + RT + PCV scheme might be more dominant, while in the IDHwt type, the S + H-RT and S + TMZ schemes also might be good treatment options.

