Related Experiment Video
Updated: Jul 6, 2026

A Contusive Model of Unilateral Cervical Spinal Cord Injury Using the Infinite Horizon Impactor
Published on: July 24, 2012
Characterization of the influence of spinopelvic parameters on thoracolumbar trauma
Joseph S Withrow1, Michael D Monterey1, Analisa Narro1
11Department of Neurosurgery, McGovern Medical School, The University of Texas Health Science Center at Houston (UTHealth), Houston.

Objective:
The current Roussouly classification identifies four groups of "normal" sagittal spine morphology, which has greatly expanded the understanding of normal heterogeneity of the spine. While there has been extensive characterization of the influence of spinopelvic parameters on outcomes after degenerative spine surgery, the influence of spinopelvic parameters on thoracolumbar trauma has yet to be described. The goal of this study was to determine if spinopelvic parameters and global spine morphology influence fracture location, fracture morphology, and rate of neurological deficit in the setting of thoracolumbar trauma.
Methods:
Of 2896 patients reviewed in the authors' institutional spine database between January 2014 and April 2020 with an ICD-9/10 diagnosis of thoracolumbar trauma, 514 met the inclusion criteria of acute thoracolumbar fracture on CT and visible femoral heads on sagittal CT. Pelvic incidence (PI) was calculated on sagittal CT. Demographic and clinical data including age, sex, BMI, smoking status, concomitant cervical fracture, mechanism of injury, major fracture location, neurological deficit, AO Spine thoracolumbar injury classification, and management type (operative vs nonoperative) were collected. Patients were stratified into high-PI (≥ 50°) and low-PI (< 50°) groups.
Results:
Patients with high PI had a lower incidence of fractures in the lower lumbar spine (below L2) compared with patients with low PI (16% vs 8%, p < 0.01). The last lordotic vertebrae were observed between T10 and L4, and of fractures that occurred at these levels, 75% were at the last lordotic vertebrae. Fall from height was the most common cause of neurological deficit, accounting for 47%. Of the patients presenting with a fall from height, AO Spine type B distraction injuries were more common in the high-PI group (41% vs 18%, p = 0.01). Similarly, within the same subgroup, AO Spine type A compression injuries were more common in the low-PI group (73% vs 53%, p = 0.01).
Conclusions:
Spinopelvic parameters and sagittal balance influence the location and morphology of thoracolumbar fractures. Fractures of the thoracolumbar junction are strongly associated with the inflection point, which is defined by sagittal alignment. While the importance of considering sagittal balance is known for decision-making in degenerative spinal pathology, further studies are required to determine if spinopelvic parameters and sagittal balance should play a role in the decision-making for management of thoracolumbar fractures.
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:29
Blood and Nerve Supply to the Bones
Nutrient Artery
The nutrient artery is the main blood vessel that enters the diaphysis via the nutrient foramen. While most long bones have only one nutrient foramen, large bones, such as the femur, may have two. This...
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
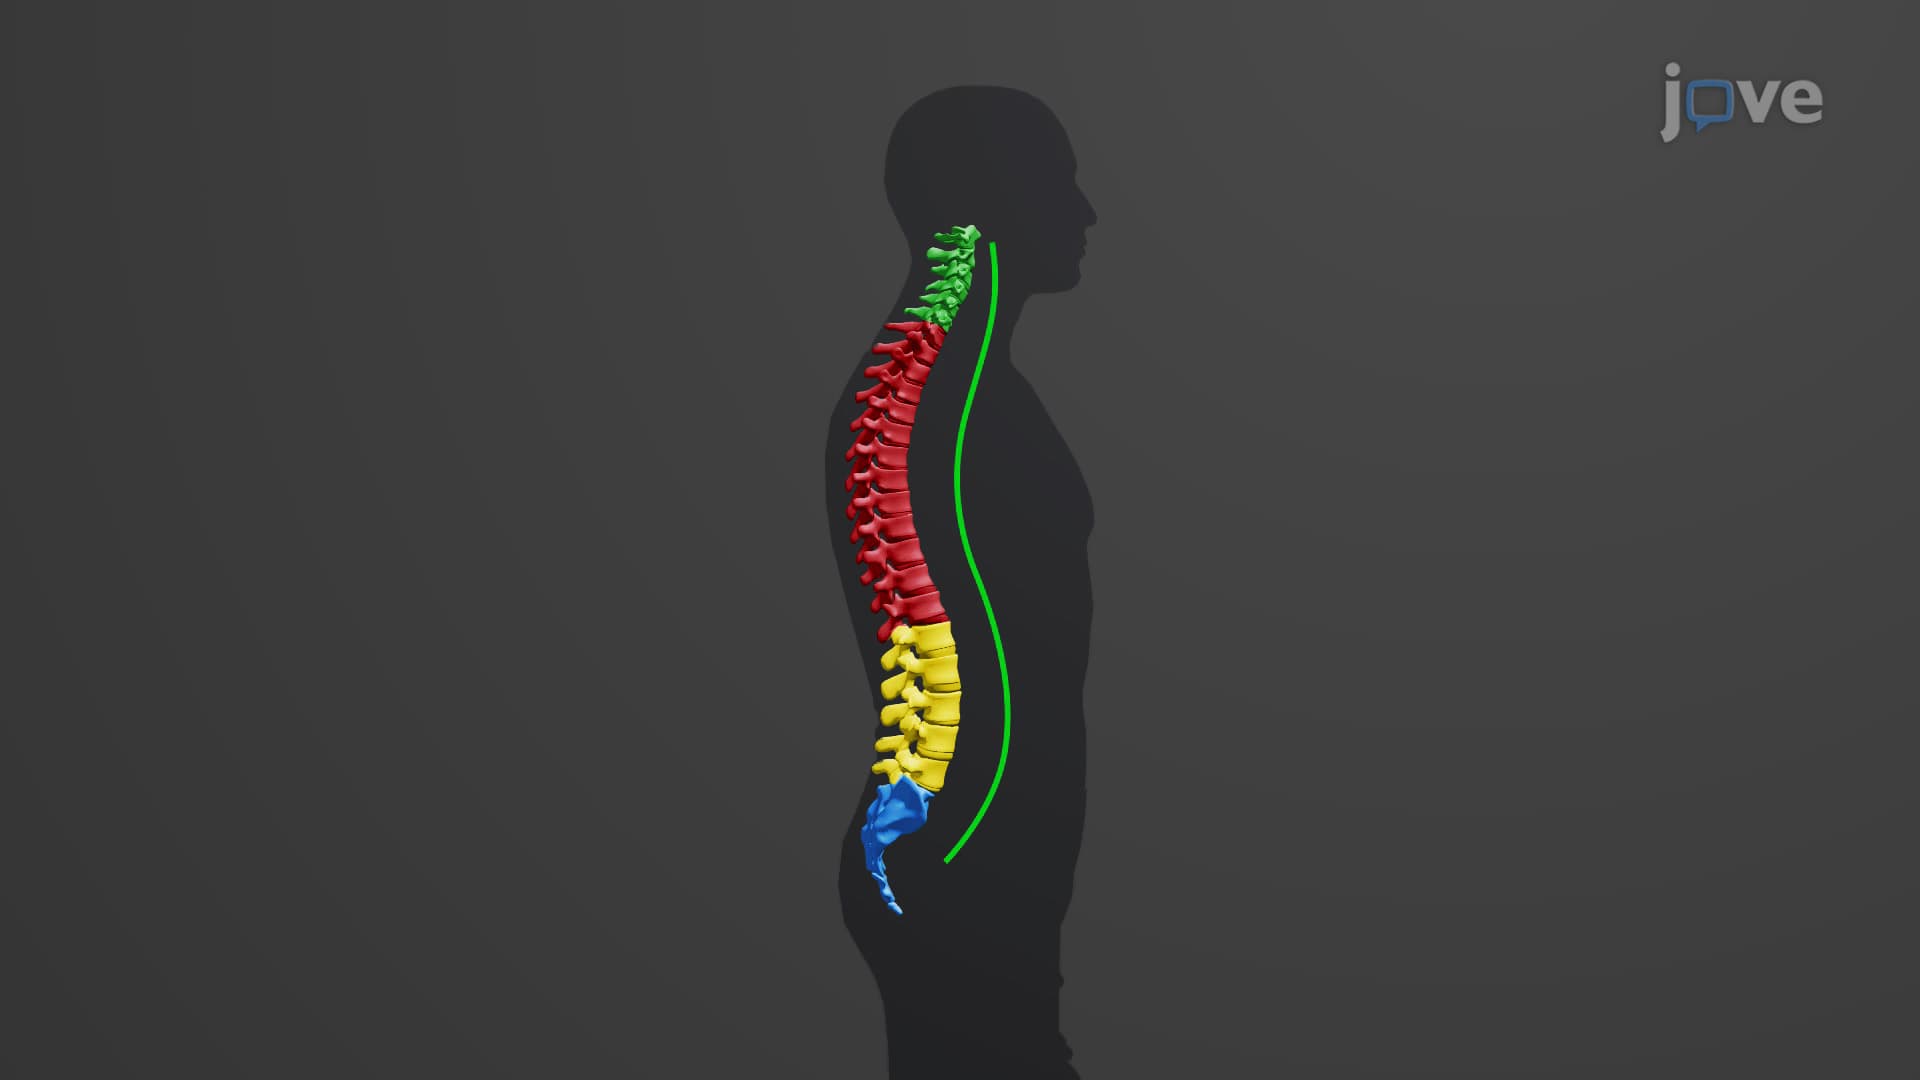
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:29
Herniated Intervertebral Disc l: Introduction