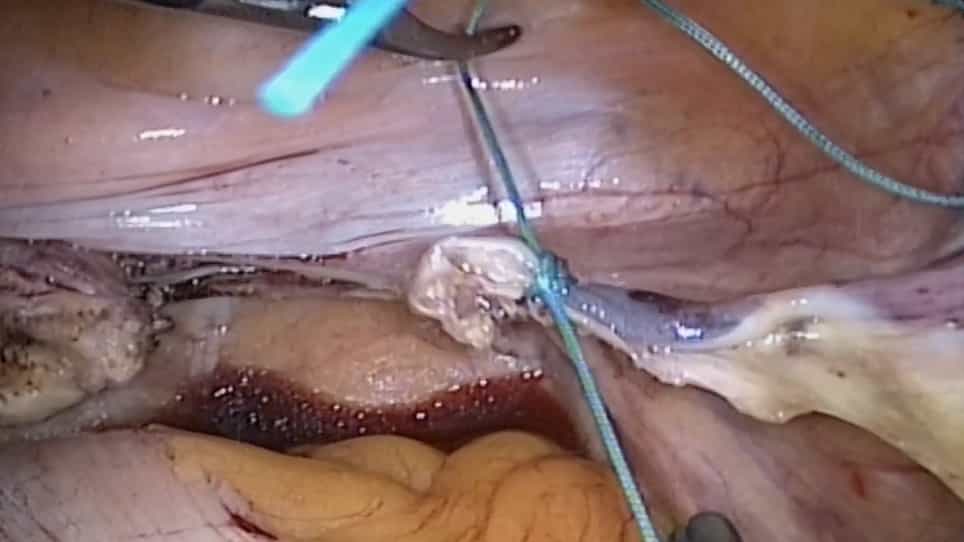
Related Experiment Video
Updated: Jul 15, 2025


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Current Clinical Practice Patterns in Total Vaginal Hysterectomy
Bayley Clarke1, Alexis A Dieter1, JiLing Chou2
1From the Section of Female Pelvic Medicine and Reconstructive Surgery, MedStar Washington Hospital Center/Georgetown University School of Medicine, Washington, DC.

Objectives:
There are no data on current surgical practice patterns for benign total vaginal hysterectomy (TVH) despite recently published guidelines. The objective was to determine gynecologic surgeon practice patterns regarding TVH perioperative interventions and to assess adherence to clinical practice guidelines.
Methods:
A survey to assess TVH practice patterns was distributed to gynecologic surgical society members for completion. The primary outcome was to compare adherence to practice guidelines between fellowship-trained and non-fellowship-trained gynecologic surgeons. Secondary outcomes included comparing adherence based on age, practice location, and hysterectomy volume.
Results:
Of the 204 respondents, there were 163 (80%) fellowship-trained and 41 (20%) non-fellowship-trained gynecologic surgeons. Fellowship-trained surgeons were more likely than non-fellowship-trained surgeons to use vaginal packing (34% vs 15%, P = 0.028), which is contrary to the recommendations. No cohort followed the guideline recommending a circular cervicovaginal incision. Fellowship-trained surgeons also were more likely than non-fellowship-trained surgeons to use the clamp and suture technique for vessel ligation (88% vs 68%, P = 0.004); otherwise, there were no significant differences between cohorts for adherence to any of the other guidelines. Although fellowship-trained surgeons were adherent to fewer of the guidelines as compared with surgeons without fellowship training, both groups generally adhered to a majority of the clinical practice guidelines for benign TVH.
Conclusions:
This information demonstrates a need for the development of targeted education and interventions to increase the use of evidence-based clinical practice guidelines during TVH for both fellowship-trained and non-fellowship-trained gynecologic surgeons.