Related Experiment Video
Updated: Jul 14, 2025
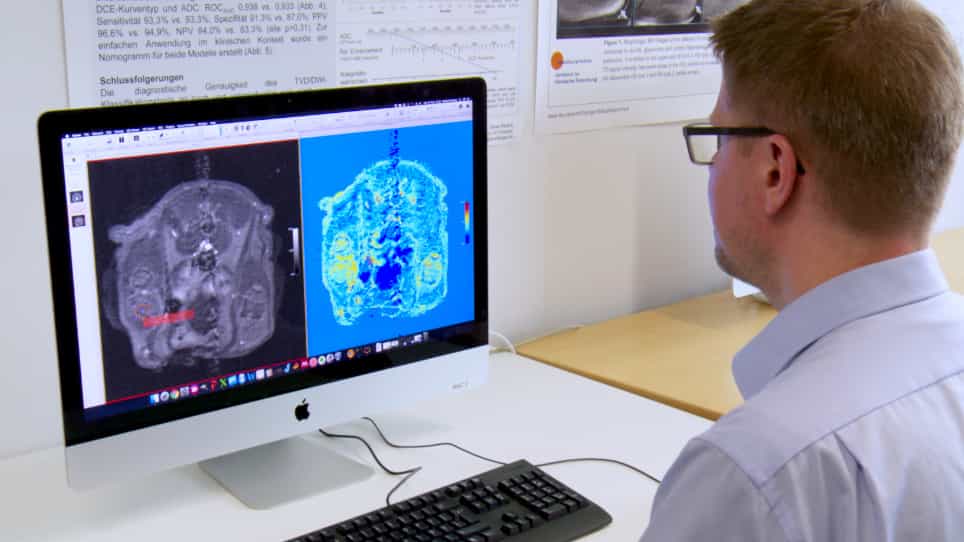

Machine Learning Algorithms for Early Detection of Bone Metastases in an Experimental Rat Model
Published on: August 16, 2020
Accuracy of liver metastasis detection and characterization: Dual-energy CT versus single-energy CT with deep
Corey T Jensen1, Vincenzo K Wong1, Nicolaus A Wagner-Bartak1
1Department of Abdominal Imaging, The University of Texas MD Anderson Cancer Center, 1400 Pressler Street, Unit 1473, Houston, TX 77030-4009, USA.

Purpose:
To assess whether image quality differences between SECT (single-energy CT) and DECT (dual-energy CT 70 keV) with equivalent radiation doses result in altered detection and characterization accuracy of liver metastases when using deep learning image reconstruction (DLIR), and whether DECT spectral curve usage improves accuracy of indeterminate lesion characterization.
Methods:
In this prospective Health Insurance Portability and Accountability Act-compliant study (March through August 2022), adult men and non-pregnant adult women with biopsy-proven colorectal cancer and liver metastases underwent SECT (120 kVp) and a DECT (70 keV) portovenous abdominal CT scan using DLIR in the same breath-hold (Revolution CT ES; GE Healthcare). Participants were excluded if consent could not be obtained, if there were nonequivalent radiation doses between the two scans, or if the examination was cancelled/rescheduled. Three radiologists independently performed lesion detection and characterization during two separate sessions (SECT DLIRmedium and DECT DLIRhigh) as well as reported lesion confidence and overall image quality. Hounsfield units were measured. Spectral HU curves were provided for any lesions rated as indeterminate. McNemar's test was used to test the marginal homogeneity in terms of diagnostic sensitivity, accuracy and lesion detection. A generalized estimating equation method was used for categorical outcomes.
Results:
30 participants (mean age, 58 years ± 11, 21 men) were evaluated. Mean CTDIvol was 34 mGy for both scans. 141 lesions (124 metastases, 17 benign) with a mean size of 0.8 cm ± 0.3 cm were identified. High scores for image quality (scores of 4 or 5) were not significantly different between DECT (N = 71 out of 90 total scores from the three readers) and SECT (N = 62) (OR, 2.01; 95% CI:0.89, 4.57; P = 0.093). Equivalent image noise to SECT DLIRmed (HU SD 10 ± 2) was obtained with DECT DLIRhigh (HU SD 10 ± 3) (P = 1). There was no significant difference in lesion detection between DECT and SECT (140/141 lesions) (99.3%; 95% CI:96.1%, 100%).The mean lesion confidence scores by each reader were 4.2 ± 1.3, 3.9 ± 1.0, and 4.8 ± 0.8 for SECT and 4.1 ± 1.4, 4.0 ± 1.0, and 4.7 ± 0.8 for DECT (odds ratio [OR], 0.83; 95% CI: 0.62, 1.11; P = 0.21). Small lesion (≤5mm) characterization accuracy on SECT and DECT was 89.1% (95% CI:76.4%, 96.4%; 41/46) and 84.8% (71.1%, 93.7%; 39/46), respectively (P = 0.41). Use of spectral HU lesion curves resulted in 34 correct changes in characterizations and no mischaracterizations.
Conclusion:
DECT required a higher strength of DLIR to obtain equivalent noise compared to SECT DLIR. At equivalent radiation doses and image noise, there was no significant difference in subjective image quality or observer lesion performance between DECT (70 keV) and SECT. However, DECT spectral HU curves of indeterminate lesions improved characterization.
More Related Videos
 09:49
Dual-phase Cone-beam Computed Tomography to See, Reach, and Treat Hepatocellular Carcinoma during Drug-eluting Beads Transarterial Chemo-embolization
Published on: December 2, 2013
 08:04
Monitoring Tumor Metastases and Osteolytic Lesions with Bioluminescence and Micro CT Imaging
Published on: April 14, 2011