Related Experiment Video
Updated: Jul 12, 2025
Direct Drug Delivery to Kidney via the Renal Artery
Published on: April 17, 2021
Venetoclax pharmacokinetics in participants with end-stage renal disease undergoing haemodialysis
Behnam Noorani1, Rajeev M Menon1, Xin Chen1
1AbbVie, Inc., North Chicago, Illinois, USA.

Aims:
Renal insufficiency is a common comorbidity in patients with haematological malignancies. This study aimed to assess how end-stage renal disease (ESRD) might affect the pharmacokinetics of venetoclax, a Bcl-2 inhibitor, in participants with ESRD undergoing haemodialysis.
Methods:
Venetoclax was administered as a single 100-mg dose to 6 female participants with ESRD (estimated glomerular filtration rate <15 mL/min) both prior to haemodialysis and between haemodialysis days and 7 healthy female participants with normal renal function (estimated glomerular filtration rate >90 mL/min). Intensive pharmacokinetic and protein binding samples were collected from all participants. Arterial and venous samples were collected from ESRD participants during haemodialysis to assess the effect of haemodialysis on venetoclax pharmacokinetics. Pharmacokinetic parameters were estimated using noncompartmental methods.
Results:
There was no difference in plasma venetoclax concentrations between arterial and venous samples, suggesting that haemodialysis did not affect the pharmacokinetics of venetoclax. The fraction unbound (fu ) of venetoclax was ~2-fold higher for participants with ESRD compared to participants with normal renal function. The unbound maximum plasma concentration and area under the plasma concentration-time curve from time 0 to 48 h were comparable between ESRD and normal function groups. The mean half-life ranged from 10.4 to 12.2 h across groups, demonstrating that ESRD did not affect the half-life of venetoclax. No new safety signals were observed during this study.
Conclusion:
ESRD and dialysis do not alter unbound venetoclax plasma concentrations. No pharmacokinetics driven dose adjustment is needed for patients with renal insufficiency.
More Related Videos
 06:14
Optimized LC-MS/MS Method for the High-throughput Analysis of Clinical Samples of Ivacaftor, Its Major Metabolites, and Lumacaftor in Biological Fluids of Cystic Fibrosis Patients
Published on: October 15, 2017
 05:34
5/6 Nephrectomy Using Sharp Bipolectomy Via Midline Laparotomy in Rats
Published on: April 4, 2025
Related Concept Videos
 01:15
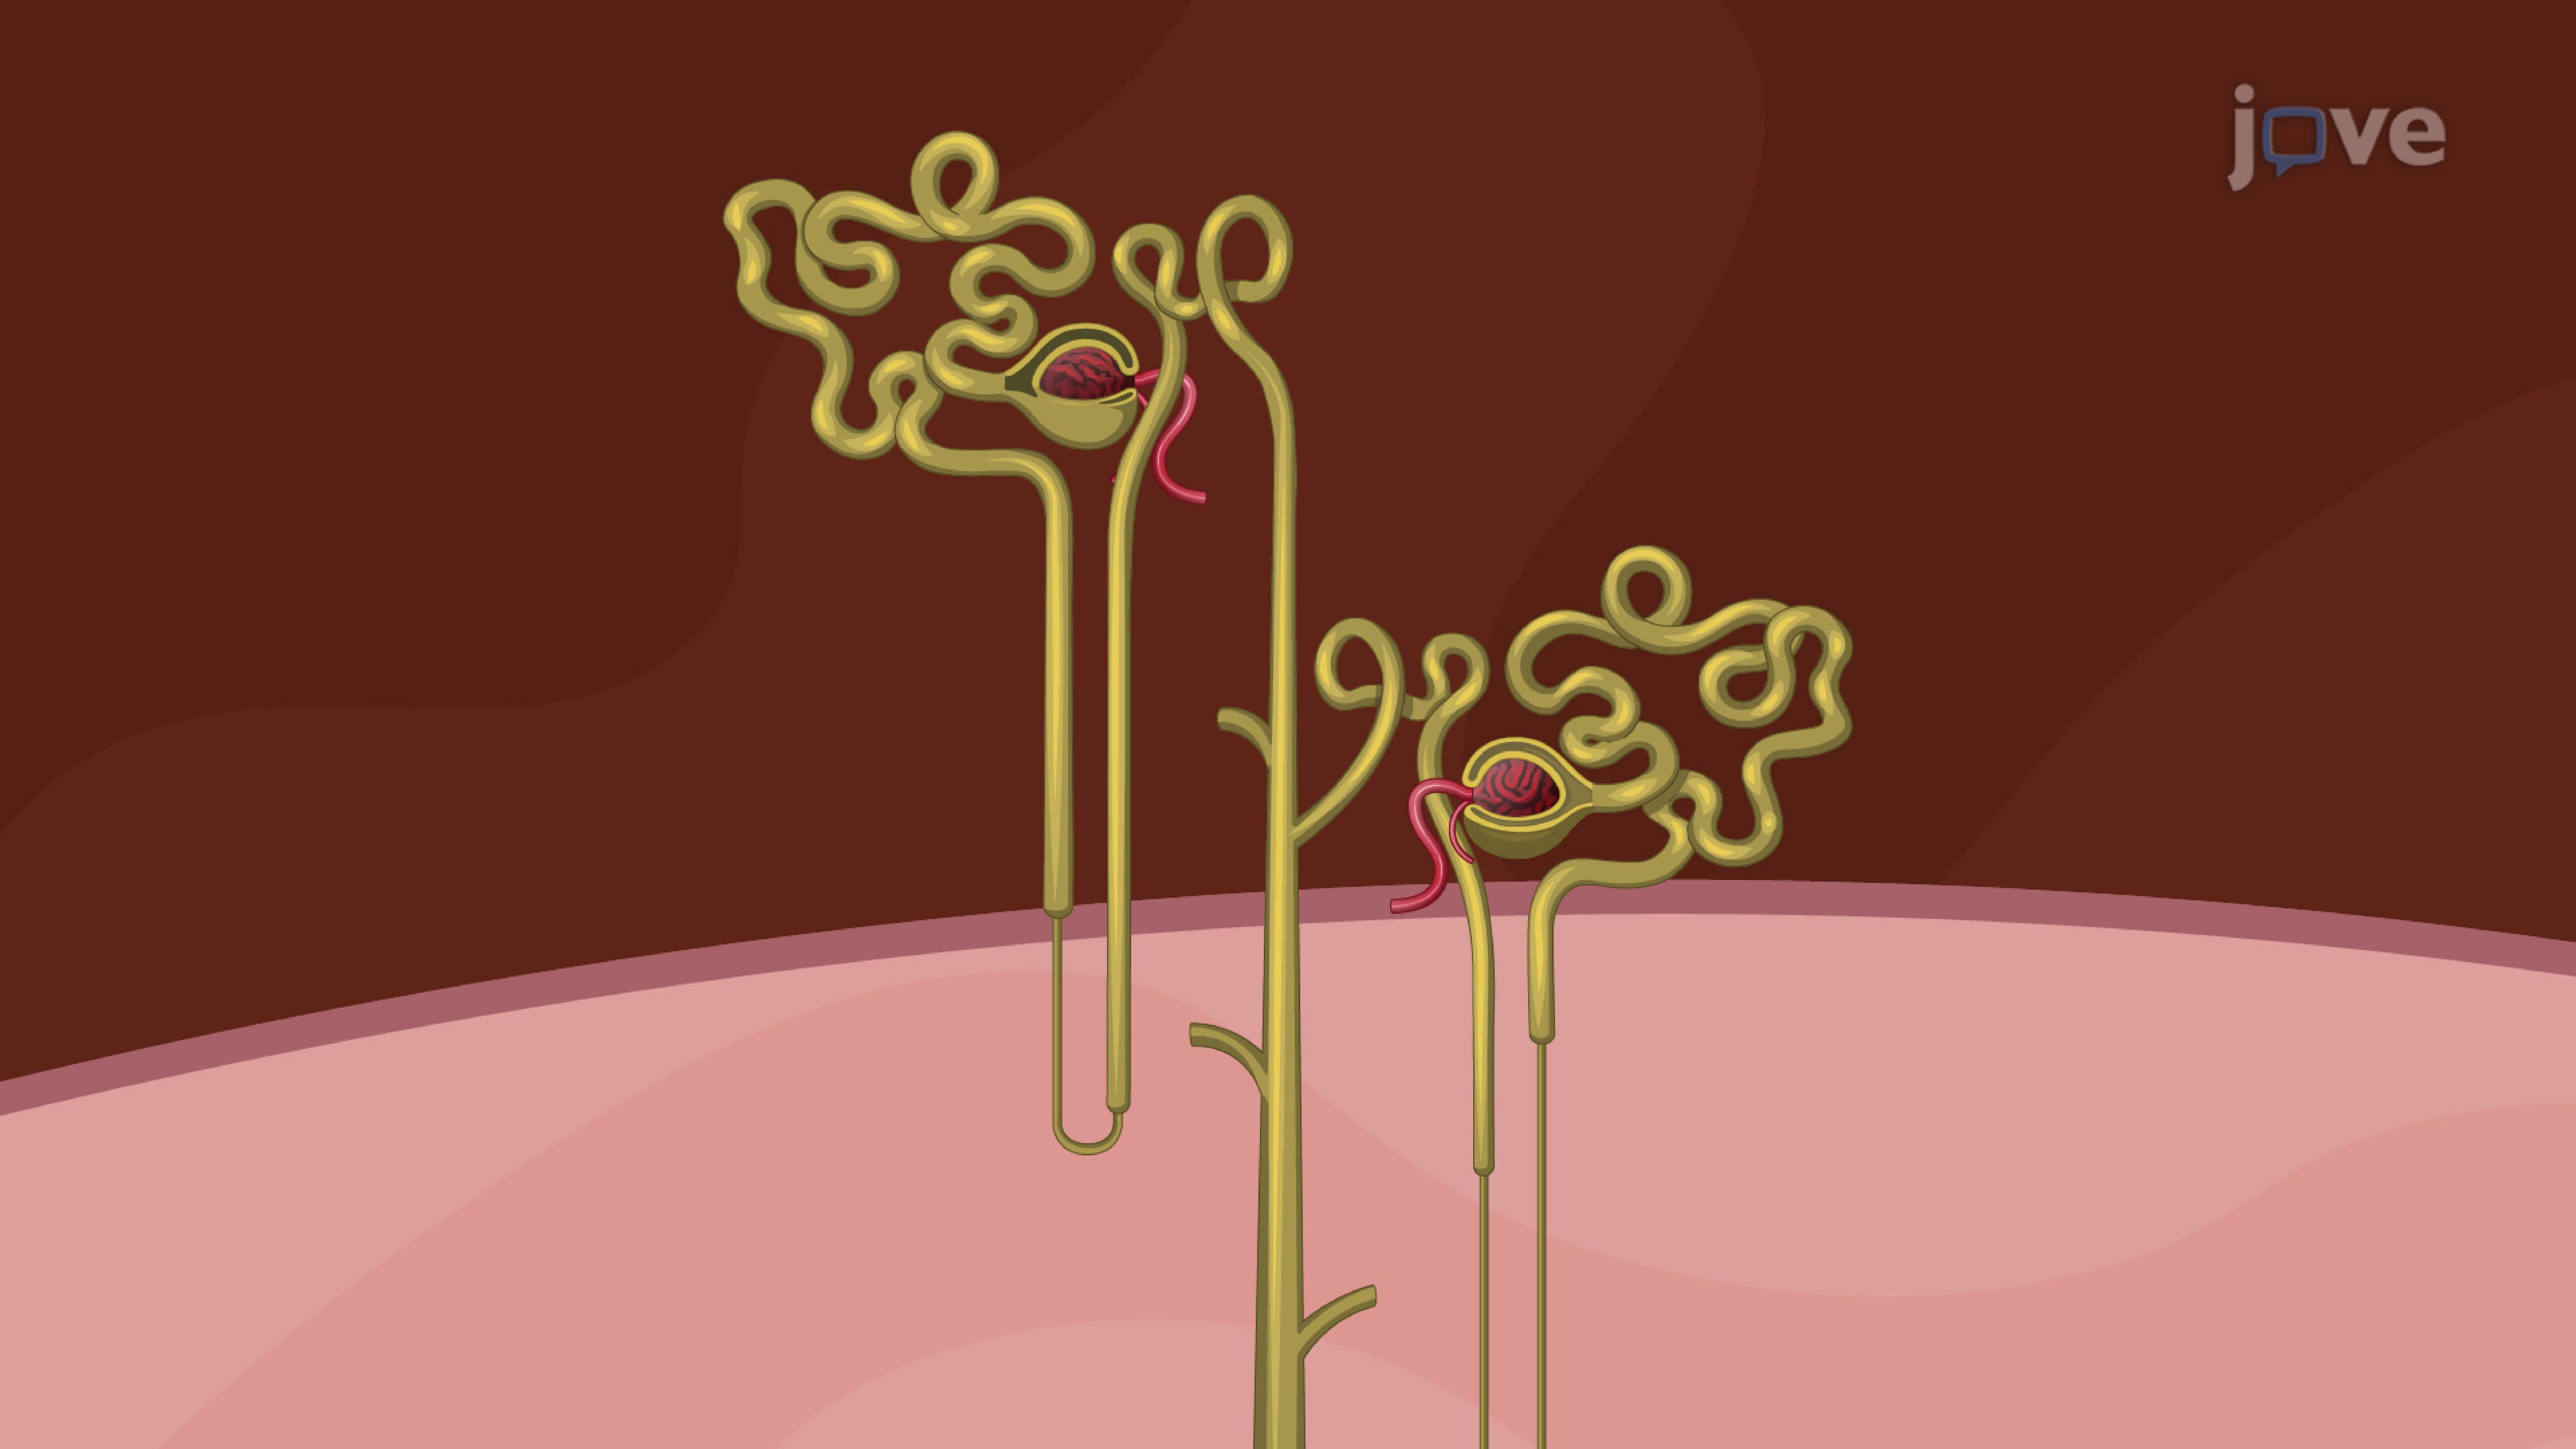
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
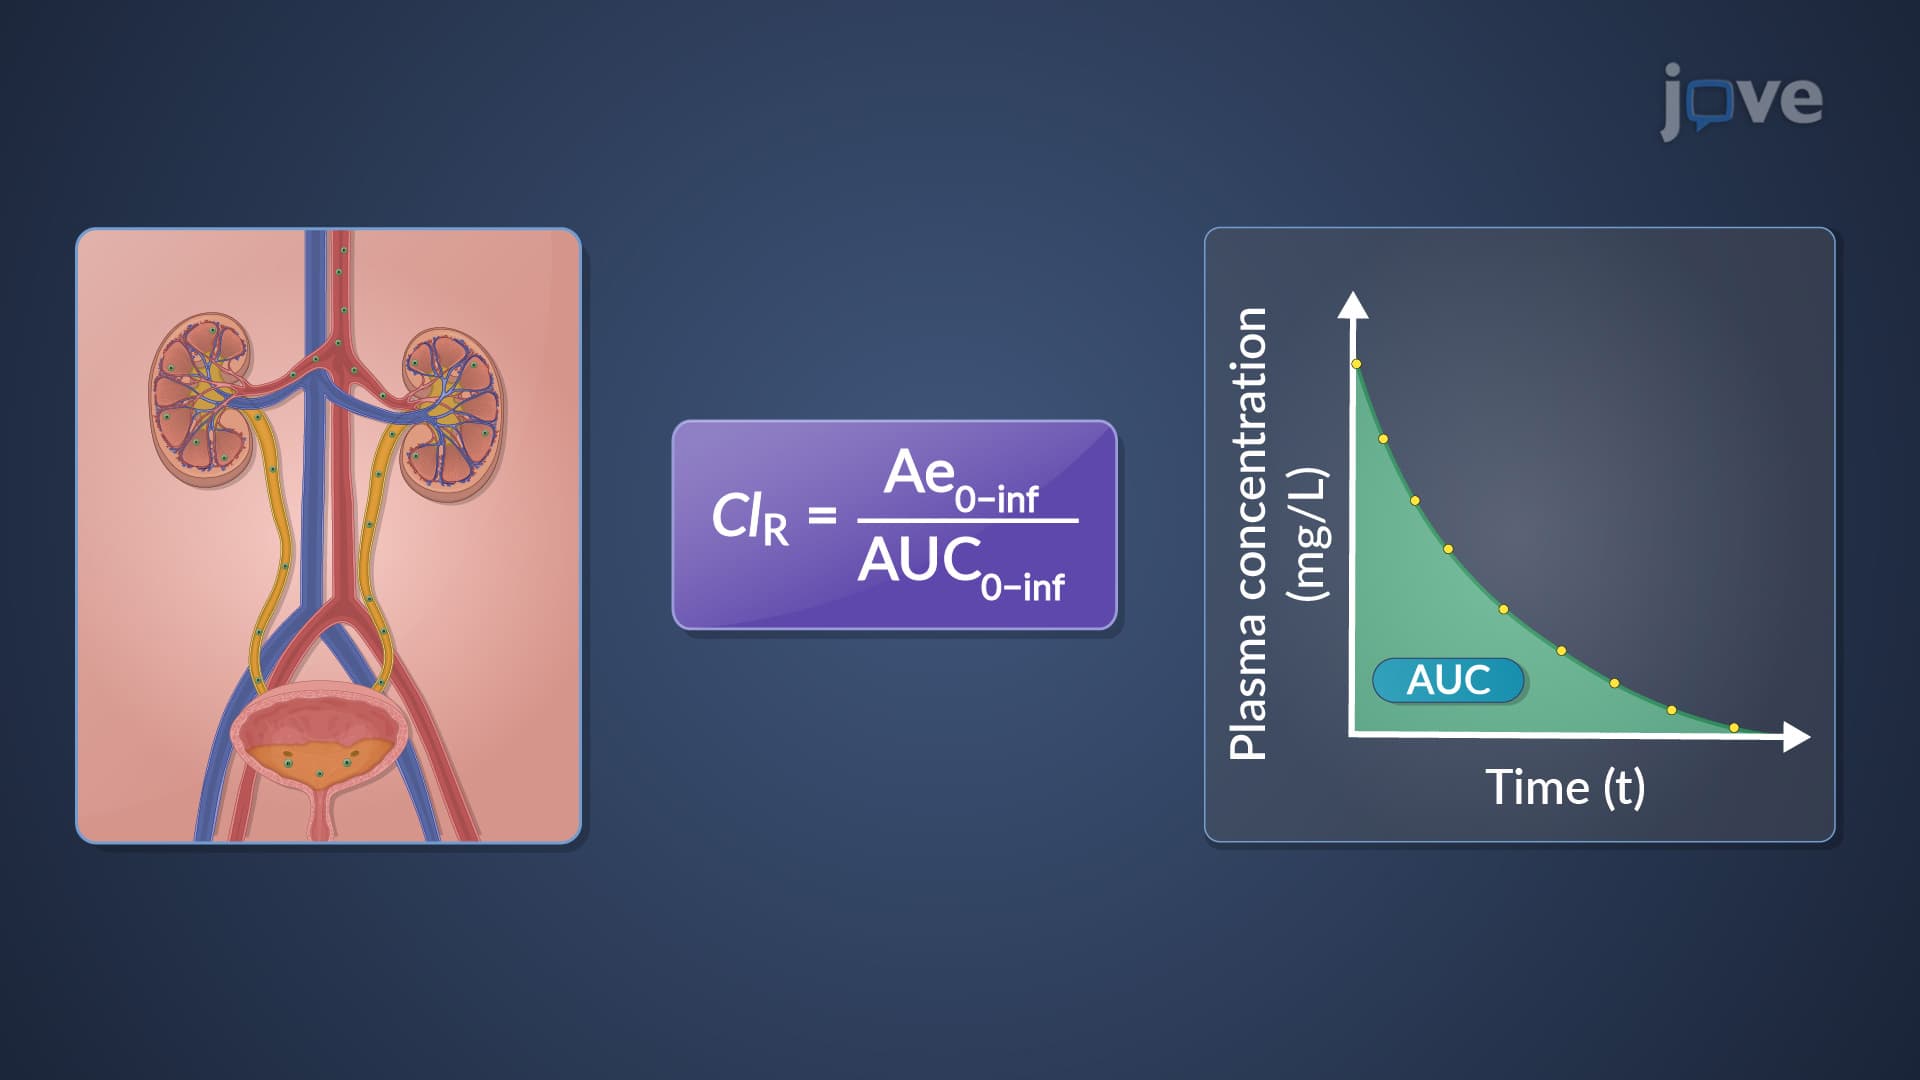
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a...