Related Experiment Video
Updated: Jul 11, 2025


A Precision Medicine Tool for Measurement and Monitoring of Hemoglobin S in Sickle Cell Disease Patients Receiving Transfusion Therapy
Sickle cell disease and pregnancy
Julie Carrara1, Anoosha Habibi2, Alexandra Benachi1
1Service de Gynécologie-Obstétrique, Hôpital Antoine Béclère, AP-HP, Université Paris Saclay, 92140 Clamart, France.

Abstract:
Pregnancy is a particularly risky period in the life of patients with sickle cell disease (SCD). Physiological changes during pregnancy increase the risk of vaso-occlusive crises (VOC), acute chest syndrome, venous thromboembolic events, and infections. This concerns haemoglobin (Hb) S/C and S/β+-thalassaemia patients as much than S/S or S/β0-thalassaemia patients. SCD also increases the risk of obstetrical complications, such as preeclampsia, in utero foetal death, preterm delivery mostly induced, and intrauterine growth restriction. Thus, pregnancy should be planned and closely monitored by a multidisciplinary team involving obstetricians and sickle cell disease specialists. Before pregnancy, the parents should also be informed about the risk of transmission of this autosomal recessive disease, and the father should therefore be prescribed haemoglobin electrophoresis. Treatments have to be revised when planning pregnancy: hydroxyurea (HU) should be stopped as soon as pregnancy is suspected or confirmed. Preventive blood transfusion is not systematic, but is recommended in the case of a pre-existing transfusion program prior to pregnancy, severe pre-existing organ damage, severe obstetric history, and severe or repeated crises during follow-up, especially in patients taking HU before. Despite the risks of prematurity, systematic administration of corticosteroids for foetal lung maturation is not recommended due to the risk of maternal vaso-occlusive event. Although more frequent, due to obstetrical and maternal complications, caesarean section is not systematic, in the absence of maternal contraindications. It is advisable not to exceed the term of 39 weeks of amenorrhoea. Post-partum follow-up is recommended, particularly because of the risk of thromboembolism.
More Related Videos
 08:23
Characterization of Sickling During Controlled Automated Deoxygenation with Oxygen Gradient Ektacytometry
Published on: November 5, 2019
 05:23
Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Related Concept Videos
 01:49
Multiple Allele Traits
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:19
Rh Blood Group
 01:22
Diabetes Mellitus: Type 2 and Gestational
 02:57
Meiosis vs. Mitosis
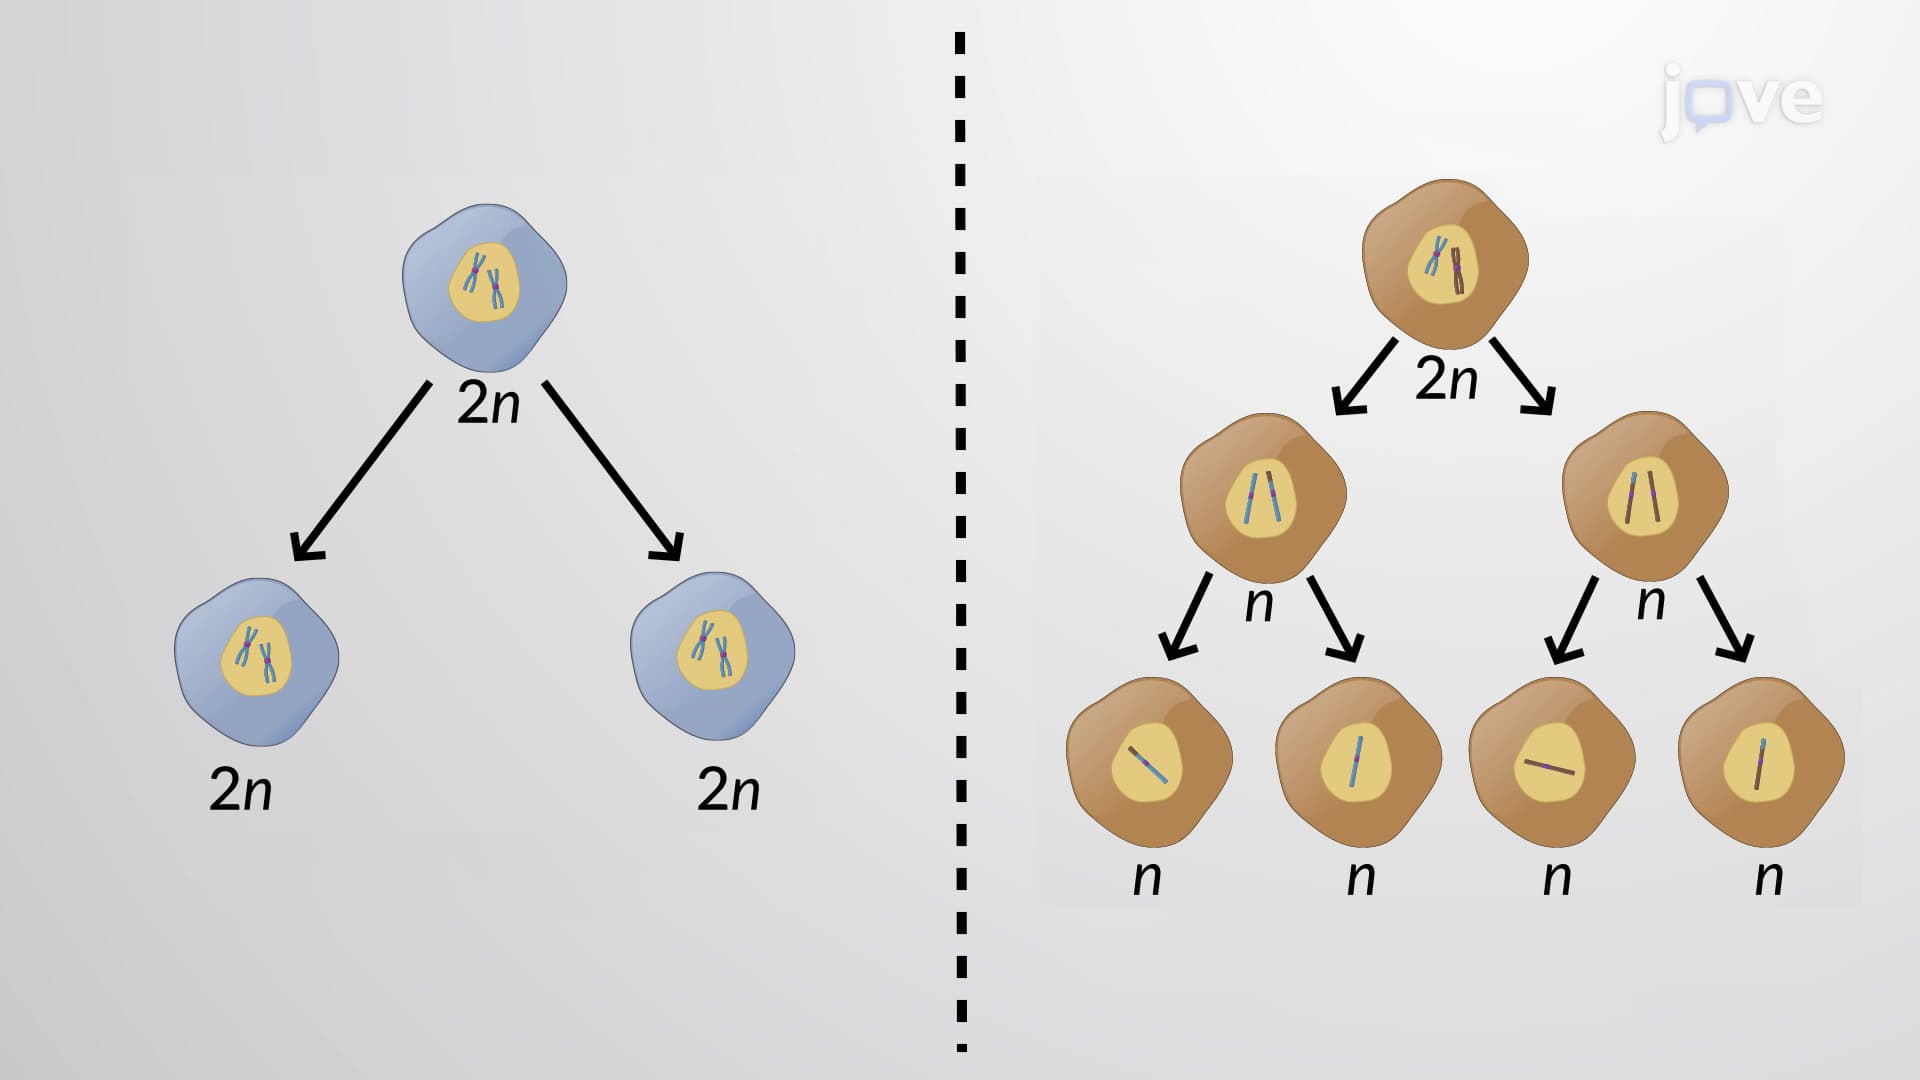
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:27
Disorders of Erythrocytes
Erythrocyte disorders can be broadly categorized into two main types: anemic and polycythemic conditions.
A low oxygen-carrying capacity of the blood due to the loss, lower production, or destruction of erythrocytes is termed anemia. Hemorrhagic anemia, for example, occurs when bleeding from an external wound or internal ulcer reduces erythrocyte counts.
On the other...